

Hospice in a Spanish-Speaking Household: The Questions Families Ask First
You are the one who takes the call from the doctor. You are the one who turns it into words your mother or father can hear. And you are also the son or daughter, sitting in the same room, trying not to cry while you do it.
In Monterey County, that scene is common. Roughly 62 percent of residents are Hispanic, and about 65,000 people here are 65 or older, so a huge share of local end-of-life conversations happen through a family member who is interpreting, scheduling, and grieving all at once.
This article answers the questions families ask first when hospice comes up in a Spanish-speaking household. Language, who decides, money, faith, and why so many people find out about all of this far too late.
Will someone who speaks Spanish actually come into the house?
This is the first question, and it deserves a straight answer instead of a brochure line about "language services available."
Ask any agency in Salinas, King City, Hollister, or on the Peninsula these questions before you commit:
- Which visiting clinicians on your team speak Spanish? Not the office. The Registered Nurse, the Hospice Aide, the Medical Social Worker who will actually walk through the door.
- Will a bilingual clinician be assigned to this case, or is it whoever is on the schedule that day?
- How does interpretation work during a scheduled visit? In person, by phone line, by video?
- How does it work at 2 a.m.? The on-call nurse is the one you reach when breathing changes or pain spikes. If that line has no Spanish option, you will be interpreting at the worst hour of your life.
- Do the consent forms, the plan of care, and the medication instructions already exist in Spanish? Translated on the spot is not the same thing as printed and left on the counter.
There is one conversation where this matters most. Research on hospice enrollment has found that interpretation quality breaks down around prognosis, the exact moment when precision is everything.
So ask directly who will interpret when the doctor explains how much time is likely left. It should not be you.
What to ask, and what a real answer sounds like
Bring this list to the first phone call. You are allowed to ask all of it before anyone comes to the house.
| Ask this | Why it matters | A solid answer sounds like |
|---|---|---|
| Who on the visiting team speaks Spanish? | Office staff and field clinicians are not the same people | Named roles, not a general yes |
| How is the after-hours line handled in Spanish? | Nights and weekends are when families panic | A specific process, available 24/7 |
| Are forms and medication instructions printed in Spanish? | Written instructions get reread at 3 a.m. | Yes, and they show you a sample |
| Who interprets prognosis conversations? | This is where meaning gets lost most often | A trained interpreter or bilingual clinician, not a relative |
| Can my parent choose who receives clinical updates? | Many patients want certain details handled carefully | The patient directs this, in writing |

Does hospice mean sending my parent somewhere?
For a lot of families, the word lands like a building. A place you send someone. A decision to stop caring.
In this region, hospice is almost always care delivered in the patient's own bedroom. The family stays in charge of the home, and the team comes to them.
That team includes Registered Nurses, Hospice Aides, Medical Social Workers, Chaplains, Physical and Occupational Therapists, Volunteers, and other clinicians. They visit on a schedule, and someone is reachable around the clock.
Families also mix up hospice, home health, and palliative care in a single sentence, which is completely understandable. Home health is recovery focused. Palliative care runs alongside treatment. Hospice begins when the goal shifts from curing to comfort.
One caller described the turn this way: "He wants to stop dialysis and focus on comfort at home." That sentence is how real families say it, and it is a clear, dignified choice, not a surrender. If that is where your family is, what happens after stopping dialysis is worth reading before the next appointment.
It also helps to know that hospice is not what most families picture.
Who actually comes to the house
Hospice at home is a team, not one nurse. Here is who shows up and what each person handles.

Who decides, when the whole family is involved?
In many multigenerational households, the answer is not one person. It is a mother, four siblings, a spouse, and an opinion from the aunt in Greenfield.
Here is how care teams usually handle that:
- The family names a spokesperson who receives updates and coordinates visits, which cuts down on five people getting five versions of the same news.
- The patient directs who receives clinical information. If your father wants certain details handled a specific way, or wants them shared with one child first, he can say so and the team follows it.
- Disagreement in the first week is normal. Social workers sit with families through exactly this.
Some adult children feel that agreeing to hospice means giving up on a mother or father. That feeling is real and it deserves space, not a lecture.
There is no single correct way for a family to organize itself. If your siblings are still arguing, the conversation about knowing when it is time is often easier to have than the decision itself.
Who pays for this, and how do I know the caller is legitimate?
Families raise these two together, so let's answer them together.
Hospice is covered under Medicare, Medi-Cal, and Veterans benefits. That matters in a county where households headed by someone over 65 report lower median income than the county overall, and roughly 9.5 percent of families live below the poverty line.
In general, the hospice benefit covers visits from the team, medications tied to the terminal illness, medical equipment like a hospital bed, and supplies. What typically falls outside it includes room and board in a facility, treatment unrelated to the terminal diagnosis, and around-the-clock help in the home.
Costs and coverage details vary by plan and situation, so ask any provider to put the specifics in writing before you sign. Room and board questions trip up families most often.
On legitimacy, families are right to be careful. A reputable provider will:
- Confirm the identity of any staff member who contacts you
- Give you a callback number you can verify
- Never ask for personal or financial information before an in-person assessment is confirmed
If a call feels like a sales pitch, it probably is one. Vetting a hospice provider is a reasonable thing to do, not an insult to anyone.
Can a priest come? What about prayers and family at the bedside?
Yes, and yes. A home is still your home when hospice is involved.
Chaplains work with your family's own parish or pastor rather than replacing them. If your mother has attended the same church in Salinas for forty years, the team helps coordinate with that priest, not around him.
Relatives at the bedside, prayers, candles, an altar in the corner of the room, none of that is a problem. Clinicians will ask about safety with open flames near oxygen, and that is the only real limit.
The team will also walk you through what happens in the hours right after a death at home, including who to call and what does not need to be rushed. Families are often surprised by how much time they are allowed to simply sit.
Support does not end there. Bereavement services continue for the family afterward, and grief support is open to people who were never hospice families at all. Spanish-language grief support meets in this region, so ask what is available near you instead of assuming nothing is. Here is what grief support actually looks like.
Why do families find out about all of this so late?
One caller said it plainly: "I did not know you offered that here."
That comes up constantly. People in Monterey County often learn at a crisis point, usually a hospital discharge, that home-based palliative care, wound care, and hospice exist in their own community.
Timing matters more than most families realize. National research on 2018 Medicare decedents found hospice use at 55.8 percent for non-Hispanic white beneficiaries compared with 46.2 percent for Hispanic beneficiaries, and that starting hospice before the last day of life was strongly tied to dying at home across every group. You can read the full study from the National Institutes of Health.
The research points at information and language access far more than at family preference. Families want this care. They often just do not know it is available in Spanish, at home, down the road.
You do not need a hospital transfer to start. A phone call and a conversation with the treating physician is enough to begin asking questions.
Frequently Asked Questions About Hospice Care for Spanish-Speaking Families
Can I ask for a bilingual nurse specifically, or is that rude?
It is not rude at all. Ask for it directly, and ask whether it applies to every visit or only some. A provider that handles this well will tell you exactly which roles on the team speak Spanish.
My mother does not want to know her prognosis. Do you have to tell her?
The patient directs who receives clinical information and how it is shared. Many families in this region ask that certain details go to a designated family member first. Tell the care team early so the plan is documented rather than improvised in the living room.
Is hospice free with Medi-Cal?
Hospice is covered under Medicare, Medi-Cal, and Veterans benefits, but what is covered depends on the plan and the situation. Ask for the coverage details in writing before services begin, including anything that falls outside the benefit.
Can we still call 911 if something happens?
You can always call 911. But once hospice is in place, the on-call line is usually the faster path to comfort, because the nurse knows the patient, the medications, and the plan. Ask how that line works in Spanish before you need it.
What if my family cannot agree on hospice?
That is normal in the first week, not a sign your family is failing. Medical Social Workers sit with families through disagreement regularly, and no one is asked to sign anything in a single conversation.
Does grief counseling cost anything if my father was never a patient?
Grief support is offered to people in the community who are grieving a loss, not only to families who used hospice. Ask what groups meet near you and whether any of them run in Spanish.
If you are the one doing the translating
Central Coast VNA & Hospice is a nonprofit that has served this region since 1951, reached into the Salinas Valley in 1969, and opened a Hollister office for San Benito County in 1974, with Latino community outreach through the Taylor Farms Family Health and Wellness Center. That history is why families here sometimes recognize the name from a neighbor rather than an ad. A care coordinator can answer questions about home health, palliative care, hospice, or grief support at 831-372-6668 or ccvna.com.

The First 48 Hours After a Family Calls About Hospice
A doctor said the word hospice for the first time, or your mother is being discharged tomorrow and someone handed you a phone number. You are not comparing agencies or reading about care philosophies. You want to know one thing: when does a nurse actually come to the house?
That question has a real answer, and it is usually measured in hours or a day or two, not weeks. But the timeline depends on a few steps most families have never heard of until the moment they need them.
This walks through the sequence as it actually unfolds on the Central Coast, from that first phone call to what physically changes in the house by day two.
What Happens When You Call Hospice on Day One
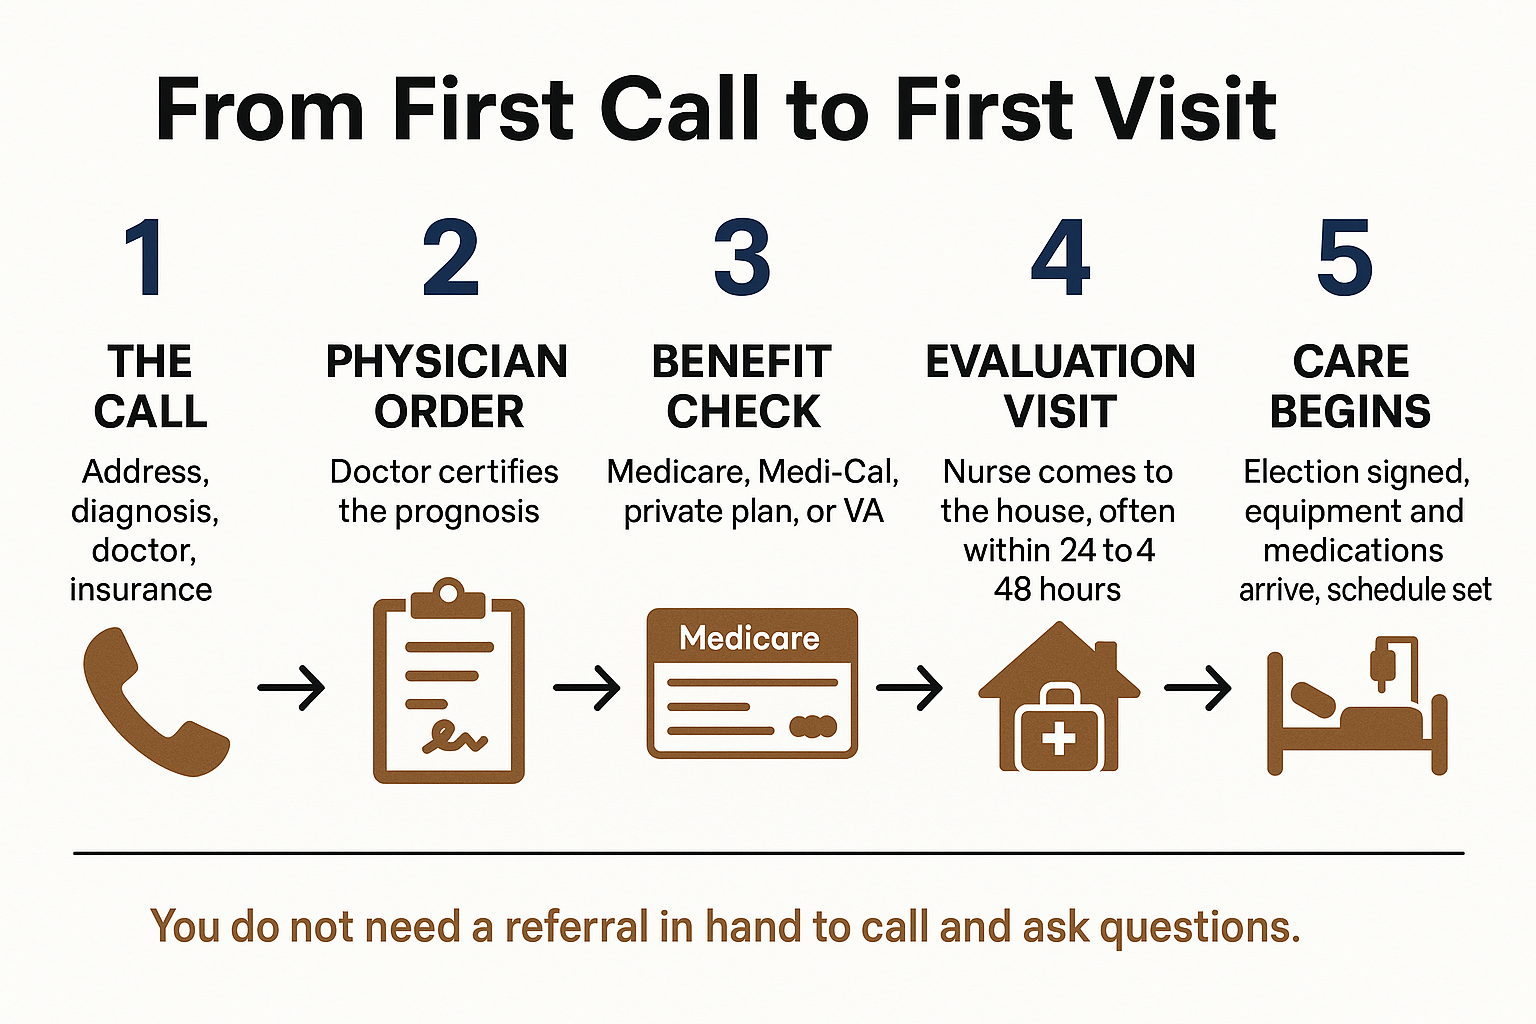
The first call is short. Most last only a few minutes, and the person on the other end is gathering enough information to figure out whether services can start and how fast.
Expect to be asked:
- The city or address where the patient is living, since coverage areas have real boundaries
- The main diagnosis and the name of the doctor following it
- Whether the patient is at home, in the hospital, or in a rehab facility right now
- What insurance the patient carries, usually Medicare, Medi-Cal, a private plan, or Veterans benefits
- Who is at the house day to day, and who has authority to make decisions
That address question matters more than families expect. Roughly one in twenty calls to local agencies ends right there because the patient lives outside the service area, so it is worth naming the city first thing. Households in Greenfield, King City, Hollister, and Marina all sit at very different distances from Monterey.
And you do not need a referral in hand to call and ask questions. Many families lose two or three days waiting for paperwork they were allowed to ask about by phone the whole time.
The Physician Order: The Step That Stalls Families the Longest
About one in ten callers asks how the referral works, and many are surprised by the answer. A hospice agency cannot simply start care because a family requests it.
The sequence usually runs like this:
- A physician certifies that the prognosis meets hospice criteria, generally a life expectancy of six months or less if the illness follows its expected course
- The referral reaches the agency, often by fax or secure message
- Intake verifies the benefit, Medicare, Medi-Cal, private insurance, or VA coverage
- An evaluation visit gets scheduled, commonly within 24 to 48 hours once the order is in hand
On the Central Coast, most referrals do not come from the family at all. They come from a hospital discharge planner at a Monterey Peninsula or Salinas hospital, a dialysis center, a medical group, or a skilled nursing facility.
That is helpful, but it also means families sometimes call to ask whether their doctor's referral has arrived yet. It is a fair question to ask directly, and worth asking twice if nobody has called you back.
If you are still sorting out whether hospice or home health fits the situation, After the Hospital Discharge, What Comes Next? and Home Health vs. Hospice: How Families Know Which One Fits Right Now lay out the difference in plain terms.

A Realistic First 48 Hours
Timing shifts with distance, the time of day the referral arrives, and how quickly the physician order clears. This is a common shape, not a promise.
| Timeframe | What usually happens | What the family can do |
|---|---|---|
| First call, 5 to 15 minutes | Intake gathers address, diagnosis, doctor, insurance, and decision maker | Ask what number reaches a nurse overnight and on weekends |
| Same day | Referral and physician order confirmed, benefit verified | Ask whether the doctor's referral has actually arrived |
| Within 24 to 48 hours | Registered Nurse comes to the house for the evaluation visit | Have the medication bottles and insurance cards in one place |
| End of the evaluation visit | Election signed, written Medicare addendum reviewed, visit schedule set | Ask what is covered and what is not before signing |
| Day two | Comfort medications and equipment can arrive, team introductions begin | Write down which team member handles which question |
The Intake Sequence at a Glance
Five steps stand between a first phone call and a nurse at the kitchen table.
Inside the Evaluation Visit
This is the part families quietly dread, and almost nobody describes it ahead of time. A Registered Nurse comes to the house and sits down, usually for an hour or more.
The visit covers:
- The diagnosis and recent history, including the last hospital stay
- Every current medication, which is why it helps to gather the actual bottles beforehand
- What the patient wants the next few weeks to look like, in their own words
- What the hospice benefit pays for and what it does not
- Who else will be coming to the house, and how often
Under Medicare, hospice care related to the terminal illness is generally covered with little or no out-of-pocket cost, though plans and situations vary and the agency should verify your specific coverage.
You will also receive a written election statement addendum listing items and services the hospice will not cover. CMS finalized the FY 2027 hospice rule on July 30, 2026, making that document mandatory at every election. Read it at the table, not later. The new Medicare form families get explains what usually shows up on it.
One thing worth saying plainly: electing hospice is signed by the patient or their representative. A doctor can certify eligibility, but no one imposes this on your family.
Over the following days you will meet the rest of the team: nurses, therapists, social workers, chaplains, volunteers, and other clinicians. Ask for names and roles and write them down.
What Physically Changes in the House by Day Two
For most families, the open-ended waiting is the worst part. That is what ends first.
Within a day or so of the election, several concrete things can show up:
- A comfort medication supply kept at the house for pain, breathing, nausea, and agitation
- A hospital bed, often set up in a living room rather than a bedroom
- An oxygen concentrator, bedside commode, wheelchair, or walker
- A written visit schedule replacing the guesswork
About seven percent of calls to local agencies are families asking when the nurse will arrive and whether they can get an exact time. The honest answer is that agencies give arrival windows instead of appointments, because a clinician who finds a patient in crisis at the previous stop does not leave on schedule. Someday that will be your house, and you will want them to stay.
Distance shapes the window too. A household in Pacific Grove or Salinas and a household in King City or Hollister may see different first visit times purely because of drive distance across Monterey County. Ask about that on the first call.
Ask one more thing on that call: what number reaches a nurse at 2 a.m. and on Sunday. Knowing who to call after hours is the single piece of information families say they wish they had written on the refrigerator sooner.
One limit worth understanding now: hospice does not provide round-the-clock personal attendant care in the home. Families who hire private personal care help on the Central Coast often report costs running into the thousands of dollars per month, and a Medical Social Worker can point you toward IHSS and local options.
Calling to Ask Questions Is Not the Same as Choosing Hospice
Plenty of families hesitate on that first call because it feels like a decision they are not ready to make. It is not one.
For the first time, a majority of Medicare decedents, 53.1 percent in 2024, were enrolled in hospice at the time of death, the third year in a row that figure rose, according to the National Alliance for Care at Home. Hospice has become the ordinary choice, not the unusual one.
Asking what the benefit covers, whether a parent would qualify, or how long the drive is from Monterey to your mother's house in Gonzales commits you to nothing. If eligibility is the part you are unsure about, the hospice eligibility question most families are afraid to ask covers it without the clinical language.
Why a Long-Established Local Agency Answers That Call Differently
There is a practical difference between an agency that has driven Highway 101 to King City for decades and one that has not. It shows up in how fast someone can tell you whether they cover your street and how honestly they describe the first visit window.
Central Coast VNA & Hospice has been answering these calls in Monterey County since 1951 and marks 75 years in 2026. Volunteers alone contributed nearly 40,000 hours in 2025, more than five percent of all direct hospice care.
One family put the value of steady contact simply in a public review: "I appreciate everything that was provided to us from information on how to cope with a deteriorating health situation to who to contact 24/7 if more assistance was needed." That is usually what families remember, not the paperwork.
Frequently Asked Questions About Calling Hospice
Can I call before my doctor has written a referral?
Yes. You can call and ask questions with no referral and no commitment. Staff can explain eligibility, coverage, and service area, and can often coordinate directly with the physician's office to get the order moving.
How fast can a nurse actually come to the house?
Once a physician order is in place and the benefit is verified, the evaluation visit is commonly scheduled within 24 to 48 hours. Afternoon referrals and longer drives to places like Hollister or King City can push that later, so ask for a realistic window on the call.
Does Medicare cover this, and what about Medi-Cal or Veterans benefits?
The Medicare hospice benefit generally covers care related to the terminal illness with little or no out-of-pocket cost. Medi-Cal and Veterans benefits also cover hospice for eligible patients. Coverage details vary by plan and situation, so have intake verify yours specifically before the first visit.
My mother was just discharged and we need help now. Is that too soon to call?
No. A hospital or rehab discharge is the most common reason families call, and it is the right moment to ask questions rather than wait until something goes wrong at home over a weekend.
Can services start before someone is at the end of life?
Yes, and many families do not realize it. Palliative care supports patients with serious illness while they continue treatment, and grief counseling is available to anyone in the community, not only families who used hospice.
Who signs the paperwork if my father cannot?
The patient signs the election, or their legal representative does if the patient is unable. Bring any power of attorney or advance directive documents to the evaluation visit so there is no delay.
Still Have Questions About the First Call?
If you are somewhere in the middle of this right now, with a discharge date coming and no clear next step, a care coordinator can walk you through the sequence for your own situation, including whether your address in Monterey County falls inside the service area. Central Coast VNA & Hospice can be reached at 831-372-6668, and asking questions carries no commitment of any kind.

What Hospice Does Not Cover: The New Medicare Form Families Get in October
Hospice admission almost never happens on a calm day. Someone has just come home from a hospital or rehab stay in Salinas or on the Monterey Peninsula, and a stack of paperwork lands on the kitchen table while the family is still absorbing what the doctor said.
Starting October 1, 2026, one page in that stack will be new to most families. It is called the hospice election statement addendum, and it lists the conditions, medications, and treatments the hospice has determined are not related to the terminal illness. Those items are not paid for under the hospice benefit.
Medicare finalized a rule that makes this form mandatory for every Medicare patient at the moment hospice begins. This article covers what is actually on it, who decided what, and how to read it line by line without guessing.
What the hospice election statement addendum actually is
The addendum is not brand new. It has existed for several years, but a family had to know to ask for it, and almost nobody knew to ask.
Under the FY 2027 hospice final rule, the hospice has to provide it to every Medicare beneficiary at the time of hospice election, requested or not. CMS confirms the change takes effect October 1, 2026.
The form generally spells out:
- Conditions the hospice determined are unrelated to the terminal diagnosis
- Items and services connected to those unrelated conditions
- Medications the hospice will not cover under the hospice benefit
- The patient's name, the hospice's name, and the date the determination was made
This is a transparency document, not a denial letter. Nobody is taking away a Medicare benefit. The point is to show the family, in writing and up front, where the hospice benefit stops, so a bill does not show up four months later as a surprise.
And that distinction matters when you are reading it at 8 p.m. in a house in King City with three other relatives on speakerphone. A list of exclusions looks alarming until you understand that it is a map, not a rejection.

Monterey County families are already asking this question before they sign anything
Coverage is one of the first things families here bring up. Roughly one in ten calls to a local home health and hospice line involves some version of "does Medicare cover this," and it comes up long before anyone is looking at a form.
Callers new to all of this also mix up three different things. Home health, palliative care, and hospice are separate programs with separate rules, and people often use the words interchangeably on the phone. If that sounds familiar, the difference between home health and hospice is worth sorting out first.
The addendum is the moment the abstract question turns concrete. It stops being "I wonder what Medicare pays for" and becomes a piece of paper with your mother's name at the top and a list under it.
That is uncomfortable, but it is better than the alternative. Families across Monterey County, San Benito County, and the Salinas Valley have historically found out about non-covered items the slow way, through an explanation of benefits that arrived weeks after a funeral.
What "unrelated" means, and why dialysis comes up so often
Hospice covers care related to the terminal illness. The hospice's clinical team decides what counts as related, and that judgment is what fills the addendum.
One family described the decision plainly: he wants to stop dialysis and focus on comfort at home. That is the situation where the related and unrelated line gets real, because kidney failure may be the terminal diagnosis in one case and a separate long-standing condition in another.
The items that most often trigger this conversation:
- Dialysis, especially when a different illness is the terminal diagnosis
- Ongoing chemotherapy or radiation intended to treat rather than comfort
- A long-standing medication for an unrelated condition, like a thyroid drug or a statin
- Treatment for an unrelated injury, such as a fall that breaks a wrist
If something lands on the list and you do not understand why, ask two questions. Why was this considered unrelated, and does original Medicare still cover it separately outside the hospice benefit?
Sometimes the answer is yes, and the treatment continues through Part B or Part D with different billing. Sometimes the answer reframes the whole conversation. Families weighing that exact tradeoff often find it helpful to read about what happens at home after someone stops dialysis.
Where common items usually land
Every case is judged individually by the hospice's clinical team, so treat this as general orientation rather than a rule. Use it to build your question list.
| Item or service | Where it usually falls | Question to ask the team |
|---|---|---|
| Pain and symptom medication for the terminal illness | Generally covered under the hospice benefit | Which of my parent's current drugs are you taking over? |
| Visits from nurses, therapists, social workers, chaplains, and volunteers | Generally covered under the hospice benefit | How often will each of these visits happen? |
| Home medical equipment such as a hospital bed or oxygen | Usually covered when tied to the terminal illness | Is this equipment covered, and who delivers it? |
| Dialysis when a separate illness is terminal | Often listed as unrelated | Why was this placed on the list, and what are the alternatives? |
| Long-standing drug for an unrelated condition | Often listed as unrelated | Does original Medicare or Part D still cover this separately? |
| Room and board in a facility | Not part of the hospice benefit itself | Who bills for the room, and at what rate? |
How to read the form, step by step
A short sequence for working through the addendum with the care team instead of guessing at it alone.

Do something with the form, not just to it
The worst way to read this document is alone at the kitchen table at 10 p.m. after everyone has gone home. By then the questions have nobody to land on.
A better approach:
- Read it with the Registered Nurse or Medical Social Worker present during a scheduled visit
- Bring a written list of every medication your parent currently takes, including over-the-counter ones, and ask about each
- Ask who made each determination and what the reasoning was
- Ask whether original Medicare, Part D, or Veterans benefits cover any listed item separately
- Keep a copy with the rest of the admission paperwork, not loose in a drawer
One more thing worth knowing. The addendum reflects one hospice's clinical determination at one point in time, and conditions change.
A medication that seemed unrelated in November may be squarely tied to symptom management by February. Asking for a fresh look as care evolves is a normal request, not a confrontation.
Why California families are being told to read paperwork closely right now
There is a reason hospice paperwork is getting more attention across the Central Coast. California's emergency hospice licensing rules took effect June 22, 2026, and state officials have said more than 280 hospice licenses were revoked over roughly the past two years.
Most of that activity has centered in Southern California, but the tightened rules apply statewide, including here in Monterey County and Hollister. Families are being advised, correctly, to look at what an agency puts in writing.
The new federal addendum requirement fits that pattern. It forces an agency to make its own coverage decisions visible on paper at the start of care, where a family can see them and question them.
If you are still comparing agencies, it pairs well with the other homework: how families here vet a hospice provider covers what to verify before anyone signs.
Who at an agency can explain the list to you
Hospice at home is delivered by a team, not one person. That team includes Registered Nurses, Licensed Vocational Nurses, Physical Therapists and other therapists, Medical Social Workers, Chaplains, Hospice Aides, and Volunteers.
For coverage and benefits questions, the Medical Social Worker is usually the right person to ask. That role exists partly to untangle exactly this kind of paperwork.
One Monterey Peninsula family described that help in a public review of Central Coast VNA & Hospice: "She helped us find the right agency to cancel her mom's Medicaid in FL and recommended additional resources in the community."
That is the kind of question a social worker handles regularly, alongside the addendum, the billing questions, and the forms nobody at home has seen before. When you get the form, ask who on the team owns coverage questions, and then bring your list to that person.
Frequently Asked Questions About the Hospice Election Statement Addendum
Does the addendum mean Medicare is denying my parent's coverage?
No. It is a list, not a denial. It tells you which conditions and treatments the hospice has decided fall outside the terminal illness, so you know where hospice billing ends and other coverage may begin.
Can we disagree with something on the list?
Yes, and you should say so if something looks wrong. Ask the team why the item was considered unrelated and what they based that on. Determinations are clinical judgments, and a conversation about your parent's full history sometimes changes them.
Do we have to sign it?
A signature generally confirms that you received and reviewed the document, not that you agree with every clinical determination on it. Ask the nurse or Medical Social Worker to note your questions before you sign so they are on the record.
What happens if my parent's condition changes after admission?
The addendum reflects one point in time. If new symptoms appear or a condition progresses, ask the team to revisit which items are considered related. This is a reasonable thing to raise at any visit.
Does this apply to someone on a Medicare Advantage plan or Medi-Cal?
Hospice is generally paid through original Medicare even for people enrolled in a Medicare Advantage plan, so the addendum requirement applies broadly to Medicare beneficiaries electing hospice. Coverage layers vary by plan and by Medi-Cal status, so ask a care coordinator to walk through your specific situation.
Questions about what hospice covers for your family?
Central Coast VNA & Hospice is a nonprofit founded in 1951, marking 75 years in 2026, serving Monterey County including Salinas, King City, and the Monterey Peninsula, along with San Benito County and parts of the surrounding region. Medicare, Medi-Cal, and Veterans benefits are accepted. A care coordinator can talk through coverage questions at 831-372-6668 or at ccvna.com whenever you are ready.

How Do You Get Your Dog Certified as a Therapy Animal?
Direct Answer: You register through a recognized therapy animal organization. The path is usually a temperament and obedience evaluation, one or more supervised visits, then formal registration with proof of vaccinations and a recent vet exam.
You have watched your dog work a room. He leans into strangers, ignores the vacuum, and has never once flinched at a wheelchair at the Monterey Bay Coastal Trail. Someone has probably told you he would make a great therapy dog.
Then you look into it and hit a wall of acronyms. TDI, ATD, Pet Partners, CGC. It is not clear which one matters, what the test involves, or whether your dog would actually pass.
That confusion shows up in the numbers. Pet therapy volunteer posts get more engagement than any other volunteer content local hospice programs share, but the applications never match the interest. This guide walks through what certification really requires, what evaluators look for, and what visiting looks like once you are approved.
What “certified therapy dog” actually means
There is no state license for therapy dogs in California and no government registry. When people say “certified,” what they usually mean is registered with a national therapy animal organization that tested your dog and carries liability insurance for your visits.
That registration is what hospitals, skilled nursing facilities, and home-based hospice programs across Monterey County ask to see before you walk in the door. Without it, most programs cannot accept you, no matter how sweet your dog is.
It also helps to know what a therapy dog is not:
- Service dog: individually trained to do tasks for one person with a disability. Has public access rights under the ADA.
- Emotional support animal: provides comfort to its owner. No task training, no public access rights.
A therapy dog, by contrast, is trained and evaluated to visit other people, by invitation, in a facility or private home. No public access rights.
That last distinction matters. A therapy dog goes where he is invited, on a schedule, as part of a care team. The American Veterinary Medical Association keeps a clear breakdown of these animal-assisted intervention definitions if you want the clinical version.
The three organizations most Central Coast handlers use
Three registries come up again and again: Therapy Dogs International (TDI), Alliance of Therapy Dogs (ATD), and Pet Partners. All three are recognized by facilities on the Peninsula. They just get you there differently.
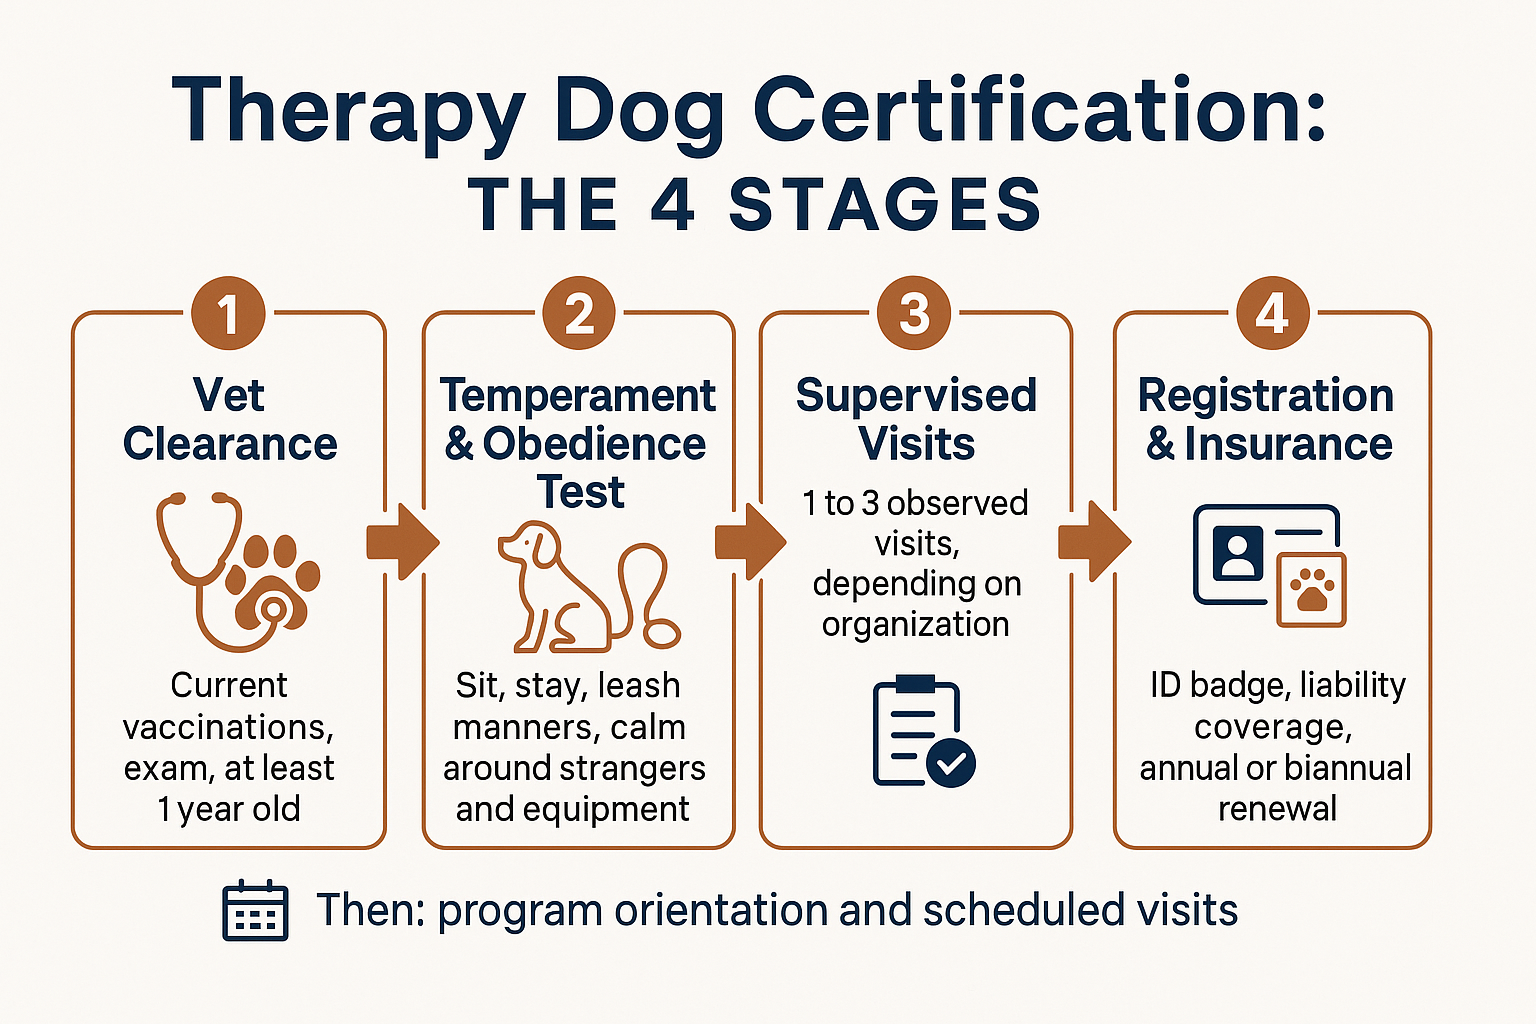
Therapy Dogs International runs a single hands-on test with a certified evaluator. The test borrows heavily from the AKC Canine Good Citizen exam and adds exposure to medical equipment like crutches and wheelchairs. Dogs generally must be at least one year old and have a current vet health record on file.
Alliance of Therapy Dogs tests the handler and dog together, then requires a set of supervised visits with a tester observing before you are registered. If you learn better by doing, this path gives you real practice before you are on your own.
Pet Partners asks the handler to complete a course first, then evaluates the team. It registers species beyond dogs and typically renews every two years rather than annually.
One practical Monterey County note: evaluators are not on every corner. Depending on the organization and the season, you may need to drive to Salinas, San Jose, or a scheduled group test date to get evaluated. Start by asking each organization where its nearest tester is before you commit.
Comparing the three main registration paths
Fees and requirements change, so treat this as general market context and confirm current details directly with each organization.
| Organization | How evaluation works | Typical cost and renewal |
|---|---|---|
| Therapy Dogs International | One in-person test with a certified evaluator, including exposure to medical equipment and unfamiliar people | Costs vary, but testing plus first-year membership commonly lands in the low to mid double digits. Annual renewal. |
| Alliance of Therapy Dogs | Handler and dog tested together, followed by supervised visits observed by a tester | Application and membership fees are usually modest, often somewhere in the $30 to $100 range combined. Annual renewal. |
| Pet Partners | Handler completes a course first, then the team is evaluated together | Course plus team evaluation and registration typically runs higher than the other two. Renews about every two years. |
The certification path, step by step
Most first-time handlers move through four stages. Knowing the order up front keeps the process from feeling like a maze.
What evaluators are really looking for
Before you pay any fees, sit down and assess your dog honestly. Evaluators are not looking for tricks or a competition-level heel. They are looking for a dog who stays calm when things get strange.
Here is what tends to decide pass or fail:
- Neutral response to strangers. The dog accepts petting from someone unfamiliar without jumping, mouthing, or shrinking away.
- Comfort around medical equipment. Walkers, wheelchairs, oxygen tubing, hospital beds, and the beeping that comes with them.
- Reliable basic obedience. Sit, down, stay, come, and walking on a loose leash without pulling.
- Recovery after a startle. A dropped tray or a raised voice happens. The dog can flinch. He needs to settle within seconds.
- No interest in food on the floor. Dropped pills and dropped snacks are real hazards in a patient’s home.
- Tolerance of clumsy handling. Hands that grip fur too hard or pat too heavily are common from someone with limited strength or dementia.
A dog who barks at the door, guards you, or gets wound up around other dogs is not disqualified for life. He is just not ready. Six months of steady work with a local trainer, plus practice walks near busy spots like the Del Monte Center parking lot, can change that answer.
One honest filter: therapy work asks more of the handler than the dog. You are reading the room, watching your dog for stress signals, and knowing when to end a visit early.
What visiting actually looks like once you are registered
Registration is the paperwork. The part people underestimate is what comes after.
Most local hospice and home health programs add their own onboarding on top of your national registration. Expect a volunteer application, a background check, a TB test, an orientation covering patient privacy and infection control, and a match with a volunteer coordinator who knows the families.
Then you get scheduled. Pet therapy visits in a program like Central Coast VNA & Hospice usually happen in private homes across Monterey, Carmel, Seaside, Salinas, and out to King City and Hollister, not in a facility lobby. You visit the same patients over time, which is the whole point.
You are also one part of a larger team. Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, Hospice Aides, Chaplains, and other Volunteers are all working the same care plan. Your visit gets coordinated around theirs, which is why home health visit schedules tend to be set in advance rather than day of.
The work itself is quieter than people expect. A dog resting his head on a bed rail while a patient who cannot speak easily strokes his ears. Companionship for a spouse who has not left the house in a week. Presence during a long afternoon.
In 2025 alone, volunteers across this region contributed close to 40,000 hours and more than 1,080 visits, accounting for over 5% of all direct hospice care. That is not a side program. It is built into how care gets delivered.
Frequently Asked Questions About Therapy Dog Certification
How long does the whole process take from start to finish?
Plan on two to four months for most people. The evaluation itself is under an hour, but scheduling with an evaluator, completing supervised visits, and getting through a program’s volunteer onboarding takes the bulk of the time. If your dog needs obedience work first, add several months to that.
Does my dog need to be a specific breed or size?
No. Temperament decides it, not breed. Small dogs work well for bedside visits because they can be lifted onto a lap or bed, and large calm dogs work well for patients who want to reach down and pet without bending. What matters is that the dog is at least a year old, has lived with you long enough for you to read him honestly, and stays steady in a strange room.
Do I need a Canine Good Citizen title first?
It is not required, but it helps. The CGC test overlaps heavily with therapy dog evaluations, so passing it first is good practice and tells you whether the real test is worth scheduling.
Can my dog visit hospice patients if he is certified but I am not affiliated with a program?
Generally no. Visits to patients happen through an established program that handles patient consent, privacy rules, infection control, and scheduling. Showing up independently is not an option, which is why registration and volunteer onboarding go together.
What if my dog fails the evaluation?
Most organizations let you retest after a waiting period, usually several months. Ask the evaluator exactly what the dog struggled with. Reactivity around other dogs and startle recovery are the two most common issues, and both respond well to focused training with a local trainer.
Are there volunteer roles if my dog is not a good fit?
Yes, and they are needed. Vigil sitting, companionship visits, reading aloud, respite so a family member can run errands, and office support are all real roles. One long-time VNA volunteer described the work simply: sitting bedside, providing comfort, being present when it matters most.
Thinking about pet therapy volunteering on the Central Coast?
VNA has been serving families in Monterey, San Benito, Santa Cruz, and South Santa Clara counties since 1951, and 2026 marks its 75th year. A new pet therapy volunteer joins a program with decades of structure behind it, not one being figured out from scratch. If you want to talk through whether your dog is a fit, or ask about other volunteer roles, you can reach a coordinator at 831-241-8423 or find details at ccvna.com.

When Heart Failure Keeps Sending a Parent Back to the Hospital
Your dad goes into the hospital short of breath. Three or four days later he is stable, the swelling is down, and he comes home with a folder of paperwork.
Then, a few weeks later, it happens again. Families across Monterey County read each of those admissions as a separate emergency, when it is usually one long decline showing up in pieces.
This article walks through why the cycle repeats, what changes when a clinician comes to the house instead of the other way around, and the questions worth asking well before the fourth admission.
Why Heart Failure Hospital Readmissions Keep Happening
Advanced heart failure means the heart cannot move blood forward the way it should. Fluid backs up into the lungs, the ankles, the abdomen. In the hospital, IV diuretics pull that fluid off fast.
At home, the same job falls to oral medication. And oral medication works slower than fluid builds when someone eats a salty meal, skips a dose, or has a rough week.
Three things usually go wrong in the gap:
- Nobody is weighing him daily. A two or three pound overnight gain is fluid, not food, and it is the earliest warning sign available.
- The medication list changed in the hospital and nobody reconciled it at home. Doses get adjusted on the ward, the old bottles are still in the cabinet, and both versions end up in play.
- The first cardiology follow-up is two or three weeks out. That stretch between discharge day and that appointment is where most of the damage happens.
By the time breathing gets bad enough to call 911, the fluid has been building for days. The admission was preventable, but only if someone was watching. Medication tracking alone trips up more families than anything else after a cardiac stay.

On the Central Coast, Distance Is Part of the Problem
Heart failure care depends on frequent check-ins. Geography here works against that.
About 15 percent of Monterey County residents are 65 or older, which is somewhere near 65,000 people. The cardiologists, meanwhile, cluster on the Peninsula and in Salinas.
So a family in King City or south county may be driving close to an hour each way for a twenty minute follow-up. A household in Hollister or east Salinas juggling work shifts often cannot make a weekday appointment at all without someone losing a day of pay.
When a visit is that expensive in time and gas, it gets postponed. And postponed visits are how a manageable fluid gain turns into an ambulance ride down Highway 101.
In-home skilled nursing changes that math in a plain way. The clinician drives to the house instead.
On a visit, a Registered Nurse or Licensed Vocational Nurse typically:
- Checks weight, blood pressure, pulse, and oxygen
- Listens to the lungs and looks at ankle and leg swelling
- Reviews what medications were actually taken this week, not what was prescribed
- Calls the physician when the numbers move the wrong way
That phone call, made on a Tuesday afternoon about a two pound gain, is often the whole difference. If you are unsure what these visits involve, skilled nursing at home is different from what most people picture.
Does Medicare Cover This, and Do We Need a Doctor's Referral First?
These are the two questions that stall families more than any others. Roughly one in ten callers to home care agencies gets stuck right here.
Here are the direct answers.
Yes, a physician's order is required. Medicare-certified home health is physician-directed care. It also requires a face-to-face visit with a physician or Nurse Practitioner tied to the condition being treated.
Medicare, Medi-Cal, and Veterans benefits all have pathways for home health. What your specific plan covers depends on the plan, the diagnosis, and whether the patient meets homebound criteria, so an agency's intake staff is the right place to confirm details rather than a blog post.
The fastest route after a cardiac admission is to ask the hospital discharge planner or the treating cardiologist to place the order before your parent leaves the building. Waiting until you are home turns a same-week start into a two-week scramble.
If the referral process itself is unfamiliar, here is why a physician referral is required and how it works.
The First Week Home After a Heart Failure Admission
This is the sequence that keeps a discharge from turning into a readmission. Print it and hand it to a sibling.

What a Strong First Week at Home Actually Looks Like
Families consistently describe the same moment. Someone was just discharged, and they need a person to come to the house and help them figure out what happens next.
A solid first week has four moving parts.
An assessment visit within a day or two. A nurse comes out, gets a baseline weight and vitals, walks the house for fall risks, and writes the care plan the rest of the week runs on.
A medication list reconciled against what was actually sent home. Not the discharge summary. The bottles on the counter. Old doses get pulled out of circulation.
A daily weight routine with a specific trigger number. Same scale, same time each morning, before breakfast, written down. Ask the clinician for the exact number that means pick up the phone. For many patients it is 2 to 3 pounds overnight or 5 pounds in a week, but that is a physician's call for your parent specifically.
One phone number for overnight symptom changes. Written on paper, taped to the refrigerator, where a visiting grandchild can find it. The first 72 hours set the tone for everything that follows.
Three Kinds of Home-Based Support for a Cardiac Parent
These are not competing choices so much as stages. Many families move through more than one as things change.
| Type of care | What it focuses on | Who starts it | Curative treatment continues? |
|---|---|---|---|
| Home health | Recovery, strength, medication stability, avoiding readmission | Physician order after a hospital stay or decline | Yes |
| Home-based palliative care | Breathlessness, fatigue, symptom control, care planning | Physician referral, can run alongside cardiology | Yes |
| Hospice care at home | Comfort, pain and breathing control, family and spiritual support | Physician certifies a six month prognosis if the illness runs its usual course | No, the goal shifts to comfort |
The Harder Turn Most Cardiac Families Never Hear About
Circulatory and heart conditions are the single most common reason people enter hospice nationally, close to 30 percent of stays. Most families with a cardiac parent are never told that.
There is a stretch, sometimes long, where the goal quietly shifts. It stops being about regaining function and starts being about fewer hospital trips and easier breathing at home.
That stretch can include home health first, then home-based palliative support running alongside cardiology, and later hospice if the trajectory continues. Palliative care does not require giving anything up, and it can start much earlier than families assume.
Hospice eligibility is a physician's clinical judgment about prognosis, not a form a family fills out. Medicare's coverage policy on determining terminal status lists cardiac indicators such as an ejection fraction of 20 percent or less as supporting documentation, while stating plainly that some patients who do not meet the published guidelines may still have a six month prognosis.
So it is a conversation, not a checklist. And asking the question early commits nobody to anything. It is information families deserve before the fourth admission, not after it.
What the Home Team Actually Looks Like
Families picture one nurse. What usually arrives is a group.
One Monterey Peninsula family described what happened after their 91 year old mother's physician made the referral: "A team made of nurses, physical therapists and Medical social worker came to help us." A nurse evaluated first, a second nurse came weekly for a month, and a Physical Therapist built an exercise plan that kept going after the visits ended.
Home-based cardiac support in this region is delivered by Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, Chaplains, Volunteers, and other clinicians. On cardiac cases, they work from protocols built with local cardiologists and coordinate back to the treating physician.
The Medical Social Worker matters more than families expect. That is the person who sorts out benefits questions, connects families to community resources, and helps when the paperwork side of things gets tangled.
Central Coast VNA & Hospice has been a nonprofit rooted in this region since 1951, which means the organization answers to the community here rather than to shareholders.
Frequently Asked Questions About Heart Failure Readmissions and Home Care
How fast can home health start after a hospital discharge?
When the order is placed before discharge, an assessment visit commonly happens within a day or two of arriving home. The delay families run into is almost always the referral, not the scheduling. Ask the discharge planner to send it while your parent is still in the bed.
Does my parent have to be bedbound to qualify for home health?
No. Medicare's homebound standard means leaving home takes a considerable and taxing effort, not that someone never leaves. Plenty of heart failure patients who can get to a doctor's appointment with help still qualify.
We live in King City. Do home health agencies actually drive that far?
Coverage areas vary by agency, and this is worth confirming before anything else. Central Coast VNA & Hospice serves all of Monterey County including King City and Greenfield, plus San Benito County, South Santa Clara County, and parts of Santa Cruz County. If an agency says no, ask them for a name of one that says yes.
Can we get palliative care while my mom is still seeing her cardiologist?
Yes. That is the whole point of it. Palliative care runs alongside treatment and focuses on symptoms like breathlessness, fatigue, and sleep. Several families each month are surprised to learn it does not require stopping anything.
What is the difference between home health and the help we need with bathing and meals?
Home health is skilled medical care ordered by a physician and covered under Medicare. Daily personal help with bathing, meals, and errands is a different category, often handled through IHSS or private duty agencies. Many families end up using both.
Thinking through the next step for a parent with heart failure?
If your family is somewhere in this cycle, in Salinas, Hollister, Carmel, King City, or anywhere across Monterey County, a care coordinator can talk through what home health, palliative support, and hospice each involve and what your parent's coverage looks like. There is no pressure and no commitment in asking. You can reach a coordinator at 831-372-6668 or find more at ccvna.com.

Who Brings the Hospital Bed? How Medical Equipment Reaches the House
A discharge planner at Community Hospital of the Monterey Peninsula or Salinas Valley Health says the words hospital bed, and then the conversation moves on to medications. Nobody stops to explain who orders the bed, who brings it, or when it shows up at the house.
Families across Monterey County call about home care on that same compressed clock. A parent is coming home tomorrow, the living room still has a couch in it, and someone has to figure out where an oxygen concentrator plugs in.
This is the practical sequence: how equipment gets ordered, who pays for what, how hospice changes the math, and whether the bed will even fit through the front door of a 1920s house in Pacific Grove.
Who Orders the Equipment and Who Delivers It
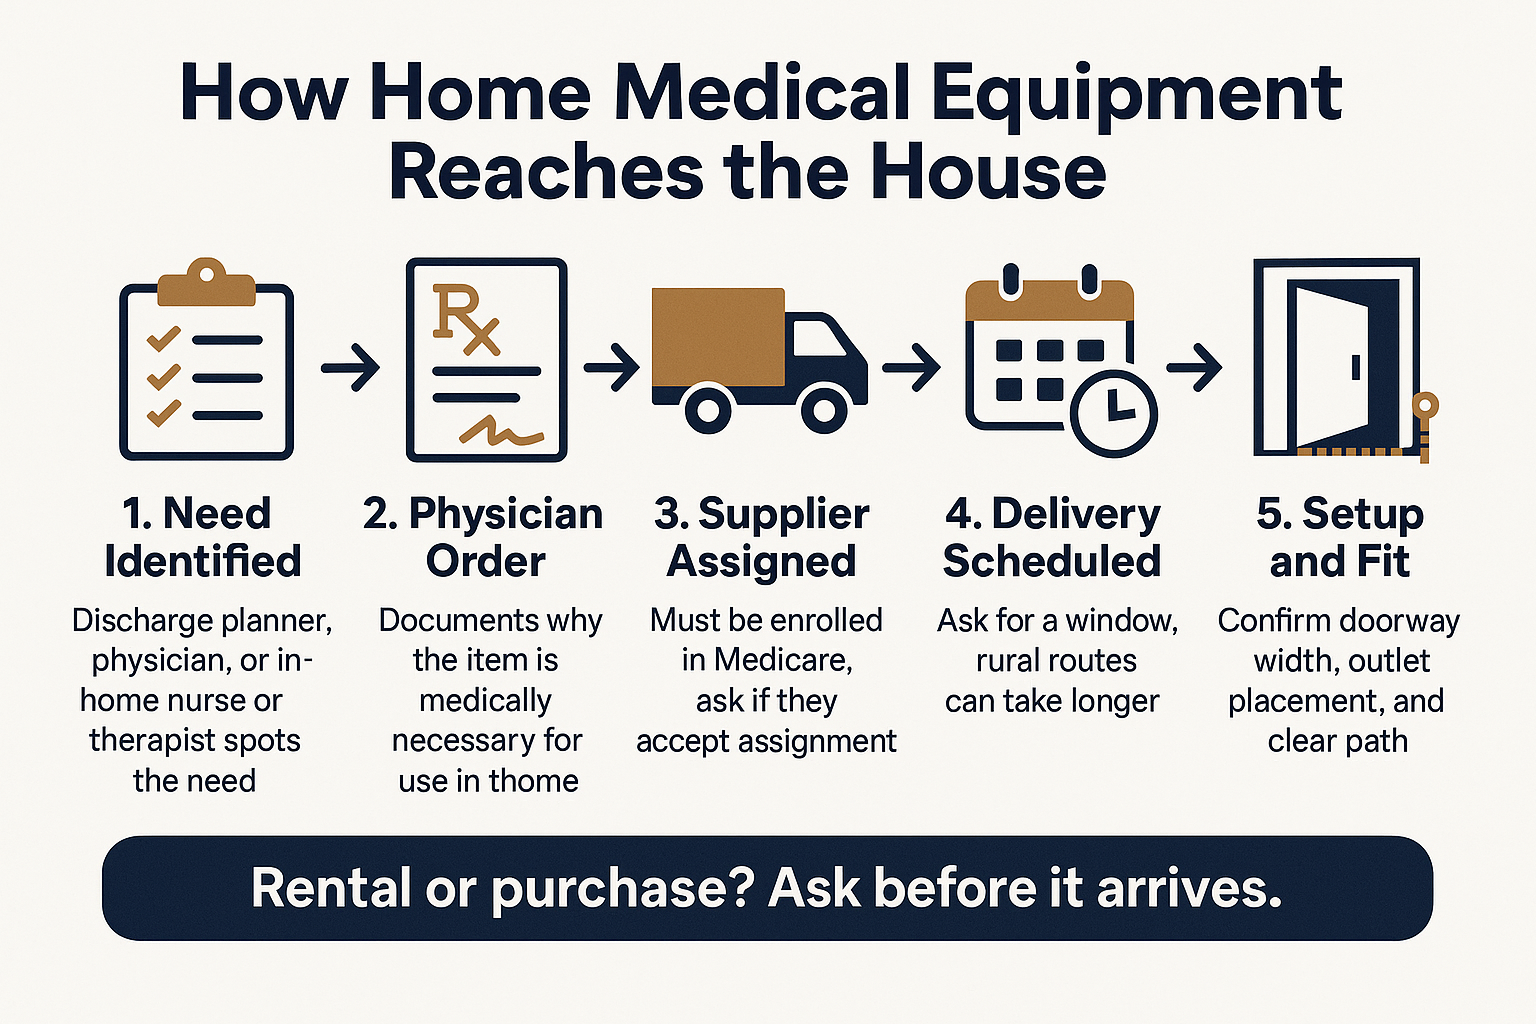
Home medical equipment does not come off a store shelf. For it to be covered, it generally needs a physician order documenting why the item is medically necessary for use inside the home, and it has to come from a supplier enrolled in Medicare.
The person who spots the need is often not the doctor. It is frequently a Registered Nurse or Physical Therapist on the first in-home visit, watching how someone actually moves through their own hallway, their own bathroom door, their own bedroom.
That visit catches things a hospital room never will:
- A bathroom doorway too narrow for a standard walker
- A bed too low for someone to stand up from safely
- A second-floor bedroom with no realistic way to get a hospital bed upstairs
- No outlet near the chair where the person actually sits all day
When a physician orders a pre-surgery home assessment, a lot of these decisions get made weeks early instead of in a scramble after discharge. One local patient put it plainly in a review: "The nurse that assess my environment prior to surgery left me with useful information."
If the equipment need surfaces after discharge instead, expect the order, the supplier, and the delivery to move on separate tracks. That is exactly where families get stuck, and it is worth reading up on what comes next after a hospital discharge before the day arrives.

Who Pays for a Hospital Bed at Home
Here is where families get surprised. Home health visits and home medical equipment are paid for in two different ways, even when both are happening in the same house on the same week.
Under Original Medicare, durable medical equipment falls under Part B. Per Medicare's own coverage rules for durable medical equipment, the item must be ordered by your provider for use in the home, must come from a Medicare enrolled supplier, and the patient is generally responsible for 20 percent of the Medicare approved amount after the annual Part B deductible when the supplier accepts assignment.
A few things change that picture:
- Deductible and approved amounts change every year, so last year's numbers are not this year's numbers
- Medicare Advantage plans set their own networks, prior authorization rules, and cost sharing
- Medi-Cal and Veterans benefits work on different rules entirely
- A Medigap policy may absorb part of the coinsurance
The practical trap worth knowing: a supplier that is not enrolled in Medicare, or one that does not accept assignment, can bill more than the approved amount. That difference lands on the family.
Confirm the numbers with the plan and the supplier before anything is delivered, not after. If a plan restricts which providers can be used at all, Medicare plan network limits are worth understanding early.
Hospice Changes the Equipment Math Completely
This is the piece families tend to learn late, often after weeks of worrying about bills.
Under the Medicare hospice benefit, equipment and supplies related to the terminal illness are part of the benefit itself. The hospice team arranges the bed, the wheelchair, the oxygen concentrator, and the supplies, and those items are not billed separately to the family the way Part B equipment is.
That means the calculation for a family weighing hospice at home in Salinas or Carmel Valley is different from the calculation for a family arranging equipment after a knee replacement. Same bed, same living room, different rules.
It does not cover everything. Room and board in a facility is a separate question, and one that trips up plenty of families, which is why who pays for hospice room and board is worth reading on its own.
But for equipment inside the house, the difference is real, and it is one of the more common surprises people mention once they finally understand how the benefit is built.
How Equipment Coverage Differs by Situation
A quick side by side of how the same hospital bed gets handled depending on which program a patient is under. Always confirm specifics with your own plan.
| Situation | Who arranges the equipment | What the family typically handles |
|---|---|---|
| Home health under Original Medicare | Physician order plus a Medicare enrolled supplier | Part B deductible, then generally 20 percent of the approved amount |
| Home health under Medicare Advantage | Plan network supplier, often with prior authorization | Plan-specific copay or coinsurance, network rules apply |
| Hospice under the Medicare hospice benefit | Arranged through the hospice team | Equipment related to the terminal illness is part of the benefit |
| Medi-Cal or Veterans benefits | Program-specific authorization process | Different cost sharing rules, confirm before delivery |
The Path From Order to Delivery
The sequence most families never get explained to them at discharge, laid out step by step.
Will It Actually Fit the House?
Almost nobody addresses this until the delivery driver is standing in the doorway with a bed frame.
Older homes on the Monterey Peninsula are charming and tight. Cottages in Pacific Grove, houses tucked into the hills in Carmel, bungalows in old Monterey. Many have doorways under 30 inches, sharp turns at the top of a staircase, and bedrooms on a second floor that a hospital bed is never getting to.
Walk the house before delivery day and check:
- Doorway width at every door the equipment must pass through, including the bathroom
- Turning space in hallways and at the top or bottom of stairs
- Whether the living room becomes the bedroom, which is the answer more often than families expect
- Where an oxygen concentrator can sit near an outlet without running a cord across a walking path
- A clear path wide enough for a walker, which usually means moving a rug, a side table, or both
Delivery timing matters too. Routes out to King City, Hollister, and the south county can stretch beyond a same-day window, so ask what the actual timeframe is rather than assuming the bed arrives the afternoon of discharge.
A safe layout is a big part of what makes staying home possible over the long run, not just for the first week.
Rent or Buy? It Comes Down to How Long the Need Lasts
The honest question is not which is cheaper. It is how long this equipment will be needed.
Recoveries after orthopedic surgery, a stroke, or a fall often run weeks, not years. Renting keeps a family from buying a hospital bed in March that sits in the garage by September.
And needs move in both directions. A walker becomes a wheelchair. A wheelchair becomes a hospital bed. Sometimes a person improves and the bed goes back.
Being able to swap or return items keeps the house matched to the person's condition right now instead of their condition last month. That flexibility matters most in the first few weeks, when things change fast. The first 72 hours of home health tend to reveal needs nobody predicted from a hospital bed.
Questions Worth Asking Before Anything Is Delivered
Families repeatedly describe being handed a plan at discharge and then having nobody to call when the pieces do not arrive. These are the questions that prevent that.
Ask the discharge planner, the supplier, or a plan representative:
- Who is the supplier, by name, and what is their direct phone number?
- Are they enrolled in Medicare, and will they accept assignment?
- Is this a rental or a purchase?
- Who services it if a motor fails or a rail sticks?
- Who picks it up when it is no longer needed, and is there a charge?
- What will we owe, and when will we see a bill?
Write the answers down. Get a name attached to each one.
If a physician referral is part of the picture, how the referral process actually works explains the paperwork side that often runs in parallel with the equipment order.
Frequently Asked Questions About Home Medical Equipment
Can I just buy a hospital bed online instead of going through all this?
You can, but Medicare will not pay for it. Coverage requires a provider's order and a Medicare enrolled supplier. If you buy retail, the full cost is yours, and you also give up service, swaps, and pickup when the need ends.
How fast can equipment show up after discharge?
It depends on the order, the supplier, and where you live. Homes on the Peninsula and in Salinas usually see faster routes than King City or Hollister. Ask for a specific delivery window rather than assuming same day, and confirm someone will be home to accept it.
Does the home health nurse bring the equipment?
No. Clinicians identify what is needed and document it, but delivery comes from the supplier. Those are two separate visits, often on different days, which is why families sometimes think something went missing when nothing actually did.
What if my parent's condition changes and the equipment no longer fits the need?
That is normal, and it is the main argument for renting. Equipment can often be swapped or returned as needs shift in either direction, so the house stays matched to the person's current condition.
Are supplies like bed pads and gloves covered the same way as the bed?
Not always. Disposable supplies are handled differently from durable equipment under Part B, and the rules shift again under the hospice benefit, where related supplies are included. Ask the supplier and your plan to spell out which specific items are covered before they arrive.
Still Sorting Out What Your Parent's House Needs?
Central Coast VNA & Hospice rents home medical equipment directly, including hospital beds, wheelchairs, walkers, crutches, scooters, and oxygen concentrators, with items that can be swapped or returned as a patient's condition changes. Home health teams across Monterey County include Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, chaplains, and volunteers who look at the home itself, not just the diagnosis. A care coordinator can walk through how equipment and coverage would work for your specific situation at 831-372-6668 or ccvna.com.

Someone Contacted Your Parent About Hospice. How Do You Check If It's Real?
The call comes on an ordinary Tuesday. Someone you have never heard of says they are following up about your mother's care, and they use her full name like they already know her.
Or there is a knock at the door. A woman says she is with the hospital and mentions a hospice home your family never discussed. That happened to a family in south Monterey County this year, and they wrote in because they did not know what to make of it. Another caller said it more plainly: they had no way to tell if the agency was real, or if the person who contacted them actually worked there.
That unease is worth taking seriously. But it is also something you can settle in one afternoon with three or four phone calls, and this guide walks through them in order.
First, Know How Home Health and Hospice Legitimately Begin
This is the single clearest test, and it screens out most of what families are worried about.
In California, home health and hospice care both start with a physician's order. A doctor who is treating your parent decides the care is appropriate, signs a referral, and sends it to an agency. Only then does anyone schedule a visit.
Roughly one in ten callers to local agencies do not know a doctor's referral is required first. That gap is exactly what enrollment schemes rely on.
So here is your first filter. No real agency will:
- Sign a patient up in a parking lot, at a health fair table, or over the phone
- Ask for a Medicare number, Social Security number, or bank information before an in-person assessment has been scheduled and confirmed
- Offer free groceries, gift cards, housekeeping, or transportation in exchange for signing paperwork
- Show up unannounced without your parent's doctor ever mentioning a referral
A legitimate first contact usually sounds boring. A scheduler calls to confirm an address and set a time for a nurse's evaluation visit, and they can name the referring physician without hesitating.

The Verification Sequence, Step by Step
Work through these in order. Each one takes a few minutes, and you can finish the whole thing in a single sitting.
1. Call the agency back on a number you found yourself. Do not use the number the person handed over or left on voicemail. Look the agency up on its own website or its Google Business Profile and dial that number instead. A fake operation cannot control what happens when you call the real one.
2. Ask for the staff member by full name and role. Say you were contacted by a person claiming to be their Registered Nurse, scheduler, or liaison, and ask the front desk to confirm that person works there. Real agencies answer this in under a minute.
3. Call your parent's treating physician's office. Ask directly whether they sent a home health or hospice referral, when, and to which agency. If the answer is no, you have your answer.
4. Check what has been billed. Log into your parent's account at medicare.gov, or read the most recent Medicare Summary Notice that came in the mail. You are looking for a home health or hospice claim nobody in the family authorized.
If something looks wrong, report it to 1-800-MEDICARE. California's Senior Medicare Patrol and HICAP counselors will also sit down with you and read a claim statement you do not understand, at no cost.
Who to Call and What to Ask
Keep this next to the phone. Four calls, four specific questions.
| Who You Call | What You Ask | What a Clean Answer Sounds Like |
|---|---|---|
| The agency, on its published number | Does a staff member by this full name work here, and in what role? | Yes, that is one of our Registered Nurses, and here is the referral we received |
| The treating physician's office | Did you send a home health or hospice referral for my parent, and to whom? | Yes, sent on this date to this agency, at the doctor's direction |
| Medicare, at 1-800-MEDICARE | Has a hospice or home health claim been filed under my parent's number? | A clear yes or no, plus how to dispute a claim you did not authorize |
| HICAP or Senior Medicare Patrol | Can you help me read this Medicare Summary Notice? | A free appointment with a trained counselor who walks the statement with you |
The Four-Call Check, in Order
A simple sequence a worried adult child can complete in one afternoon.

Why an Unauthorized Hospice Election Is Not Just Paperwork
This is the part families tend to underestimate.
Electing the hospice benefit is a voluntary choice that requires a physician's certification, and it changes how Medicare and Medi-Cal pay for care connected to the terminal condition. The California Department of Health Care Services explains that hospice election replaces normal coverage for services related to that condition.
So a parent enrolled without knowing it can discover that coverage for treatment they are still actively pursuing has quietly shifted underneath them. Chemotherapy, dialysis, a surgical follow-up: the billing rules change, and the family usually finds out at the worst possible moment.
That is why an enrollment nobody remembers agreeing to is worth chasing down the same week you find it, not after the next billing cycle. It is also worth understanding the difference between the programs before you assume the worst, because home health and hospice serve very different situations and a referral for one is not a referral for the other.
What Has Been Happening in California This Year
Some background helps explain why families are on edge, and why the answer is usually reassuring here on the Central Coast.
In April 2026, federal agents suspended 447 hospices and 23 home health agencies in the greater Los Angeles area over an estimated $600 million in alleged Medicare fraud. California has barred new hospice licenses since January 1, 2022, and on June 11, 2026 the California Department of Public Health filed the state's first full set of hospice licensing regulations after decades with no real operational rulebook behind a license.
Almost all of the enrollment schemes have been concentrated in Southern California. But phone calls and mailers do not respect county lines, and neither do the lists these operations buy.
For families in Monterey, Salinas, Seaside, King City, and Hollister, the practical takeaway is simple. An agency your parent has never heard of, contacting you first, deserves a second look. If you want the wider picture, we covered what the fraud crisis means for California families separately.
What an Established Local Agency Looks Like
This article is not about comparing agencies you are considering. It is about one situation: someone made contact first, and you need to confirm identity, confirm whether a referral exists, and confirm whether anything was billed. If you are further along and actually choosing, there is a separate process for vetting a provider.
Still, it helps to know what a long-standing organization looks like on paper. Look for how long the agency has served the area and who stands behind it.
Central Coast VNA & Hospice has operated here since 1951, became a Medicare-certified home health agency in 1963, and holds Joint Commission accreditation. Its board includes nursing leadership from local hospitals, and its clinicians, including Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, Chaplains, and Volunteers, are identifiable by name and role.
Staff identity can be confirmed by calling the main line at 831-372-6668 before anyone is let through the door. That is true of any reputable agency, and you should never feel awkward about asking.
Frequently Asked Questions About Hospice Enrollment Without Consent
Can someone enroll my parent in hospice without them signing anything?
They should not be able to. Hospice election is voluntary and requires a signed election statement plus a physician's certification. But enrollment fraud usually works by getting a signature under false pretenses, or by using a Medicare number obtained some other way, which is why checking the claims record matters even when nobody remembers signing.
My parent already gave out their Medicare number. What now?
Call 1-800-MEDICARE and report it, then check the Medicare Summary Notice or the medicare.gov account for claims your family did not authorize. A HICAP counselor can help you read the statement and file a dispute if something is there.
A hospital case manager called me about hospice. Is that a red flag?
No. Hospital case managers and discharge planners contact families about home health and hospice all the time, and that is a normal part of leaving the hospital. The difference is that the case manager works for a hospital you can call back, and the referral traces to your parent's treating physician. Verify the same way, just expect the answers to check out.
How quickly do I need to deal with this?
Within the same week. An unauthorized hospice election changes how care tied to the terminal condition is paid for, so the longer it sits, the more likely a family runs into a denied claim for treatment their parent is still receiving.
What if the person was legitimate and I offended them by checking?
You will not have. Every experienced agency in Monterey County fields identity verification calls, and a real Registered Nurse or scheduler expects them. If someone gets defensive when you say you want to call the main office first, that reaction is information.
Still Not Sure Who Contacted Your Parent?
If someone reached out about care for a parent in Monterey County and the story does not add up, a care coordinator can help you understand how a referral is supposed to arrive and what questions to ask next. Central Coast VNA & Hospice has answered questions like this from Central Coast families since 1951, and the main line is 831-372-6668.

It's 2 a.m. and Something Changes at Home. Who Do You Call?
It is the middle of the night. Your mother's breathing sounds different than it did at dinner, or your father just tried to stand and went down in the hallway. The office is closed and you are standing there with a phone in your hand, trying to decide between a number on a folder and 911.
This happens constantly across Monterey County. Roughly a third of families who call in are an adult child or spouse reaching out within hours or days of a discharge from Community Hospital of the Monterey Peninsula or Salinas Valley Health. One caller put it simply: she was just discharged and we need someone to come to the house.
The worry peaks on evenings and weekends, when nobody is around to explain what is normal. This guide covers who actually answers after hours, what counts as urgent enough to call at 2 a.m., and the exact words that get you help fastest.
Hospice After Hours and Home Health After Hours Are Not the Same Thing
Families mix these two up on the phone all the time, and the difference decides who picks up in the middle of the night.
Hospice includes access to a nurse by phone around the clock. If symptoms change, a Registered Nurse can talk you through it and can come to the house overnight when the situation calls for it. That is part of the Medicare hospice benefit, not an extra service you have to ask for. You can read how the benefit is structured directly from Medicare's own hospice coverage page.
Home health works differently. It is physician-ordered, intermittent skilled care: a nurse or therapist comes out on a set schedule to treat a wound, manage medications, or rebuild strength after surgery. There is an on-call clinician for urgent clinical questions after hours, but that person is not there to schedule visits or send supplies.
So at 2 a.m. on home health, an on-call nurse can help you decide whether a symptom needs the emergency room tonight. What waits until morning:
- Rescheduling or confirming a visit time
- Supply and equipment requests
- New orders from the physician
- Insurance and billing questions
- Adding a therapy discipline to the plan
If you are still sorting out which type of care your parent is actually on, this breakdown of home health versus hospice explains where the line falls.
Who Answers After Hours, and What They Can Do
A quick reference for the moment you are holding the phone and cannot remember which line to try.
| Situation | Hospice patient | Home health patient |
|---|---|---|
| Nurse available by phone overnight | Yes, around the clock | On-call clinician for urgent clinical questions |
| Nurse can come to the house overnight | Yes, when symptoms change | Not typically, visits are scheduled and physician-ordered |
| Sudden pain or breathing change | Call the on-call line first | Call the on-call line, be ready for a 911 recommendation |
| Supplies, scheduling, new orders | Business hours | Business hours |
| Chest pain, stroke signs, major fall injury | Call the on-call nurse, 911 if unsafe to wait | Call 911 |
What Actually Justifies a Middle of the Night Call
Families hesitate because they do not want to bother anyone. That hesitation costs more than the call does.
Call the on-call line when you see:
- A sharp jump in pain that the usual medication is not touching
- New shortness of breath or breathing that sounds different
- A fall, even if your loved one says they are fine
- A catheter or feeding tube that stops working or leaks
- Bleeding through a wound dressing that does not stop with pressure
- Sudden confusion in someone who was clear earlier that day
- A doubled or missed medication dose
These can usually wait for business hours:
- A visit time you want to shift next week
- Gauze, briefs, or equipment you are running low on but not out of
- A question about a bill or a Medicare statement
- Mild, familiar symptoms that have not changed in days
When you are unsure, make the call. An on-call Registered Nurse would rather spend four minutes ruling something out than hear about it two days later. And if the answer is genuinely 911, they will tell you plainly.

What to Say When You Call
Having these five things ready lets an on-call nurse sort out the problem in minutes instead of half an hour.

Give the Nurse Something to Work With
The call goes faster when you lead with facts instead of fear. That is not coldness, it is efficiency at an hour when minutes matter.
Say the pain number out loud. A 4 that jumped to a 9 in two hours tells a nurse something completely different than "she seems uncomfortable." Name what changed and when it started, down to the hour if you can.
Keep the medication list within arm's reach of the phone, not in a drawer. The nurse will ask what was given, how much, and at what time.
And if you reach voicemail, do not hang up. Families do this constantly and lose the entire night waiting for a callback that was never triggered. Leave:
- The patient's first name
- The city, such as Salinas, Seaside, or Gonzales
- What changed and when
- A callback number that someone will actually answer
- Whether a physician has already ordered care
If you are in the first days after a hospital stay and none of this is set up yet, the first 72 hours of home health explains what should be in place before the first weekend arrives.
Geography Changes the Math Out Here
In a dense city, the emergency room is ten minutes away and the decision is easy. Monterey County is not built that way.
A family in King City or Greenfield sits a long drive from the hospitals in Salinas or Monterey, and it gets longer at night on Highway 101. Families out past Hollister in San Benito County face the same stretch of road.
That distance matters more than people expect. A 1 a.m. ambulance ride can undo a comfort plan that took weeks to build, and it often ends with a night in a hallway, a set of tests, and a discharge back home by morning with nothing changed.
For a hospice patient, a call to the on-call nurse can frequently settle at home what an emergency room visit would not improve. Pain medication can be adjusted. A catheter can be flushed. Breathing can be managed with what is already in the house.
But some situations still call for 911. Chest pain, signs of a stroke, an injury from a fall, uncontrolled bleeding, or anything where waiting feels unsafe. Nobody will second guess you for making that call.
When Your Loved One Is Already on Service
About one in five after hours callers are relatives of a patient already receiving care. They are not in crisis. They are calling because a supply never showed up, a visit shifted without warning, or a symptom appeared that nobody explained in advance.
These calls deserve a straight answer too. Before you hang up, ask for three things:
- The name of the person who will call you back
- A specific timeframe, not "soon"
- Confirmation that your request was documented in the chart
That last one is the piece families skip, and it is the reason a request can vanish between shifts. Reviews reflect both sides of this. One family described visits that felt inconsistent and unannounced. Another wrote: "I appreciate everything that was provided to us from information on how to cope with a deteriorating health situation to who to contact 24/7 if more assistance was needed." That is David H., writing about his mother's care.
The difference between those two experiences usually comes down to whether the family knew who to reach and what to ask for. Write the after hours number on the refrigerator the day service starts. Not in your phone, on the refrigerator, where whoever is in the house at 2 a.m. can find it.
Frequently Asked Questions About After Hours Care at Home
Will a nurse actually come to the house overnight?
For hospice patients, yes, when symptoms change and a phone call is not enough. For home health patients, generally no. Home health visits are physician-ordered and scheduled, and the after hours clinician is there for urgent clinical questions rather than unscheduled visits.
If I call 911, does that end hospice care?
No. Calling 911 does not automatically remove someone from hospice. It can lead to treatments that work against the comfort plan, though, which is why a call to the on-call nurse first is usually worth the two minutes. If the situation is clearly an emergency, call 911.
My parent is not on hospice and not on home health yet. Who do I call at night?
Your first calls are the physician's answering service and, if the situation is serious, 911. Home health requires a physician order before anyone can come out, which is covered in more detail in how the referral process works.
Is after hours support included, or is it billed separately?
Under the Medicare hospice benefit, around the clock nurse access is part of the benefit rather than an add on. Home health coverage depends on your plan and your physician's orders. Medicare, Medi-Cal, and Veterans benefits all cover home based care differently, so ask a care coordinator to walk through your specific situation.
How long should I wait for a callback before trying again?
Ask for a timeframe when you call, then hold them to it. If 30 minutes pass on an urgent symptom with no callback, call again. And if the symptom is getting worse while you wait, do not keep waiting.
Questions About After Hours Support on the Central Coast
Central Coast VNA & Hospice is a nonprofit that has been making home visits in Monterey County since 1951 and marks 75 years in 2026, with more than 73,000 visits across the county in 2025. Care is delivered by nurses, therapists, social workers, chaplains, volunteers, and other clinicians, with a Care Team line staffed around the clock. Families with questions about what after hours support looks like can call 831-372-6668 or read more at ccvna.com.

When a Home Health Agency Says It Does Not Cover Your Parent's Address
You are standing in a hallway at a hospital in Salinas or Monterey. Discharge is set for tomorrow, the planner handed you an agency name, and you are on hold trying to get a nurse out to the house.
Then, three minutes into the call, you hear it. The address you are calling about sits outside that agency's coverage area. Now you are starting over, with a clock running.
Roughly one in twelve calls that come into a home health office are some version of "do you serve my area?" Too many of those callers find out mid conversation that the answer is no. This article is about checking coverage before that moment instead of after it.
A Service Area Is a Drive Time Line, Not a Marketing Choice
It helps to know what you are actually running into. A home health or hospice service area is an operational boundary, built around how far a clinician can drive and still make the rest of the day's visits.
Skilled home health is delivered by nurses and therapists who travel house to house. A single visit might take 45 minutes. Getting there and back can take twice that in this part of the state.
The boundary also has to hold up after hours. An agency will not promise coverage at an address it cannot reach with a nurse at 2 a.m. on a Sunday, because that promise would be hollow.
So when an intake coordinator says an address is out of area, it is rarely a brush off. It usually means:
- No clinician is currently staffed close enough to that address
- The drive would break the visit schedule for everyone else that day
- After hours response could not be guaranteed at that distance
- The specific therapy discipline you need is not staffed in that corridor
Understanding that changes how you ask. You are not negotiating. You are trying to find the agencies whose real footprint already includes your parent's street.
How a Home Health Agency Service Area Gets Drawn in Monterey County
The geography here makes coverage messier than in most metro areas. Agencies commonly list whole counties on their websites. A county listing does not always mean every address inside that county.
Monterey County alone runs from Pacific Grove and Carmel down through Salinas, Soledad, Greenfield and King City. A nurse driving south from Monterey to a King City address can spend well over an hour each way, and that is before the return trip.
Then there are the wrinkles families run into constantly:
- Big Sur, where the drive down Highway 1 is long, slow, and occasionally closed
- Carmel Valley Road, where the last ten miles take as long as the first twenty
- The far end of San Benito County past Hollister, out toward the ranch roads
- South Santa Clara County around Gilroy and Morgan Hill, which some agencies serve and others do not
Partial county coverage is normal, not a red flag. An agency that lists Santa Cruz County may reach some communities and not others. The same is true inside Monterey County.
This is also why zip codes are a poor way to check. Boundaries can split a zip code down the middle, and the person answering the phone needs the street, not the city.

Medicare Gives You More Leverage Than Most Families Realize
Here is a piece most families never hear at the bedside. When a provider decides a patient needs home health care, Medicare's home health coverage guidance says that provider should give the patient a list of agencies that serve the patient's area.
That same guidance says the provider must tell you if their organization has a financial interest in any agency on the list.
So you can ask for two things, plainly and without apology:
- The list of home health agencies that serve your parent's specific address, in writing
- Whether anyone on that list is there because of an ownership relationship
Most discharge planners will hand this over without blinking. It is a normal request. The written part matters because a name said out loud in a busy hallway gets lost by the time you are in the parking lot.
One name is not a list. If you were given a single agency and that agency turns out to be out of area, go back and ask for the rest. Plan network rules are a separate question, and worth reading up on if you are on an Advantage plan, but geography comes first.
Coverage Questions That Get Real Answers
Vague questions get vague answers. These are the ones worth reading off a piece of paper when you call.
| Ask this | Why it matters | What a clear answer sounds like |
|---|---|---|
| Read the full street address, not just the city | Boundaries can split a zip code or a road | Yes, that street is inside our footprint |
| Is that address covered for the specific service we need? | Home health and hospice footprints are not always identical | Home health yes, hospice we would need to check |
| Do after hours nurse visits reach that address? | Nights and weekends are when families panic | Yes, with a typical response window of X |
| Are Physical, Occupational and Speech Therapists staffed in that part of the county? | Therapy staffing is often thinner outside the Peninsula | PT and OT yes, speech therapy has a wait |
| If you cannot cover it, who can? | A good intake team should hand you names | Here are two agencies with phone numbers |
Check Coverage Before the Discharge, Not After
A short sequence families can run through while a hospital social worker is still available to help.
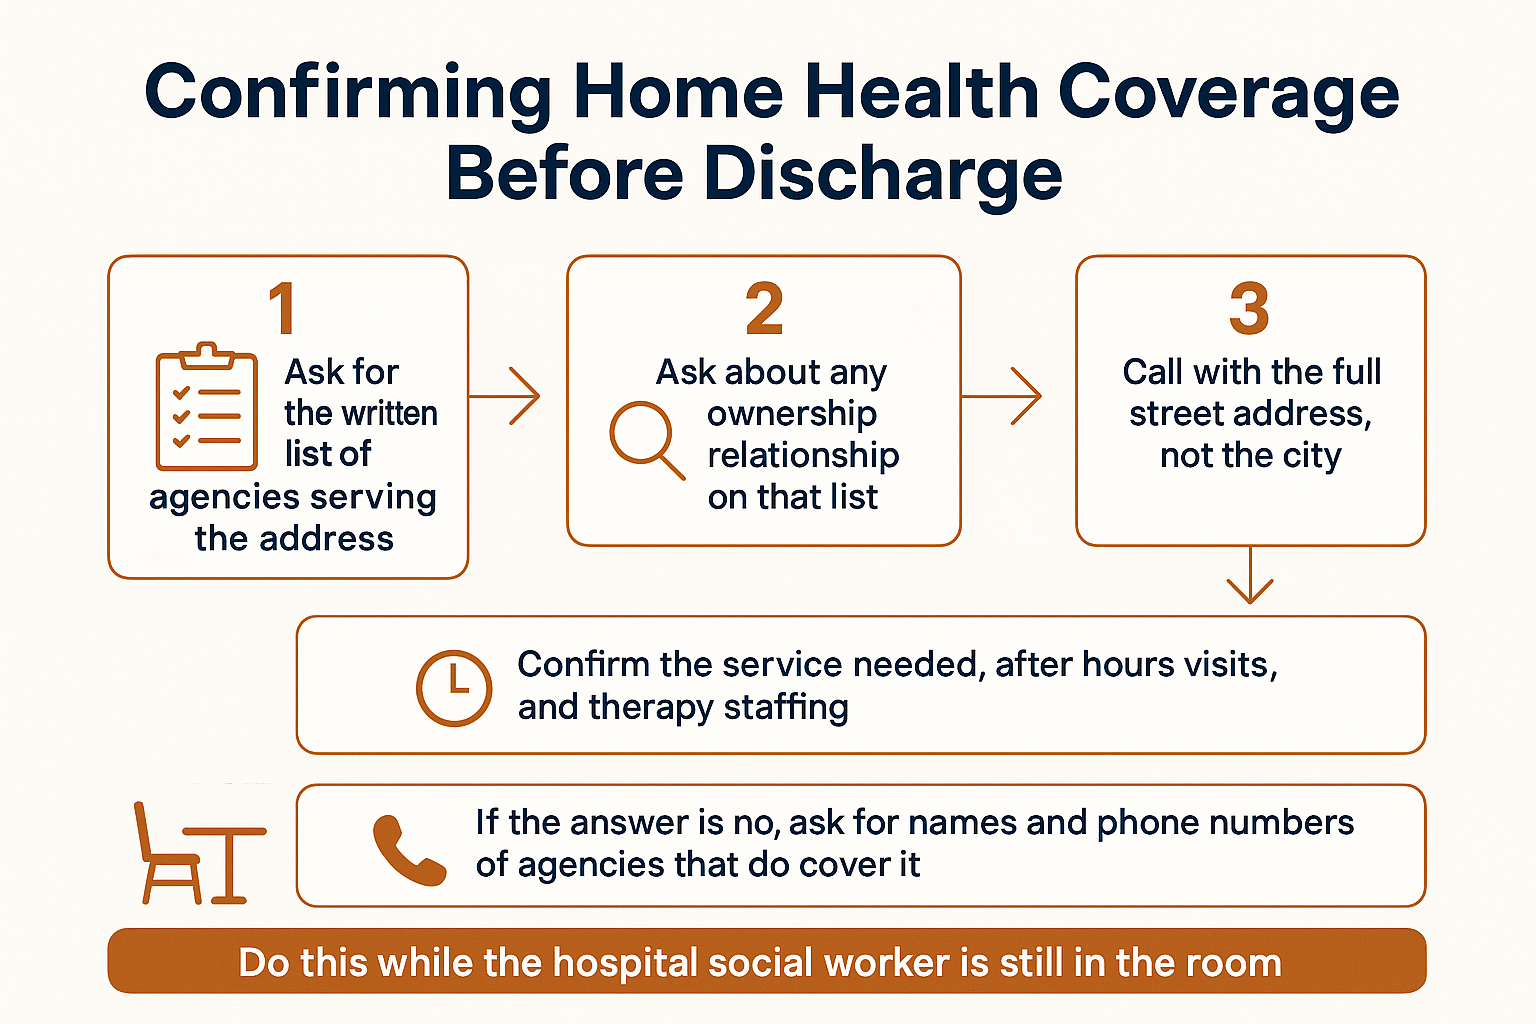
When the Answer Is No, Ask for Names Before You Hang Up
This is where families feel most stranded. The call ends, you have nothing new, and the discharge is still happening tomorrow.
A well run intake team should not simply decline. It should hand you names and phone numbers of providers who do cover that address. You are allowed to ask for exactly that, and most coordinators keep an informal list for this reason.
There is a second gap that comes up in almost every one of these conversations. Skilled home health visits are intermittent, meaning a few visits per week, not daily hands on help. A nurse might come twice a week and a Physical Therapist once or twice more.
For a parent in Greenfield or out past Hollister who needs help getting to the bathroom at 3 a.m., that clinical schedule alone will not carry the household. Families in outlying areas often combine a clinical team with separately hired private duty support or IHSS hours.
Private duty is paid differently, and the hours add up fast. One public review of a Monterey area experience described a family paying somewhere around $8,000 a month out of pocket for private aides, which gives a sense of scale, though rates vary widely by hours and agency.
Knowing that combination exists early spares families two weeks of confusion. It is worth reading how IHSS, home health and private duty each fit together before you start dividing up the week, and what visit schedules actually look like once care begins.
Do This While the Social Worker Is Still in the Room
One family described their situation in about as few words as it can be put. She was just discharged, and we need someone to come to the house.
That is the reality of these calls. They happen in the 24 to 72 hours after a discharge, not during calm planning at the kitchen table weeks ahead.
So the single most useful thing you can do is confirm coverage during the discharge planning meeting itself. The hospital social worker is in the room, has a phone, and can make calls on your behalf while everyone is together.
Ask them to verify the street address with the agency before the meeting breaks up. Ten minutes there saves a very bad afternoon later. If you want a sense of what else tends to get missed in that meeting, this walkthrough of what families overlook when planning a discharge to home covers the rest, and what the first 72 hours at home actually look like sets expectations for the days right after.
Why Some Organizations Reach Farther Than Others Here
Coverage on the Central Coast is often a matter of how long an organization has been operating outside the Monterey Peninsula.
Central Coast VNA & Hospice opened a Hollister office serving San Benito County in 1974. The Monterey Peninsula, Salinas Valley and San Benito visiting nurse organizations then merged into one nonprofit in 1984.
That history is why South County and San Benito coverage there is long established rather than newly added. Staffing in Salinas, King City and Hollister was built over decades, not stretched from the coast last year.
When care does reach the home, it is not one person. It is nurses, therapists, social workers, chaplains, volunteers and other clinicians working from the same plan. Families with a coverage question about a specific address can call 831-372-6668 or visit ccvna.com and ask before anything else gets decided.
Frequently Asked Questions About Home Health Coverage Areas
The discharge planner only gave me one agency name. Is that normal?
It is common, but you can ask for more. Medicare guidance says the provider ordering home health should give you a list of agencies serving the patient's area, and must disclose any financial interest in those agencies. Ask for that list in writing.
The agency lists my whole county. Does that mean my parent's house is covered?
Not always. Partial county coverage is common on the Central Coast, especially in Big Sur, upper Carmel Valley, and the far reaches of San Benito County. Read the full street address over the phone and get a yes or no on that specific address.
If they cover home health at our address, does that mean hospice too?
Not automatically. One organization's home health footprint and its hospice footprint are not always identical, because the staffing and after hours requirements differ. Ask about the service you actually need by name.
We need someone there every day. Will home health cover that?
Skilled home health is intermittent, usually a few visits per week from nurses and therapists. Families who need daily hands on help typically pair that clinical team with separately arranged private duty aides or IHSS hours. Naming that combination early saves a lot of frustration.
What if we are out of area and nobody will take us?
Call back and ask directly for referral names and phone numbers. Intake teams in Monterey County generally know which agencies cover King City, Greenfield, Gonzales and the outlying roads, and a good one will not leave you with nothing.
Have a Specific Address You Need Checked?
Coverage questions are easier to answer with a street address in hand than with a city name. Families anywhere from Pacific Grove to King City, Hollister, or the Gilroy side of the county line are welcome to call 831-372-6668 or visit ccvna.com and simply ask whether a given address is served. A care coordinator can tell you yes or no, and point you elsewhere if the answer is no.

IHSS, Home Health, or Private Duty: Who Does What When a Parent Needs Help
In one recent month, about a dozen calls came into a nonprofit home health line in Monterey from people who were actually trying to reach something else. They wanted IHSS. Or the Alliance on Aging. Or a Medi-Cal insurance plan. Or their parent's primary care office.
Those callers were not confused about wanting help at home. They were confused about which program does which job, and which phone number solves which problem.
So this is a map, not a pitch. Here is what home health, IHSS, and private duty each actually cover on the Central Coast, who pays for each one, how each door opens, and why most families in Monterey County end up using two of the three at once.
IHSS vs Home Health Care vs Private Duty: Three Different Jobs
The fastest way to sort this out is to stop thinking about companies and start thinking about tasks. Each program is built to handle a different kind of help.
- Home health is medical care ordered by a physician. Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, and Medical Social Workers come to the house on a visit schedule to handle wound care, medication management, chronic disease teaching, and rehab after surgery or a hospital stay.
- IHSS (In-Home Supportive Services) is a county-administered program that pays a provider, often a family member, to help a Medi-Cal recipient with bathing, dressing, meals, housework, and supervision so they can stay safely at home instead of moving into a facility.
- Private duty is an hourly home care agency or independent worker you hire and pay directly. Same kind of hands-on help as IHSS, no eligibility test, and the bill comes to you.
The dividing line is simple. If a task needs a nursing license or a therapy license, it lives under home health. If it is help with the ordinary business of getting through a day, it lives under IHSS or private duty.
If you are still deciding whether home is the right setting at all, the difference between needing help and needing a facility is the question to settle first.
"We Need Daily Care, Not Just a Few Visits a Week"
This is one of the most common things families say on a first phone call, and it is worth answering plainly.
Skilled home health under Medicare is intermittent. That means visits, not shifts. A nurse might come twice a week for a few weeks, a Physical Therapist might come three times a week during rehab, and a Medical Social Worker might come once to sort out resources. Nobody stays through the day.
That is not a limitation an agency invented. It is how the benefit is written, and it is why skilled nursing care at home is different from what most people picture.
So when the real need is somebody there at 7 a.m. to help Dad shower, somebody making lunch, and somebody nearby in the afternoon so he does not fall getting up from the recliner, that is IHSS or private duty work, not home health work.
Most families in Salinas, Seaside, and Carmel end up running both at the same time:
- The home health team manages the medical side: wounds, new medications, blood pressure, therapy goals, coordination with the doctor.
- The IHSS provider or private aide covers the hours in between: bathing, dressing, meals, laundry, supervision.
One program does not replace the other. They are stacked.

How Each Door Actually Opens
The sequence matters most in the days right after a hospital discharge, when everyone is tired and the clock feels loud.
Home health starts with a physician order. A doctor has to order the care, and the agency then checks coverage before scheduling anything. About one in ten callers does not know this, and that gap delays intake. Some families give up entirely at that point, which is a shame, because the order is usually a single phone call to the discharging doctor. The full picture is here: why a physician referral is required for home health.
IHSS starts with an application through county social services. Monterey County, San Benito County, and Santa Cruz County each run their own intake. After the application comes a functional needs assessment, and applicants should expect an interview and, in some cases, a home visit or a virtual assessment. Hours are then authorized by task, which is why two people with the same diagnosis can end up with very different weekly totals.
Private duty starts with a phone call and an hourly rate agreement. No physician order, no eligibility test. That is why it is usually the fastest option, and also why it is the one families pay for out of pocket.
If the discharge already happened, the first 72 hours of home health after a hospital stay walks through what should be happening right now.
Three Doors, Three Starting Points
A quick look at how each type of help gets approved and how fast it typically moves.
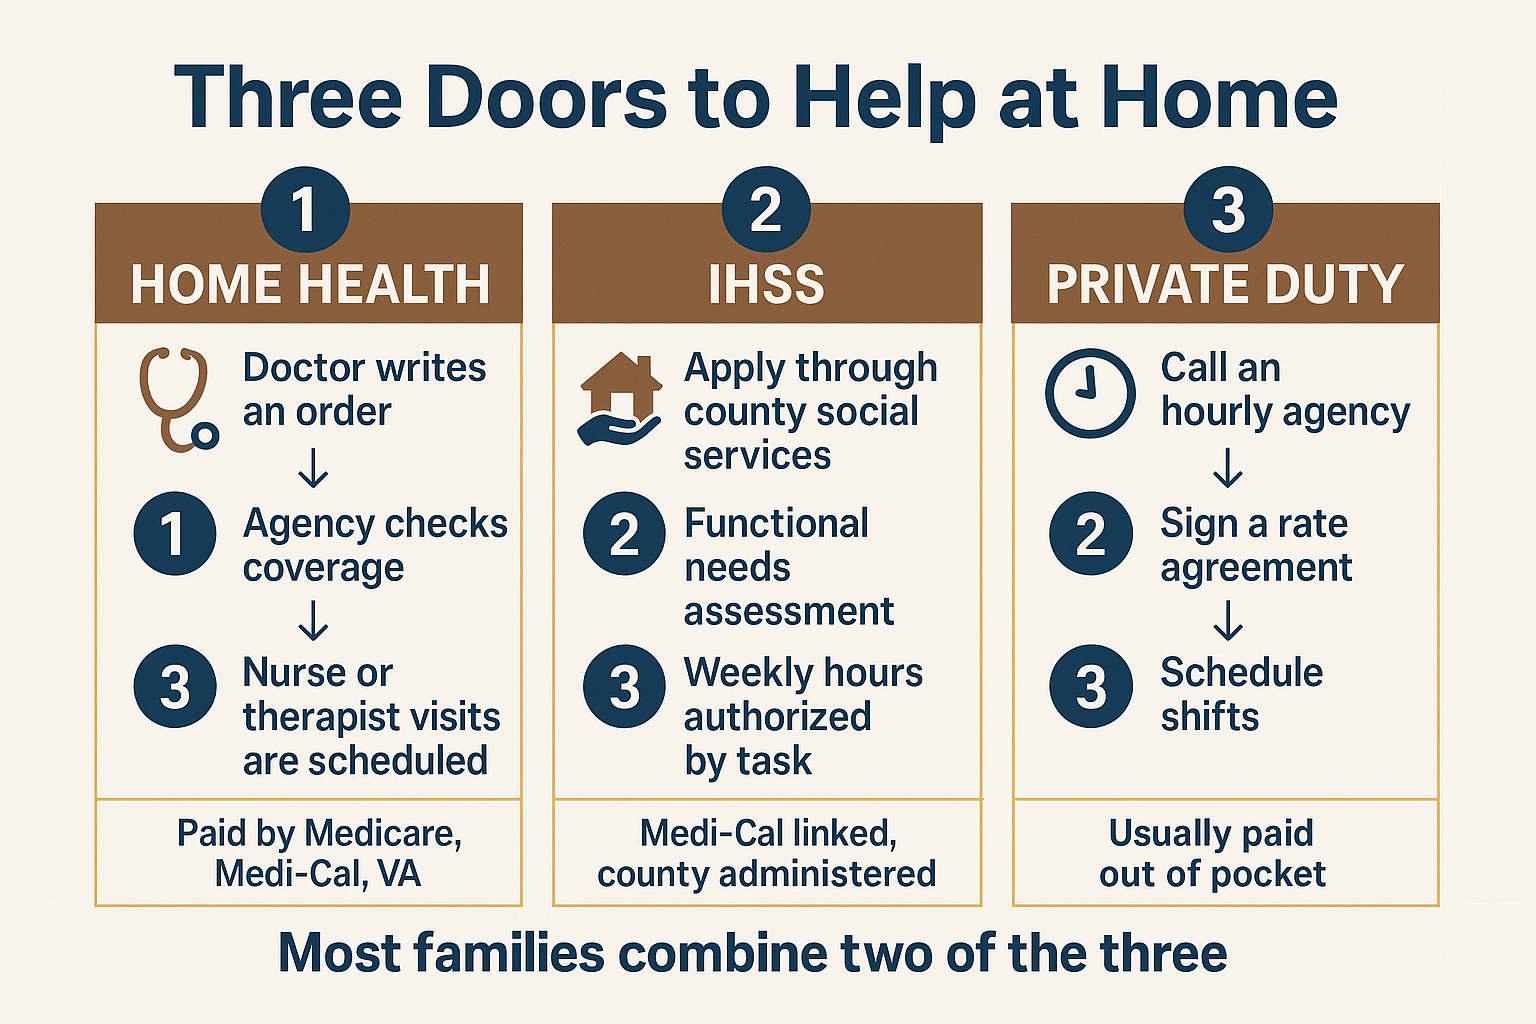
Side by Side: Who Authorizes, Who Pays, What You Get
Here is the same information in one place, for the moment when you are on the phone and trying to figure out whether you are talking to the right office.
| Home Health | IHSS | Private Duty | |
|---|---|---|---|
| What it covers | Skilled nursing, wound care, medication management, physical, occupational, and speech therapy, medical social services | Bathing, dressing, meals, housework, errands, supervision | Bathing, dressing, meals, companionship, overnight or live-in coverage |
| Who authorizes it | A physician, plus a coverage check by the agency | County social services after a functional needs assessment | You do, by signing a rate agreement |
| Who pays | Generally Medicare, Medi-Cal, or Veterans benefits | Medi-Cal funded, county administered | The family, out of pocket, unless long-term care insurance applies |
| Schedule | Intermittent visits set by the care plan | Authorized hours per week, spread as needed | Hourly shifts you choose |
| Typical start time | Days, once the order is in hand | Weeks, because of the assessment step | Often the fastest of the three |
What Actually Drives the Cost of Daily Help
Nobody can quote you a real number over the internet, and anyone who does is guessing. But the factors that move the number are the same for every family on the Peninsula.
- Hours per week. A few mornings a week and around-the-clock coverage are not the same product.
- Overnight and live-in arrangements. These are priced differently than daytime hourly help.
- Weekend and holiday rates. Many agencies charge more for both.
- Whether the person is on Medi-Cal. If they are, IHSS hours may cover a meaningful share of what the family would otherwise pay for privately.
The strain is real. In a public review, a Monterey area family described paying roughly $8,000 per month out of pocket for personal care and noted that with Medicaid coverage it would have been free. That is one family's situation, not a market rate, but it shows how quickly private hourly care adds up when someone needs hands-on help through the whole day.
Home health lands very differently at the mailbox. Physician-ordered home health visits are generally covered by Medicare, Medi-Cal, and Veterans benefits, which is why the two categories feel so unlike each other financially even though the person walks through the same front door.
What Changed Going Into 2026
Rumors move fast in caregiver groups, so it is worth being precise about the three changes that touch this decision.
IHSS provider wages went up in many California counties on January 1, 2026, with pay moving toward a $20 per hour floor statewide. That helps IHSS providers, and it also nudges private-duty market rates upward, since both draw from the same local labor pool in Monterey and Salinas.
Medi-Cal asset limits are being reinstated starting January 1, 2026, after California eliminated them for many programs in 2024. If somebody told your parent years ago that they would not qualify, that answer may be out of date in either direction. Verify current rules with the county rather than assuming.
And the enacted 2026-27 state budget kept the IHSS Backup Provider System in place and did not adopt the proposed Medi-Cal-linked termination change. The program is projected to serve roughly 875,000 people in fiscal year 2026-27. If you want the underlying detail, the Legislative Analyst's Office published a full analysis of IHSS in the 2026-27 budget.
Ask About Your Town, Not Your County
Roughly 8 percent of callers ask whether their address is covered, and some learn mid-call that it is not. That is avoidable, because boundaries work differently for each program.
IHSS is county-administered. Monterey County, San Benito County, and Santa Cruz County each run separate intake, with their own phone numbers and their own timelines. Where your parent lives decides which office handles the application.
Medicare-certified home health agencies each have their own footprint. A footprint may include the Monterey Peninsula, Salinas, King City, and Hollister without including every address in between. Greenfield, Marina, and the ranch roads south of King City are exactly where this gets uncertain.
So on the first call, give the specific town or ZIP code, not the county name. And if the answer is no, ask for a referral to a provider who does cover that address. A good intake person will have names ready.
Who to Call for What on the Central Coast
Here is the short list worth taping inside a kitchen cabinet.
- County social services in Monterey, San Benito, or Santa Cruz County for an IHSS application and needs assessment.
- The Alliance on Aging in Monterey County for benefits questions and free Medicare counseling.
- The local Medi-Cal plan for case management questions and covered services under the plan.
- Community nonprofits running Meals on Wheels and volunteer transportation, for the gaps no clinical program fills.
- A home health agency once you have the physician order in hand.
The person who usually untangles all of this for a family is a Medical Social Worker. They are part of the home health team alongside nurses, therapists, chaplains, volunteers, and other clinicians, and their job includes knowing which local office handles what.
One local family, in a five-star review, credited the Medical Social Worker on their mother's home health team with helping them cancel out-of-state Medicaid coverage and pointing them toward community resources they had not known existed. That kind of help does not show up on a service list, but it is often the thing families remember.
If the person doing all the daily lifting right now is you, respite care for family caregivers is worth reading before you hit the wall.
Frequently Asked Questions About IHSS vs Home Health Care
Can my parent have IHSS and home health at the same time?
Yes, and many families do exactly that. The programs are funded and authorized separately, so IHSS hours cover bathing, meals, and daily supervision while a physician-ordered home health team handles nursing, wound care, and therapy. Neither one cancels the other out.
Do I need a doctor's order for IHSS too?
No. IHSS runs on a county functional needs assessment, not a physician order. A doctor's input can support the application, but the county caseworker makes the hours determination. Home health is the one that cannot begin without an order.
How long does IHSS take to start compared to home health?
IHSS generally takes longer, because the application has to be processed and a needs assessment scheduled, which can mean weeks. Home health can often begin within days once the physician order and coverage check are complete. Private duty is usually the quickest, which is why some families bridge the gap with paid hours while an IHSS application is pending.
What if my parent does not qualify for Medi-Cal?
Then IHSS is likely off the table, and hands-on daily help would come from a private-duty agency paid out of pocket. Physician-ordered home health visits are a separate question and are generally covered by Medicare or Veterans benefits regardless of Medi-Cal status. And since asset rules changed again in January 2026, an old denial is worth rechecking with the county.
Does home health cover a home health aide for bathing?
Some aide support can be part of a home health plan when it is tied to skilled care already in place, but it is limited and scheduled, not daily shift coverage. If the real need is help every morning and evening, that is IHSS or private duty territory.
Still Not Sure Which Program Fits Your Family?
Central Coast VNA & Hospice has been a nonprofit serving Monterey County and the surrounding Central Coast since 1951, reaching 75 years in 2026, with teams of Registered Nurses, Licensed Vocational Nurses, therapists, Medical Social Workers, Chaplains, and Volunteers, and it accepts Medicare, Medi-Cal, and Veterans benefits. A care coordinator can help you sort out which program handles which part of the need before anything is scheduled, including pointing you toward the county or community office that actually handles your question. You can reach the team at 831-372-6668 or read more at ccvna.com.