

Speech Therapy at Home: What It Covers and Who Qualifies
Most families picture the same thing when they hear speech therapy: someone practicing words that came out wrong. That picture is only a small slice of what a Speech Therapist actually does in the home.
After a stroke, a head or neck surgery, or a long hospital stay, the harder problems are often invisible from across the room. Trouble swallowing safely. Forgetting the steps of a task. Losing the thread of a conversation halfway through.
Families across Monterey County call about this after a discharge from Community Hospital of the Monterey Peninsula, Salinas Valley Health, or Natividad, usually with two questions: does Medicare cover it, and do we need a doctor's order first. This guide answers both, and explains what speech therapy at home actually covers after a stroke or surgery.
What speech therapy at home actually covers after a stroke or surgery
A Speech Therapist, also called a speech-language pathologist, works on three broad areas in the home. Speech is only one of them.
- Swallowing safety (dysphagia). Coughing during meals, a wet or gurgly voice after drinking, food that seems to stick, or unexplained weight loss.
- Communication. Slurred words, trouble finding the right word, difficulty understanding what others say, or a voice that has gone weak and quiet.
- Thinking and memory (cognition). Losing track of medications, repeating questions, trouble sequencing daily tasks, poor safety awareness after a fall or a head surgery.
That third one surprises people. A patient in Pacific Grove who can hold a normal conversation may still be unable to reliably remember whether they took their morning pills.
That is a speech therapy problem, and it is also a safety problem. It is one reason therapy visits are usually coordinated with a Registered Nurse who is already managing medications in the home.
Speech therapy in the home is part of a physician-directed plan, the same way skilled nursing care at home works. Visits are intermittent, goal-based, and reassessed as the patient improves.

The swallowing problem families almost never see coming
Of everything a Speech Therapist handles at home, swallowing difficulty carries the highest stakes. When food or liquid goes down the wrong way, it can settle in the lungs and cause aspiration pneumonia, which sends patients right back to the hospital.
It often shows up quietly. A parent starts eating less. Meals take twice as long. They stop drinking water because it makes them cough. According to the National Institute on Deafness and Other Communication Disorders, swallowing problems commonly follow stroke and other nervous system conditions, and they can lead to poor nutrition and dehydration.
What a Speech Therapist does about it in the home:
- Evaluates how the patient handles different food textures and liquid thicknesses
- Teaches positioning and swallowing techniques that reduce risk
- Recommends diet changes, cup types, and pacing that the family can actually follow
- Trains family members on what warning signs mean a call to the nurse
Families frequently do not realize this is a skilled clinical concern at all. They treat it as picky eating, and then the pneumonia arrives three weeks later.
What Families Notice vs. What a Speech Therapist Is Looking At
The same everyday observation can point to a very different clinical issue. Here is how common household signs line up.
| What the family notices | What it may actually be | What therapy addresses |
|---|---|---|
| Coughing or throat clearing during meals | Unsafe swallow, aspiration risk | Swallow techniques, texture and liquid changes, positioning |
| "He just doesn't talk much anymore" | Weak voice or word-finding difficulty after stroke | Voice strength, language exercises, communication strategies |
| Missed or doubled medications | Memory and sequencing changes | Cognitive strategies, written routines, safety cues |
| Repeating the same question | Short-term memory loss after surgery or illness | Memory supports the family can maintain between visits |
| Eating less, losing weight | Fear of choking, fatigue while chewing | Meal pacing, calorie-dense soft foods, endurance work |
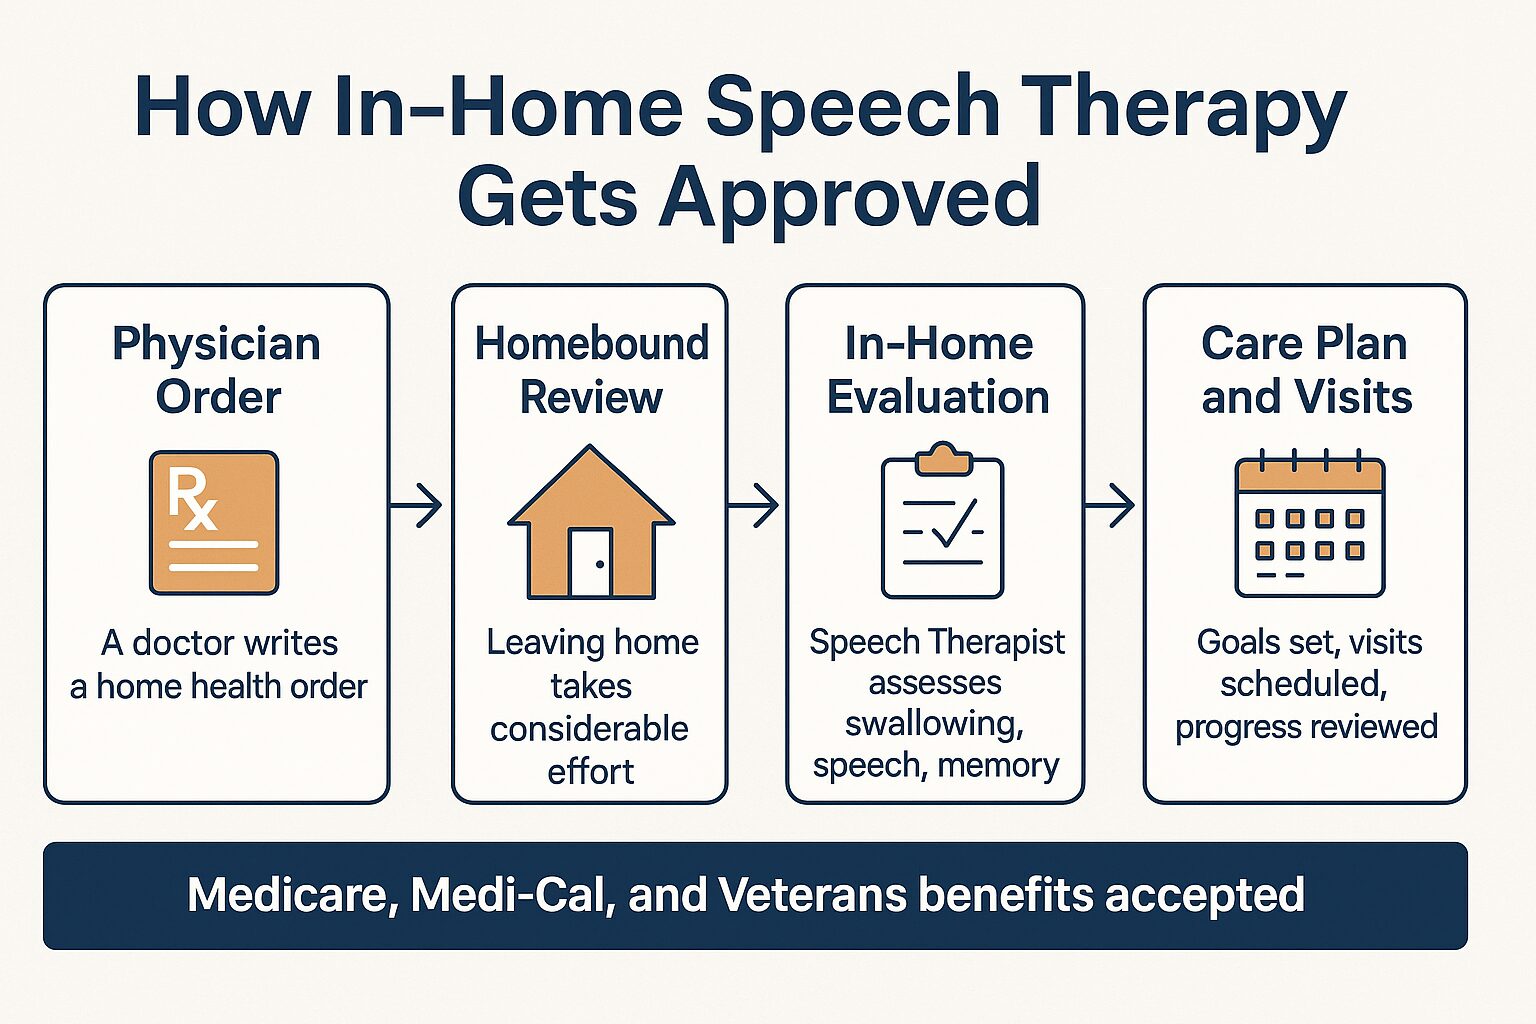
The Qualifying Path in Four Steps
Most families get stuck on the referral step. This is the order things actually happen in.
Who qualifies, and what "homebound" really means
To get speech therapy at home under Medicare, a patient generally needs two things: a physician order and to meet the homebound requirement. Those are the same conditions that apply to skilled nursing and physical therapy.
The homebound standard is where families count themselves out too early. It does not mean the patient can never leave the house. It means leaving takes a considerable and taxing effort, or that they need help or a device to do it.
Someone in Salinas who can get to a Sunday church service with a walker and a family member's arm may still qualify. Someone recovering from head and neck surgery who tires after twenty minutes upright may qualify too.
A few practical notes:
- Medicare, Medi-Cal, and Veterans benefits are all accepted for home health services here
- The order can come from the hospital physician at discharge or from the primary care doctor later
- Home health does not cover ages 0 to 21, maternity diagnoses, or primary behavioral health conditions
If the rules feel murky, a Registered Nurse or care coordinator can walk through the specific situation. The guidelines are more flexible than most families assume, which is also true of Medicare coverage for physical therapy at home. And if you are unsure how the order gets written, this explanation of the physician referral process covers it step by step.
Why the kitchen beats the clinic room
A clinic can simulate a meal. A home does not have to.
When a Speech Therapist sits down in a patient's own King City or Hollister kitchen, they are working with the actual cups in that cupboard, the actual chair height, the food that family actually cooks. Swallowing strategies get practiced with dinner, not with a demonstration.
The same holds for memory work. Cues get placed on the real pill organizer, on the real calendar, in the room where the patient will use them at 7 a.m. tomorrow.
One family on the Peninsula described the team that came to their home as nurses, physical therapists, and a Medical Social Worker who each evaluated a different piece of the picture, then built one plan. That coordination between nurses, therapists, social workers, chaplains, volunteers, and other clinicians is the point of home-based care.
Progress made in the room where the patient lives tends to stick. There is no gap between the exercise and real life.
Asking for an evaluation is not a commitment
Plenty of families wait because they are not sure the problem is "serious enough" to bother anyone about. That hesitation costs weeks.
A formal evaluation gives you information, not an obligation. A Speech Therapist can tell you what is present, what is not, which goals are realistic, and roughly how many weeks a course of therapy might run.
Sometimes the answer is that no therapy is needed and the family can stop worrying. Sometimes the answer changes the meal plan that night. Either outcome is better than guessing.
If a discharge is coming up soon, it is worth reading what families often miss when planning a hospital discharge to home, because the speech therapy question is one of the most commonly skipped items on the list.
Frequently Asked Questions About In-Home Speech Therapy
Does Medicare cover speech therapy at home, and what will we pay?
Medicare covers speech-language pathology as part of the home health benefit when the patient meets the homebound requirement and has a physician order. For eligible patients, the covered home health visits themselves typically come with no coinsurance, though durable medical equipment is usually billed separately at a percentage. Coverage details depend on the plan, so ask a care coordinator to review the specific situation before assuming anything.
Do we need a doctor's order first, or can we just call and schedule?
A physician order is required before a visit can be scheduled. This is the single most common point of confusion on incoming calls. The hospital physician can write it at discharge, or the primary care doctor can write it afterward.
My mother's speech is fine. Is speech therapy still relevant?
Often yes. Swallowing difficulty and memory or sequencing problems fall under speech therapy even when the patient speaks clearly. If she is coughing at meals, losing weight, or mixing up medications, an evaluation is worth requesting.
How many visits does in-home speech therapy usually involve?
It varies with the diagnosis and goals. Home health is intermittent, meaning scheduled visits rather than daily coverage, and the plan is reassessed as the patient progresses. A Speech Therapist can give a realistic estimate after the initial evaluation.
We need someone in the house every day. Is that what this is?
No, and this comes up often. Home health provides skilled clinical visits, not around-the-clock personal care. Many families pair home health with a private-duty agency for daily hands-on help, and a care coordinator can point you toward local options for that piece.
Still Unsure Whether a Speech Therapy Evaluation Makes Sense?
If someone you love is coughing at meals, forgetting medications, or struggling to be understood after a stroke or surgery, a conversation costs nothing but a few minutes. Central Coast VNA & Hospice has provided home-based care across Monterey County and the surrounding Central Coast since 1951, and a care coordinator can talk through whether an in-home evaluation fits your situation. You can reach the team at 831-372-6668 or read more at ccvna.com.

How Families in Monterey County Can Vet a Hospice Provider
The moment usually arrives on a hard day. A physician sits down with your family and explains that treatment is no longer working, and someone hands you a name and a phone number for hospice.
Most families accept that first name. It feels like the only option, and nobody has the energy to shop around. But a referral from a discharge planner or a physician is a starting point, not a vetted recommendation.
This guide walks through the questions families in Monterey County can ask in a single phone call. Six steps, each with a concrete answer you can actually judge.
Step 1: Treat the referral as one option, not the decision
Hospital discharge planners at hospitals across the Monterey Peninsula and Salinas Valley are doing their job, and they are usually doing it fast. They pass along providers who are in-network and accepting patients.
That list is not a quality ranking. You are allowed to ask for more than one name, and you are allowed to call a provider your family found on its own.
Here is what to do before you say yes to anyone:
- Ask the discharge planner for two or three hospice names, not one
- Ask whether the hospital has any financial relationship with the provider
- Write down the questions in this guide and ask each provider the same ones
- Give yourself 24 to 48 hours if the clinical situation allows it
One more practical note for families in King City, Greenfield, or out toward Big Sur: ask directly whether the provider actually staffs your area. Several callers each month learn mid-conversation that a provider's map stops well short of their driveway. Coverage on paper and a nurse who can reach you in 40 minutes are two different things.
Step 2: Ask if they are Medicare-certified, and whether they are nonprofit
Start with Medicare certification. Every legitimate hospice serving Monterey County is certified, so this is a floor requirement rather than something that sets a provider apart. If a provider hesitates on this question, end the call.
You can verify certification and see patient survey results yourself through Medicare's Care Compare tool, which lists hospices by ZIP code.
The more revealing question is the funding model. Nonprofit hospice organizations return their resources to patients and the community. For-profit hospices answer to investors.
That difference shows up in ordinary ways: staffing ratios, how long a nurse stays in the room, whether a Chaplain drives to Carmel Valley at 10 p.m. because it is the right thing to do.
California has also seen a real problem with fraudulent hospice operations, mostly concentrated in Southern California but worth understanding anyway. If you want the background, read about California's hospice fraud crisis.
A quick safety note families here have raised: a legitimate provider will never ask for personal or financial details before an in-person assessment is scheduled. If someone shows up unannounced claiming to represent a hospice, call the agency's main number and confirm.

Step 3: Make them name every person on the team
Hospice is not one nurse who visits twice a week. A credible program should be able to name each member of the interdisciplinary team without pausing to think about it.
Ask who will actually come to the house. The full team should include:
- Registered Nurses for pain and symptom management
- Hospice Aides for bathing, grooming, and personal comfort
- Medical Social Workers for paperwork, benefits, and family conflict
- Chaplains for spiritual support, regardless of faith or lack of one
- Bereavement Specialists for the months after a death
- Volunteers who sit with patients so family members can sleep or run errands
If a provider is vague about Chaplain availability, or does not bring up bereavement follow-up on their own, treat that as a real gap. Families across Monterey County have been caught off guard by programs that sent a nurse but had no one else behind her.
Ask how often each person visits, and ask whether visit schedules are set in advance. Inconsistent, unannounced arrivals are one of the most common complaints families raise about hospice care anywhere, and a provider who cannot describe a schedule probably does not keep one.
Step 4: Ask what happens at 2 a.m.
This is the single most useful question on the list, because the answer is concrete and easy to judge.
Ask it plainly: if my mother has a pain crisis at two in the morning, what happens?
A solid answer sounds like this. You call one number, a clinician answers, and that person can either talk you through a medication adjustment or send a Registered Nurse to the house that night.
A weak answer sounds like this. An answering service takes a message, and someone calls back during business hours.
Follow up with:
- Is the after-hours line staffed by a nurse or by a message service?
- How long does a night visit typically take to arrive in my area?
- Who covers weekends and holidays?
- What medications will already be in the house for a crisis?
Nights are when families feel most alone. A provider that has thought this through will answer in fifteen seconds without checking with a supervisor.
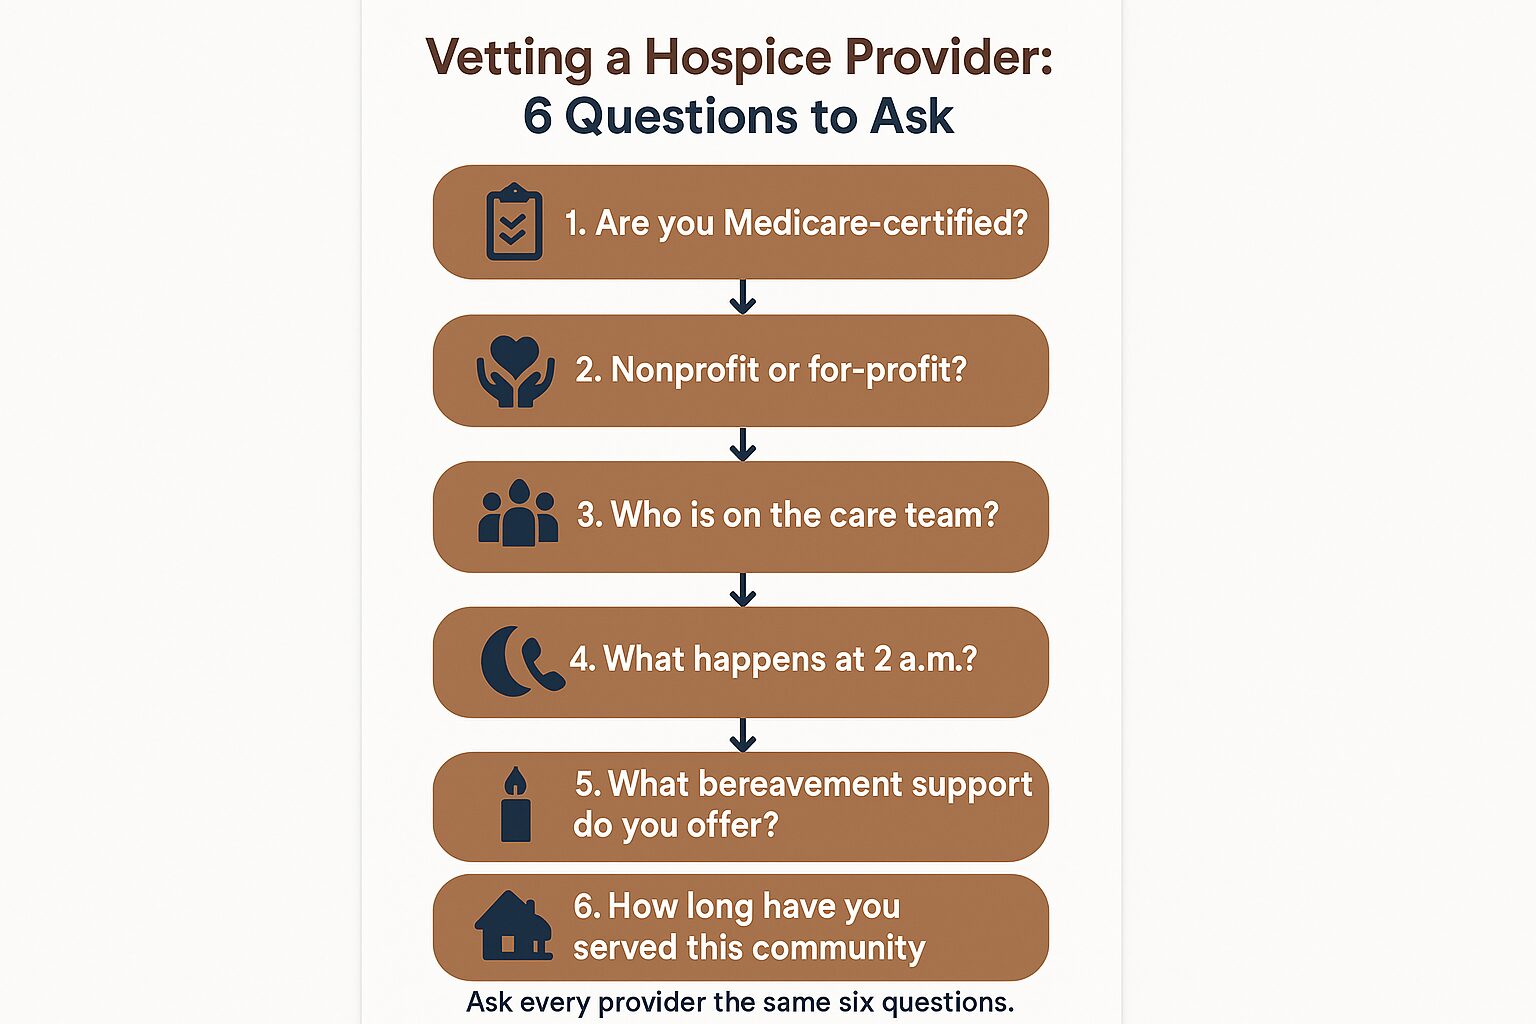
Six Questions and What the Answers Should Sound Like
Use this as a phone script. Ask every provider the same questions and compare the answers side by side.
| Question to ask | A solid answer | A warning sign |
|---|---|---|
| Are you Medicare-certified? | Yes, with a certification number they will share | Hesitation or a vague yes |
| Nonprofit or for-profit? | A direct answer either way, with an explanation | Deflection or confusion |
| Who is on the care team? | Names every role, including Chaplain and Volunteers | Only nurses are mentioned |
| What happens at 2 a.m.? | A 24/7 clinical line that can dispatch a nurse | An answering service takes a message |
| What does bereavement look like? | Months of support, groups and one-on-one counseling | A single follow-up phone call |
| How long in this community? | A specific number of years and local references | Recently opened, no local history |
The Six-Question Vetting Call at a Glance
Print this or keep it on your phone. The whole conversation takes about fifteen minutes per provider.
Step 5: Ask about grief support before you think you need it
Bereavement is the part families skip during the vetting call and regret skipping six months later.
Ask what happens after your loved one dies. Real grief support means ongoing counseling and support groups over a period of months, not one sympathy call and a mailed pamphlet.
A second question worth asking: does the provider offer grief support to people in the community who were never hospice patients? A steady stream of calls comes in from Monterey and Pacific Grove residents who lost a spouse through a different provider and have nowhere to turn afterward. One recent message came from a woman whose husband of more than fifty years had died the day before, asking simply for a group she could attend nearby.
Providers who keep the door open to the wider community tend to be more invested in the whole family experience. If you want a sense of what this looks like in practice, here is what grief support after hospice actually involves.
Step 6: Check local history, because reputation here is evidence
The Monterey Peninsula is small. A provider's actual record travels through churches, senior communities, and physician offices faster than any marketing campaign.
A hospice that has operated continuously in Monterey County, San Benito County, and the surrounding communities for decades leaves a trail you can follow:
- Ask your loved one's primary physician which programs they trust
- Ask neighbors and friends who have been through it recently
- Check licensing and complaint history through the California Department of Public Health
- Read reviews, including the critical ones, and see whether the provider responds
Read negative reviews carefully rather than dismissing them. A pattern of complaints about scheduling or communication tells you something. A single hard review with a thoughtful reply tells you something different.
Also be clear on what you are actually choosing. Many families call about hospice when what they need right now is home health or palliative care. If that line is still blurry, this comparison of home health and hospice sorts it out, and the eligibility question most families are afraid to ask covers timing.
Frequently Asked Questions About Choosing a Hospice Provider
Do we need a doctor's order before hospice can start?
Yes. Hospice requires a physician certification that the illness is expected to run its course within about six months if it follows its usual path. This is the step that surprises families most often and the one that delays admission. You can call a provider first and start the conversation while the order is being arranged.
Does Medicare cover hospice, and what does it actually pay for?
The Medicare hospice benefit generally covers the care team's visits, medications related to the terminal illness, medical equipment such as a hospital bed, and supplies. Small copayments can apply to some outpatient prescriptions and inpatient respite stays, and coverage details vary by situation. Medi-Cal and Veterans benefits also cover hospice. Ask any provider you call to walk you through the specifics for your loved one.
Can we switch hospice providers if it is not working?
Yes. Medicare allows you to change hospice providers once during each benefit period, and doing so does not end the benefit. If visits are inconsistent, calls go unanswered, or the team is not a fit, you are not stuck.
How quickly can hospice start after a hospital discharge?
Often within a day or two once the physician order is in place, and sometimes the same day for urgent situations. When you call, say plainly that the patient is being discharged and needs someone at the house. That changes how the intake conversation is handled.
Does hospice mean we are giving up on treatment?
No. Hospice shifts the goal from curing the disease to caring for the whole person, including pain relief, emotional support, and spiritual care. Families often describe it as the point where their loved one finally got comfortable. If curative treatment is still on the table, palliative care may be the better fit right now.
Questions About Hospice Care on the Central Coast?
If you are working through these questions for a parent or spouse in Monterey County, San Benito County, or South Santa Clara County, you are welcome to ask them of us the same way you would ask any other provider. Central Coast VNA & Hospice has served families here since 1951, and a care coordinator can talk through options, eligibility, and Medicare or Medi-Cal coverage without any pressure to decide. The number is 831-372-6668.

Summer Heat and Smoke on the Central Coast: What Home Patients Need to Know
It usually starts with a phone call. A daughter in Pacific Grove, wearing a sweatshirt in 62-degree fog, calls her father in Salinas and finds out his house has been sitting at 94 degrees since noon.
That gap between the coast and the valley is one of the most misunderstood health risks in Monterey County. And when wildfire smoke drifts in on top of the heat, a patient managing serious illness at home is dealing with a medical situation, not a weather annoyance.
This guide covers what heat and smoke actually do to a seriously ill person at home, which medications make it worse, and the handful of questions families should answer before the next advisory shows up on their phone.
Why heat hits inland patients harder than coastal ones
Monterey County is really two climates. Coastal Monterey, Pacific Grove, and Carmel often stay in the 60s through summer, while Salinas, Gonzales, Soledad, and King City can push into the 90s and past 100.
A lot of seriously ill patients live in those hotter inland communities. Their adult children often live on the Peninsula, where the fog makes the risk feel abstract.
Heat is harder on some bodies than others. Risk climbs for:
- Adults over 65, who sweat less and feel thirst less reliably
- People with heart disease or a history of heart failure
- People with COPD or other chronic lung conditions
- People with diabetes, which can affect circulation and sweating
- Anyone with limited mobility who cannot move to a cooler room on their own
- Anyone taking medications that interfere with temperature regulation
One more factor matters here: many older inland homes have no central air conditioning. A home built to shed valley heat overnight does not do much during a five-day stretch of triple digits. If your parent is already having trouble managing the house on a hot day, that is often the same moment families start asking whether it's time to get some help at home.

Heat plus wildfire smoke is a different kind of risk
Smoke season on the Central Coast rarely stays put. Fires burning in Big Sur, Los Padres National Forest, or well outside the county can push haze into the Salinas Valley and across the Peninsula for days.
In July 2026, the American Heart Association published findings that the combination of extreme heat and wildfire smoke can nearly double the risk of a fatal heart attack, with older adults facing even greater risk. You can read the American Heart Association's warning on heat and wildfire smoke directly.
The reason is fairly simple. Heat already makes the heart work harder to cool the body. Fine smoke particles inflame the airways and lower the oxygen the blood is carrying. Stack those two demands on a heart or set of lungs that is already compromised, and the margin gets thin fast.
For a patient with a cardiac diagnosis, COPD, or an advanced illness, that means a smoke event needs to be managed clinically, not just waited out. Symptoms families should watch closely during a smoke day include new or worsening shortness of breath, chest pressure, a cough that will not settle, confusion, and swelling in the legs or feet.
The medication piece most families never hear about
This is the part that surprises people. Some of the most common medications for seriously ill patients make it harder for the body to handle heat.
Monterey County's own emergency heat guidance flags people taking certain medications as higher-risk during heat events. Broad categories that can affect temperature regulation, fluid balance, or sweating include:
- Diuretics, often called water pills
- Beta blockers and some other blood pressure medications
- Certain antidepressants and antipsychotics
- Anticholinergic medications, including some bladder and allergy drugs
- Medications that cause drowsiness or reduce awareness of thirst
Nobody should stop or change a dose on their own. But a Registered Nurse visiting the home can look at the full medication list, flag the combinations that raise heat risk, and bring concerns back to the treating physician.
That kind of review is routine work on a home visit. If you have never seen one, this walkthrough of what a skilled nurse actually does during a home visit covers the ground. Medication management is also part of why a single visit often catches problems a family has been living with for months.
Warning signs during a heat or smoke event and what they usually mean
Use this as a general reference, not a diagnosis. Any patient with a serious illness should have symptom instructions from their own physician or care team.
| What you notice | What it may point to | Typical next step |
|---|---|---|
| Hot, dry skin with no sweating, plus confusion | Possible heat stroke | Call 911 right away |
| Chest pressure, pain, or a racing heartbeat | Cardiac event | Call 911 right away |
| Sudden severe shortness of breath or bluish lips | Respiratory distress | Call 911 right away |
| Dizziness, weakness, cramping, heavy sweating | Early heat exhaustion | Move to a cooler room, give fluids, call the care team |
| Worsening cough or wheeze during a smoke day | Airway irritation | Call the care team or physician the same day |
| Not urinating much, very dark urine | Dehydration | Call the care team or physician the same day |
| More confused or sleepy than usual | Heat effect or medication effect | Call the care team the same day |
Five questions to answer before the next heat advisory
Families who work through these five questions ahead of time spend far less energy scrambling once an advisory hits.

Building a plan that fits your parent's actual house
The plan does not need to be elaborate. It needs to be specific to the home and the person in it.
Start with cooling. If there is no air conditioning, pick one room to cool rather than the whole house. Costs vary, but many households in Monterey County find portable or window units land somewhere in the range of a couple hundred dollars, and a good box fan with drawn shades makes a real difference in a valley home overnight.
Then work through the practical gaps:
- A backup plan for power, especially if the patient uses an oxygen concentrator or refrigerated medication
- Someone who can physically get the patient to the cooler room, since a hallway is a long trip for a patient with limited mobility
- Windows and doors closed during smoke, with recirculating air and a clean filter if the home has a system
- A written symptom list on the refrigerator so any family member or visitor knows what to act on
- Fluid guidance from the physician, because some heart and kidney patients have fluid limits that override general advice to drink more
One caller described the feeling plainly: they just needed someone to come out and help, because they did not know where to start. That is a normal place to be. Families managing a hospital discharge in August have plenty on their plate already, and the pieces families tend to miss during a discharge home often include seasonal safety.
The team already in the home is part of the answer
Here is what families often overlook. If a patient is receiving home health, palliative care, or hospice care at home, clinicians are already walking through that house on a regular schedule.
A Physical Therapist who visits weekly already knows whether the patient can safely get down the hall to a cooler room. A nurse already has the medication list. A Medical Social Worker already knows what community resources exist in Salinas or Hollister or King City.
Across a home care team, that means nurses, therapists, social workers, chaplains, volunteers, and other clinicians all see pieces of the picture. Seasonal safety planning is a reasonable thing to raise at the next visit instead of researching alone at 11 p.m.
One family in Monterey County described a team of nurses, physical therapists, and a Medical Social Worker coming into the home and said they were "blown away by the personalized care." That kind of coordination is exactly what makes a heat plan realistic rather than theoretical. It is also part of what makes staying home as you age workable through a hard summer.
Frequently Asked Questions About Heat, Smoke, and Home Patients
Does Medicare cover home health visits during a heat wave?
Heat by itself is not a qualifying reason for home health. But Medicare covers physician-ordered home health when a patient meets the clinical criteria, and a real change in condition during a heat or smoke event is worth reporting to the physician. Home health always starts with a physician referral, which is a step many families do not realize is required.
Should we cancel a scheduled home visit when the air quality is bad?
Talk to the care team rather than deciding on your own. Clinicians work through smoke days regularly, and a visit during a bad air stretch is often more useful than a normal one because someone is laying eyes on the patient.
My mother is on hospice at home. Does smoke really matter at that point?
Yes. Hospice care is focused on comfort, and smoke can cause coughing, breathlessness, and agitation that make a patient genuinely uncomfortable. Pain and symptom management includes respiratory symptoms, so report changes just as you would report new pain.
What about air purifiers? Are they worth it?
A unit with a HEPA filter sized for one room can meaningfully cut indoor fine particles during a smoke event. Prices vary widely by room size and brand, so check what the room actually needs. Running it in the bedroom where the patient sleeps usually gives the most benefit per dollar.
Who do I call if I am not sure whether something is an emergency?
Keep the care team's clinical line where you can see it, and use 911 without hesitation for chest pain, severe shortness of breath, or new confusion. Guessing wrong toward caution is the right error to make.
Want help thinking through a heat and smoke plan?
Summers in Monterey County are not getting gentler, and families in Salinas, King City, and Hollister feel that before anyone on the coast does. If you have questions about care at home during a heat or smoke event, a care coordinator at Central Coast VNA & Hospice can talk through what applies to your loved one's situation. Call 831-372-6668 or visit ccvna.com when the timing is right for you.

California's Hospice Fraud Crisis: What Families Need to Know
In April 2026, federal agents suspended 447 hospices and 23 home health agencies in the greater Los Angeles area, alleging roughly $600 million in Medicare fraud. That number is not a typo. California's hospice fraud problem has grown into one of the largest healthcare crime waves in the country.
The fraud is not limited to Southern California, and it is not abstract. The California Hospice and Palliative Care Association has documented cases where scammers "deceptively and illegally enroll seniors in hospice and skilled home health programs they never consented to." Families across the state, including those in Monterey County, need to understand what is happening before they accept a referral or sign any paperwork.
This article focuses on two things: what the fraud actually looks like in practice, and how families can tell the difference between a trustworthy provider and one they should walk away from.
What California's Hospice Fraud Actually Looks Like
Hospice fraud does not always look like obvious crime. It often looks like a helpful person showing up at the right moment, offering relief to a family that is already exhausted and overwhelmed.
The scheme tends to follow a pattern. A recruiter, sometimes posing as a hospital worker or social services coordinator, approaches a senior or their family and steers them toward a specific hospice agency. The family signs documents they may not fully understand. The agency then bills Medicare for services it either never delivers or delivers poorly, while the patient loses access to treatments they could still benefit from.
The California Governor's office confirmed expanded DHCS oversight of hospice services taking effect in July 2026, and emergency hospice regulations took effect on June 22, 2026, giving the California Department of Public Health broader authority to deny licensure, investigate complaints, and revoke licenses from illegitimate operators. This is a meaningful shift. But regulations alone do not replace a family's own judgment.
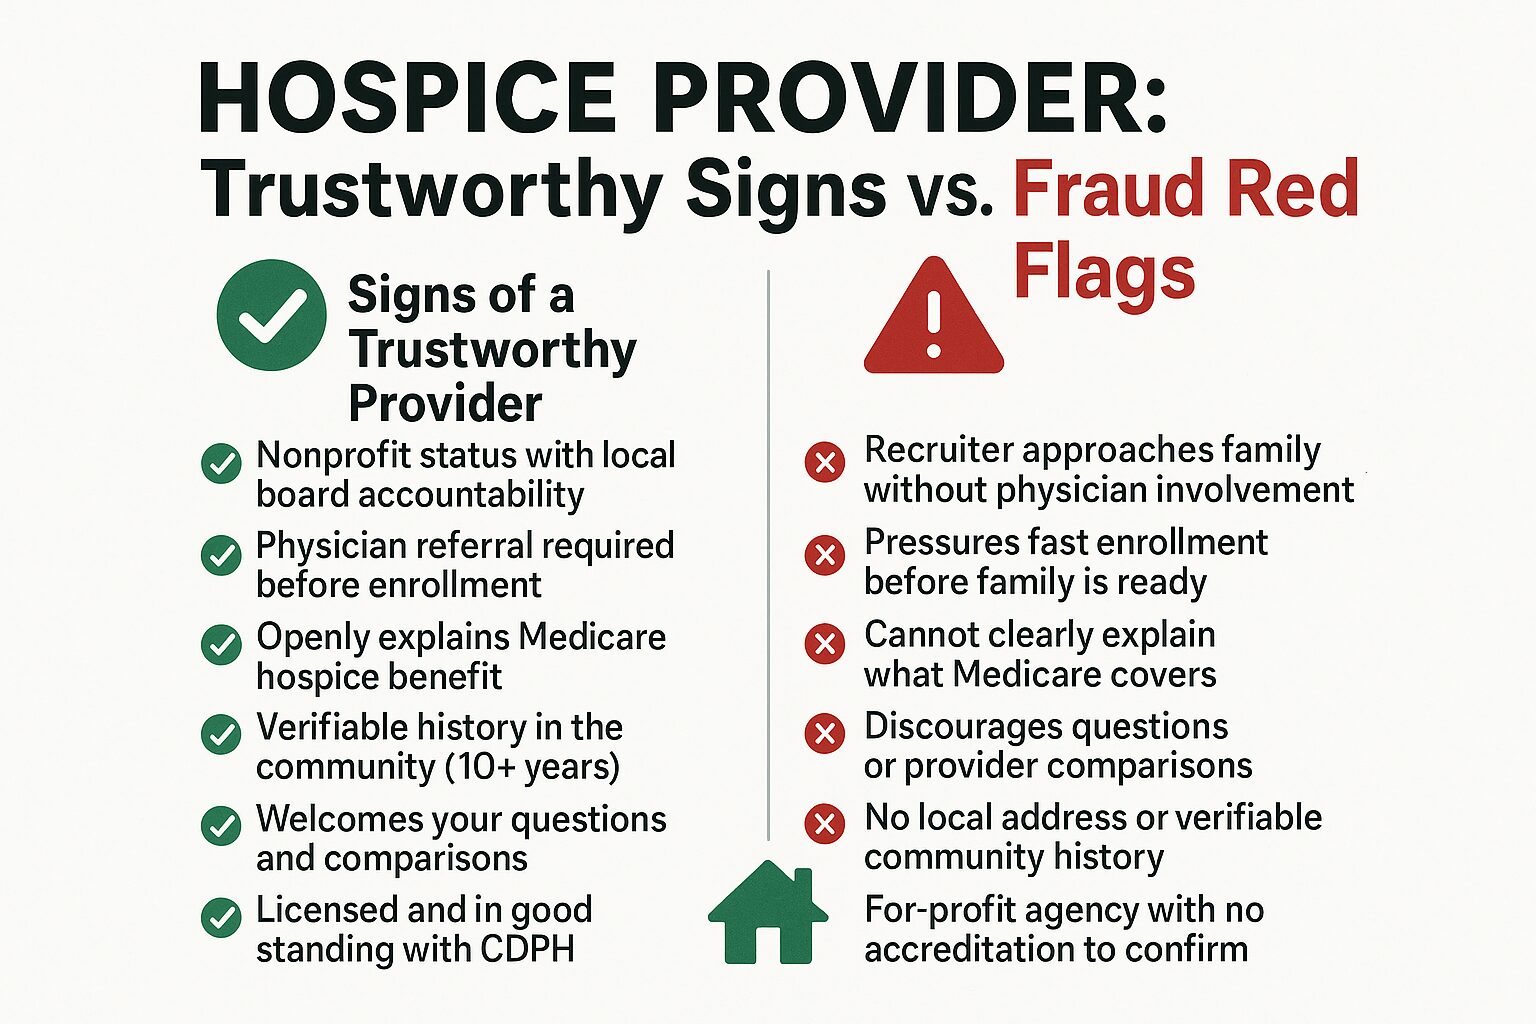
The warning signs families should watch for include:
- Pressure to enroll before a physician has recommended it, a legitimate hospice never pushes enrollment
- Recruiters approaching you in non-medical settings, like at a senior center, a pharmacy, or through an unsolicited call
- An agency that cannot clearly explain what the Medicare hospice benefit covers or what your loved one would be giving up
- Discouraging you from asking questions or comparing providers
- No verifiable history in your community, no local address, no staff you can speak with directly, no track record you can confirm
If any of these apply to a provider you are considering, stop and ask more questions before moving forward.

Why Referrals Alone Are Not Enough
Many families assume that if a hospital or physician refers them to a hospice provider, that provider must be reputable. This is understandable, but it is not always true.
Hospital discharge planners work under real time pressure. They may default to whichever agency responds fastest or is most familiar to their team, not necessarily the one with the strongest record of care. A referral is a starting point, not a guarantee.
Families have every right to ask:
- "Who else could we consider for hospice care in this area?"
- "How long has this agency operated in Monterey County or the surrounding region?"
- "Is this provider accredited and in good standing with the California Department of Public Health?"
- "Is this a nonprofit or a for-profit agency?"
Asking those questions is not rude. It is exactly what a thoughtful family should do. A trustworthy provider will welcome them. One with something to hide will not.
For families navigating this for the first time, it also helps to understand what hospice actually involves before any agency visit or paperwork conversation. Articles like how to know when it may be time to consider hospice care and what families often miss when planning a hospital discharge to home can help you go into those conversations with the right questions already in mind.
Trustworthy Hospice Provider vs. Fraud Red Flags
Use this side-by-side comparison to quickly evaluate any hospice provider you are considering.
What Longevity and Nonprofit Status Actually Signal
One of the most reliable ways to evaluate a hospice provider is to ask how long they have been operating in your specific community, and whether they are a nonprofit.
Fraud operations are built to bill Medicare quickly and then disappear or rebrand before regulators catch up. They cannot fabricate decades of community presence. A nonprofit organization accountable to a local board of directors has a fundamentally different structure than a billing operation set up to exploit the Medicare hospice benefit.
This is not to say that all for-profit hospice agencies are fraudulent, or that all nonprofits are above criticism. But when a provider has been delivering care in the same communities since before most of today's families were born, that history is verifiable. Patients and families from Salinas, Pacific Grove, King City, and Hollister can speak to the care they received. Neighbors can vouch or not vouch. That kind of local accountability does not exist when a provider showed up recently with no track record you can trace.
Families evaluating their options should also consider whether a provider accepts Medicare and Medi-Cal on a transparent basis. Legitimate providers are straightforward about coverage. If an agency is vague about billing or steers you away from using Medicare, that is a reason to pause.
For a broader look at how to evaluate a provider's credibility, how to tell if a hospice provider is actually trustworthy covers the specific questions worth asking before you commit.
Questions to Ask Any Hospice Provider Before Enrolling
Before agreeing to hospice services for a loved one, work through this checklist with any provider you are considering.
| Question to Ask | What a Good Answer Looks Like | Why It Matters |
|---|---|---|
| How long has your agency operated in this county? | Specific founding year, verifiable local history | Fraud operations cannot fake a long local track record |
| Is this agency nonprofit or for-profit? | Clear, direct answer with no deflection | Nonprofit status signals community accountability over profit motive |
| Did my physician recommend hospice and refer us to you specifically? | Enrollment should follow a physician recommendation | Unsolicited recruitment is a primary fraud tactic |
| What exactly does the Medicare hospice benefit cover? | Plain explanation of covered services and what changes at enrollment | Legitimate providers explain this clearly without hesitation |
| Are you licensed and in good standing with the California Department of Public Health? | Confirmed licensure, ability to provide accreditation details | New regulations give CDPH authority to revoke fraudulent operators |
| Can I speak with a care coordinator before we decide anything? | Yes, with no pressure to sign first | Trustworthy agencies welcome questions before commitment |
What the New California Regulations Mean for Families
The emergency hospice regulations that took effect June 22, 2026 represent a real shift in how California oversees hospice licensure. The California Department of Public Health now has broader authority to deny new licenses, investigate complaints more aggressively, and revoke the licenses of providers found to be operating fraudulently.
This matters for families because it means the accountability gap that allowed hundreds of fraudulent agencies to operate in California is beginning to close. The expanded DHCS oversight taking effect July 2026 adds another layer of scrutiny at the state level.
But regulatory change moves slowly compared to how quickly a family in crisis needs to make a decision. If your parent is being discharged from Natividad Medical Center or Community Hospital of the Monterey Peninsula and a hospice referral is on the table, you may have hours, not weeks, to evaluate your options. Knowing the warning signs in advance is the practical advantage that regulations alone cannot give you.
Families who want to understand more about what hospice actually involves, separate from the fraud question, will find it useful to read hospice care is not what most families think it is before they are in a time-pressured situation.
Frequently Asked Questions About Hospice Fraud in California
Can I switch hospice providers if I realize I enrolled with the wrong one?
Yes. Under the Medicare hospice benefit, a patient has the right to change hospice providers. You can request a transfer to a different agency without losing your hospice eligibility. If you believe you were enrolled without proper consent or under false pretenses, you can also report the provider to the California Department of Public Health and to Medicare directly.
Does the hospice fraud crisis affect providers in Monterey County, or just Southern California?
The large-scale suspensions in April 2026 centered on the Los Angeles area, but the patterns that enable fraud, including loose oversight and aggressive recruiting, are not geographically limited. Families throughout California, including the Central Coast, should apply the same due diligence regardless of location.
What does a patient give up when they enroll in hospice?
Under the Medicare hospice benefit, a patient agrees to shift focus from curative treatment to comfort-focused care. This means Medicare generally stops covering treatments aimed at curing the underlying illness. This is a significant decision that should happen only when a physician has determined that curative treatment is no longer the goal, and only after a full conversation with the patient and family. Any provider that enrolls a patient without that conversation is not operating ethically. For more on this, comfort care vs. hospice: why the difference matters explains the distinction clearly.
How do I verify a hospice provider's license in California?
The California Department of Public Health maintains a public database of licensed healthcare providers. You can search by provider name or license number to confirm current status. If a provider cannot give you a license number or discourages you from checking, that is a significant warning sign.
Is a physician referral required to start hospice?
Yes. Legitimate hospice enrollment requires a physician to certify that the patient has a terminal diagnosis with a life expectancy of six months or less if the illness follows its expected course. No reputable hospice agency will enroll a patient without that physician certification in place. If someone is pushing enrollment before that step has happened, stop and ask why.
Want to Ask Questions Without Any Pressure?
Central Coast VNA & Hospice has been serving families in Monterey County, San Benito County, and surrounding Central Coast communities since 1951, and a care coordinator is available to answer your questions at whatever pace you need. You can call the team at 831-372-6668 or visit ccvna.com to learn more about hospice and palliative care services, how the enrollment process actually works, and what families in this region typically want to know before they decide.

The First Holiday Season After a Loss: What Grief Can Look Like
The weeks right after someone dies are often filled with motion. There are arrangements to make, people to call, paperwork to complete. Families move through that period with a kind of purposeful momentum that can feel, from the outside, like coping.
Then the holidays arrive. And the absence, which may have felt manageable in the busyness of early grief, suddenly fills the entire room.
For families across Monterey County, from the Peninsula to Salinas to Hollister, this pattern shows up every year without fail. It is not a sign that something has gone wrong in the grieving process. It is one of the most common and well-documented features of grief, and understanding it before the season hits can make a real difference in how families find their footing.
Why the First Holiday Hits Harder Than Families Expect
Grief researchers have long noted that the initial weeks after a death carry a kind of protective busyness. The practical demands of loss, the calls, the services, the thank-you notes, give the grieving person something to do with the enormity of what has happened.
When that activity ends and the first Thanksgiving, Christmas, or even a birthday rolls around, the absence can feel sudden and total. The holiday table, the family rituals, the food that was always made the same way, all of it becomes a sensory reminder of who is no longer there.
This is not pathological grief. It is a normal part of the grief timeline, and it is worth knowing it is coming before it arrives. According to research from the American Psychological Association, anticipating difficult grief moments and having support in place ahead of time is one of the most practical steps a grieving person can take.
For families who lost someone in the spring or summer, the holiday season may arrive when they feel they should be "past the hardest part." That expectation can make the holiday wave feel even more disorienting when it comes.

Spousal Loss and the Holiday Table
Not all grief moves the same way, and the holiday grief that surviving spouses experience often has a specific quality that is different from what adult children feel when mourning a parent.
Decades of shared ritual create a kind of sensory map. The same table. The same seat. The food that one person always made and the other always praised. When those rituals arrive without the person who made them meaningful, the loss can feel both immediate and total in a way that is hard to describe to someone who hasn't lived it.
One Monterey woman submitted a message to a local bereavement program the day after her husband of 56 years died. Her message was direct and raw: she needed a local grief group, immediately. That kind of reaching out, in the earliest hours of loss, reflects something grief support professionals see often. The need for connection is immediate, even when the emotional capacity to reach out is barely there.
For surviving spouses specifically, grief support programs that address spousal loss tend to be more useful than general bereavement groups. The shared experience in the room matters. When the people around you have also lost a partner of many years, the conversations start at a different depth.
If you are an adult child helping a surviving parent plan for the holiday season, understanding what grief support after hospice actually looks like can help you find the right kind of help, not just the closest available option.
The Grief Timeline Around the Holidays
This overview shows how grief tends to shift in the weeks surrounding the first holiday season, and when families most often reach out for support.

Finding Support Before the Season Arrives, Not After
Grief counselors and Bereavement Specialists consistently note the same pattern: the sharpest increase in inquiries from grieving families arrives in the weeks between Thanksgiving and New Year's. Many of those callers say the same thing, they thought they were managing fine.
The problem is that finding a local grief group or counselor in the middle of an acute grief moment is much harder than finding one in a calmer week. The emotional bandwidth required to research options, make calls, and get enrolled in a program is exactly what grief depletes.
For families in the Monterey Peninsula, Salinas, and Hollister areas, the practical advice is straightforward: identify your support resource before the holiday season, not during it. Get on the list. Attend once. Know where to go.
Bereavement support in Monterey County is not limited to families who used hospice services. Anyone who has experienced a significant loss, whether a loved one died at home, in a hospital, or in a care facility, can access grief counseling and group support. That access point is not always obvious to families who navigated a hospital death rather than a hospice program, and it is worth knowing the door is open.
You can read more about what is specifically available locally in this guide to finding grief support in Monterey County after a loss.
For families who are also managing a loved one's ongoing health needs while grieving, the weight can compound quickly. Knowing when caring for an aging parent becomes more than you can do alone is a useful starting point if that is part of your situation.
Types of Grief Support and Who They Tend to Help
Different kinds of support serve different needs. This is a general overview, the right fit depends on the individual and what feels most useful.
| Type of Support | What It Involves | Best Fit For |
|---|---|---|
| Individual grief counseling | One-on-one sessions with a Bereavement Specialist or licensed counselor | People who prefer privacy or have complex grief histories |
| General bereavement group | Group sessions open to anyone who has experienced a loss | People who find connection with others helpful and have flexible schedules |
| Spousal loss group | Group sessions specifically for people who have lost a spouse or partner | Surviving spouses navigating the specific pattern of partner grief |
| Community bereavement programs | Support offered through local nonprofits, open to the broader community regardless of how care was received | Anyone who lost a loved one in a hospital, at home, or in a care facility |
What Grief Can Actually Look Like in the Weeks Around the Holidays
Grief does not always look the way people expect. Some of what families experience around the first holiday season can feel confusing, because it may not match what they think grief is supposed to be.
Common patterns include:
- Feeling fine for days, then being hit hard by a specific song, smell, or meal
- Dreading the holiday weeks in advance, then finding them more manageable than expected, followed by a harder week afterward
- Feeling guilty for laughing or enjoying any part of the holiday
- Anger or irritability that doesn't seem tied to anything specific
- Physical symptoms, fatigue, poor sleep, changes in appetite, that arrive or worsen around the holiday period
- Difficulty being around the same family gathering without the person who is gone
None of these responses are wrong. And none of them mean that grief is "not progressing." Grief doesn't follow a schedule, and the holiday season has a way of making that very clear.
If grief starts to feel stuck, not just painful, but genuinely immovable over many months, that is worth a conversation with a counselor. There is a difference between grief that is hard and grief that has become complicated in ways that benefit from professional support. Understanding complicated grief can help families recognize when that line has been crossed.
Frequently Asked Questions About Grief Support During the Holidays
Do I have to have used hospice services to access bereavement support in Monterey County?
No. Bereavement support through community-based programs is open to anyone who has experienced a significant loss, regardless of how care was provided. If your loved one died in a hospital or care facility rather than through a hospice program, you can still reach out for grief counseling or group support.
When should I look for a grief support group, before or after the holidays?
Before, if at all possible. The weeks between Thanksgiving and New Year's are when Bereavement Specialists see the sharpest increase in people reaching out. Having a resource already identified, even just knowing where to call, means it is there when you need it most, rather than having to search in the middle of a difficult moment.
Is it normal to feel like the holidays are harder than the days right after the death?
Yes, and it is more common than most families realize. The initial weeks after a loss often carry a protective momentum, things to do, people to contact. When that activity winds down and a holiday arrives, the absence becomes much more visible. This is a well-documented feature of grief, not a sign that something has gone wrong.
My surviving parent lost their spouse of many decades. Are there specific groups for that kind of loss?
Yes. Spousal loss groups focus specifically on the grief of losing a long-term partner, which has a different quality than grieving a parent or sibling. The shared experience in the room matters, conversations can start at a level of specificity that a general group may not reach. Ask when you call about bereavement resources whether a spousal loss group is available in your area.
What if I'm not sure whether what I'm feeling is grief or something that needs clinical attention?
A conversation with a Bereavement Specialist is a good first step. They can help you understand whether what you are experiencing is part of a normal grief process or whether it might benefit from a more structured clinical response. You do not need to have a diagnosis or a crisis to make that call, it is what the support is there for.
Finding Support in Monterey County Before the Season Hits
Central Coast VNA & Hospice has been supporting grieving families across Monterey County, Salinas, Hollister, and surrounding communities since 1951. In 2025 alone, the bereavement program extended support to more than 2,200 individuals, many of them people who had not used hospice services but needed a place to turn. If you or someone you love is approaching the first holiday season after a loss, a Bereavement Specialist can help you understand what is available and whether a group or individual counseling might be the right fit. You can reach the care team at 831-372-6668 or visit ccvna.com to learn more.

What Grief Support After Hospice Actually Looks Like
Most families assume that when a loved one dies under hospice care, their relationship with the care team ends that same day. A phone call, maybe a card in the mail, and then silence. That assumption is understandable, but it's also wrong, and for families across Monterey County, the difference matters.
Grief doesn't follow a tidy timeline. The weeks after a death can feel surreal, then exhausting, then suddenly empty in ways nobody warned you about. Knowing what bereavement support after hospice loss actually looks like, what happens, when it happens, and what you can ask for, gives families a clearer picture of what's available before they need it most.
This article focuses specifically on the transition from hospice to bereavement: the first days, the first months, and what structured grief support looks like in practice.
The First Outreach Isn't a One-Time Check-In
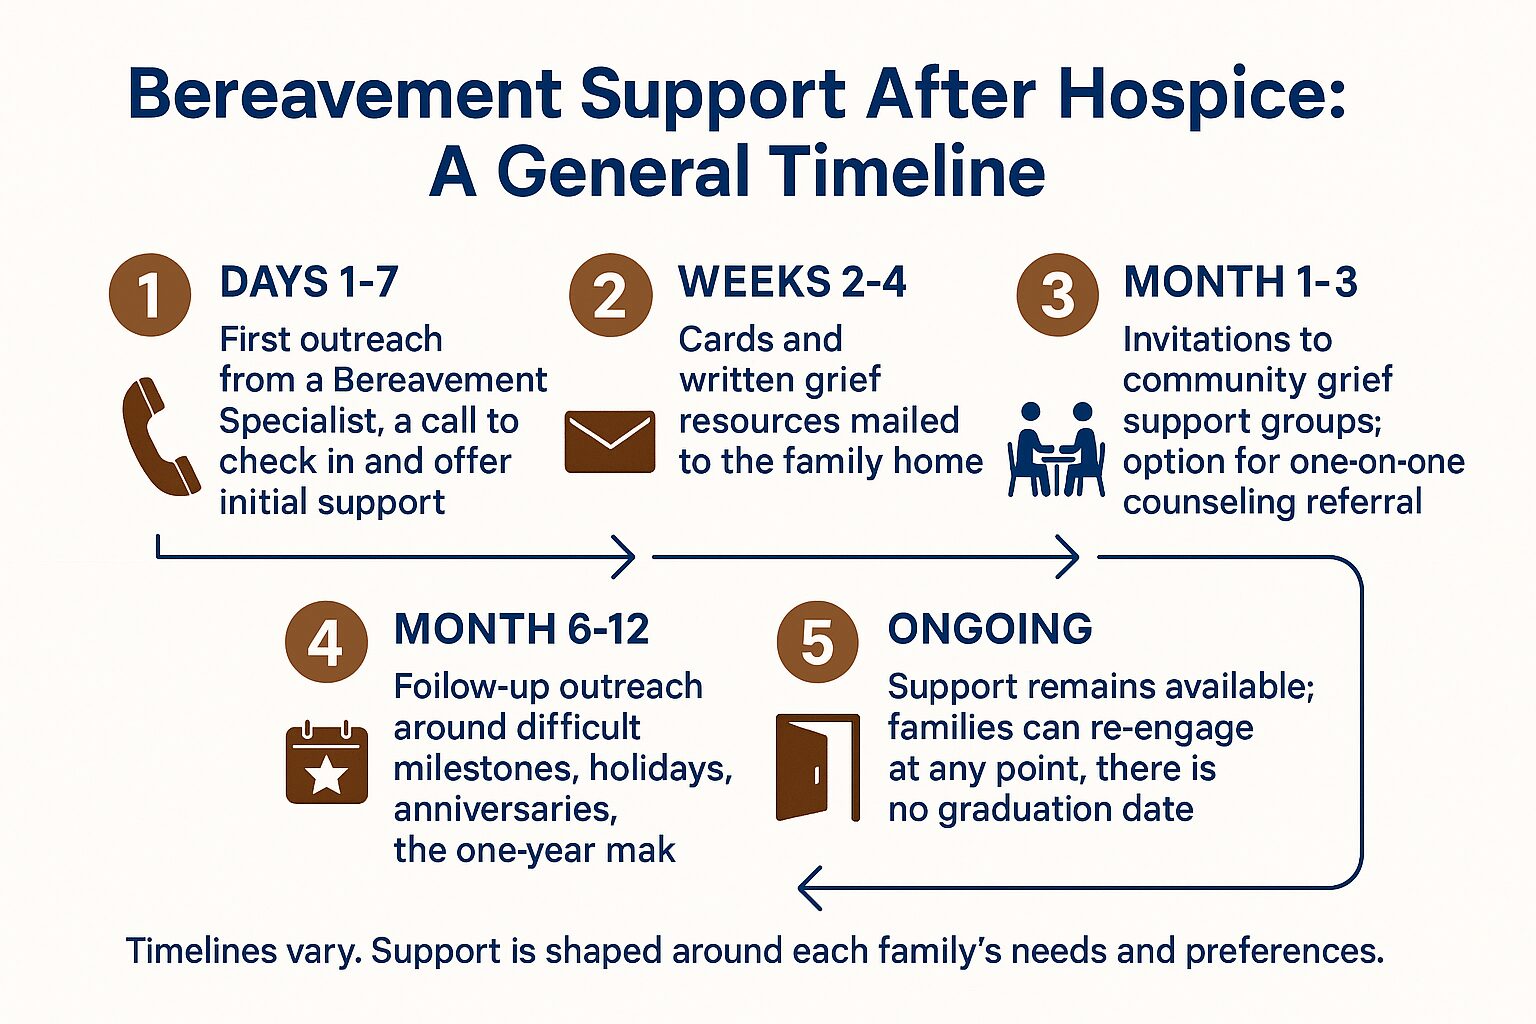
After a patient passes, a Bereavement Specialist reaches out to the family. That first contact is not a formality and not a single call. It's the beginning of a structured support program that unfolds over months.
Depending on what the family needs, that support can include:
- Phone calls at key intervals in the weeks following the death
- Cards and written grief resources mailed to the home
- Invitations to join a grief support group in the community
- Referrals for one-on-one counseling when a family member needs more than a group setting can offer
Some families engage actively with every touchpoint. Others prefer a lighter presence, just knowing support exists if they reach for it. Both approaches are respected. There's no pressure to participate in any particular way, and no single path that families are expected to follow.
In 2025, more than 2,200 individuals received bereavement support through this kind of program across Monterey County and surrounding communities. That number reflects real depth, not a small afterthought program, but one built for the full range of how people grieve.
For families wondering whether grief counseling and group support are available to them specifically, the Finding Grief Support in Monterey County After a Loss resource offers more detail on local options.

The Loss Nobody Warns You About: When the Role Disappears
There's a specific grief experience that often catches people off guard, and it belongs to the person who was the primary day-to-day presence during a loved one's illness.
For months or years, that person, often an adult child or a spouse, organized their life around someone else's needs. Medication schedules. Appointments. Calls to the care team. The constant, focused attention that serious illness demands. Then, almost overnight, all of it stops.
What's left isn't just grief for the person who died. It's also the loss of purpose and structure. The quiet that was supposed to feel like relief instead feels disorienting. And many people are not prepared for it.
This is a well-documented pattern. Research from the National Institute on Aging confirms that grief takes many forms, and that those who served as primary supporters during illness often face a layered loss that goes beyond the loss of the relationship itself.
A Bereavement Specialist or grief group facilitator who understands this particular experience brings something different from general mental health support. They've sat with families at this exact point of transition many times before. That familiarity shapes how they listen and what they suggest.
If you were the person doing the daily work of caring for someone, it's worth naming that experience when you reach out for support, because it's a real and distinct part of what you're carrying.
What Bereavement Support Looks Like Over Time
Grief support after hospice loss doesn't arrive all at once. This timeline shows what families can typically expect in the weeks and months that follow.
Grief Peaks at Unexpected Moments, and Support Should Too
One of the most honest things that can be said about grief is that it does not resolve on a fixed schedule. The people around a grieving person often move on within weeks. But grief frequently intensifies around specific moments: the first holidays, a birthday, the one-year anniversary of a death, a random Tuesday when a song plays on the radio.
This is exactly why bereavement support programs are designed to follow up at intervals, not just in the immediate aftermath of a death. A check-in at six months or twelve months isn't a formality, it's timed to a period when many people feel most alone in their grief.
One person who volunteered as a hospice vigiling volunteer, sitting bedside to provide comfort during a patient's final hours, wrote publicly about being consistently impressed by the quality of the clinical staff and the genuine care they showed families across difficult moments. That kind of team culture doesn't end at the patient's death. It extends into how Bereavement Specialists, grief group facilitators, and Volunteers continue to show up for families afterward.
If you're wondering whether complicated grief, the kind that feels stuck rather than slowly moving, is something you're experiencing, the article When Mourning Feels Stuck: Understanding Complicated Grief addresses that specific experience in more depth. And if grief simply doesn't seem to be following any predictable pattern at all, Grief Doesn't Follow a Schedule, What Support Actually Helps is worth reading.
Two Paths Through Bereavement Support
Families engage with grief support in very different ways. Neither path is wrong, the right level of involvement is whatever actually helps.
| If You Want Active Support | If You Prefer a Lighter Presence |
|---|---|
| Regular calls from a Bereavement Specialist | Knowing contact information is available when needed |
| Grief support group attendance in the community | Receiving mailed resources without committing to calls |
| Referral to one-on-one grief counseling | Reconnecting with the program at a later milestone |
| Follow-up outreach at key anniversaries | Opting back in if grief intensifies unexpectedly |
| Ongoing coordination with the broader care team | A single point of contact who can respond if you reach out |
Who Can Access Bereavement Support
One question families sometimes ask is whether bereavement support is only available to people whose loved one was actively enrolled in hospice. The answer is broader than most people expect.
Grief counseling and bereavement services are available to anyone navigating the loss of a loved one, not only families who went through a formal hospice program. If someone in Salinas, King City, Hollister, or anywhere else in Monterey County is carrying grief and doesn't know where to turn, that support is not locked behind prior enrollment.
Bereavement is also not the same conversation as hospice eligibility or home health. If you're still in an earlier stage, trying to understand whether hospice is even the right direction, the article How Do You Know When It's Time to Consider Hospice Care? is a better place to start. And if a loved one is still living but facing serious illness, What Palliative Care Actually Means, and When It Can Start explains how earlier support works alongside treatment.
Frequently Asked Questions About Bereavement Support After Hospice
Does bereavement support really continue after my loved one dies, or is it just a one-time call?
It continues. A structured bereavement program typically includes multiple points of outreach over months, not a single call. This can include phone check-ins, mailed resources, grief group invitations, and referrals for individual counseling depending on what a family needs.
What if I wasn't the primary person in the house, but I'm still grieving? Can I access support too?
Yes. Grief doesn't only belong to the person who was most physically present. A sibling who lived across the country, a close friend, an adult child who visited on weekends, all of these people can experience significant loss. Bereavement support is not limited to a single designated family member.
I feel fine right now, but I've heard grief sometimes hits hard later. What if I need support months from now?
That's a very common pattern. Many people find that grief intensifies at the six-month or one-year mark, or around the first holiday season after a death, often because the people around them have moved on and the loss feels more isolating. A good bereavement program anticipates this and reaches out at those intervals. And if support isn't already in place, reaching out later is always an option.
I was the one managing all the care for months. Now I feel lost without that structure. Is that normal?
It's extremely common and worth naming directly. When someone's daily life is organized around another person's medical needs, appointments, medications, calls to nurses and therapists, the loss of that structure after a death is a real secondary grief. It's not weakness or confusion; it's a recognized part of the grief experience for primary family supporters. Mentioning this specifically when you reach out for support will help a Bereavement Specialist understand what you're going through.
Do I need to have used hospice to access grief support?
No. Bereavement and grief counseling are available to anyone experiencing loss, not only families who went through a formal hospice program.
What if I live in Salinas or King City, not right on the Monterey Peninsula? Is support available there too?
Yes. Monterey County as a whole is part of the service area, which includes the Peninsula, Salinas, King City, and surrounding communities. Geography should not be a barrier to reaching out.
Ready to Learn What Support Is Available to Your Family?
Central Coast VNA & Hospice has been walking alongside families in Monterey County through some of the hardest moments of their lives since 1951. If you or someone you love is in the months following a loss and wondering what support looks like, a conversation with a care coordinator is a good first step, no commitment required, no pressure. You can reach the team at 831-372-6668 or visit ccvna.com to learn more.

When a Parent's Medications Become Too Much to Track Alone
A Monterey County family reached out in early 2026 with a situation that many families here are quietly living through. Their 83-year-old mother, a cancer survivor, and their 86-year-old father, recently diagnosed with dementia, were living independently, but managing more than five medications between them had become more than Mom could handle alone. The question they asked was simple: can a Registered Nurse come to the house and help sort this out?
The answer is yes. But most families don't know that until they're already in crisis.
This article explains what medication management at home actually looks like, why it matters more when dementia is part of the picture, and how skilled nursing visits work, including what Medicare covers and how to get one started in Monterey County.
What Polypharmacy Means and Why It Raises the Stakes
Polypharmacy is the term clinicians use when a patient takes five or more medications regularly at the same time. It's common in older adults managing multiple chronic conditions, heart disease, diabetes, cancer recovery, and now, increasingly, dementia, and the risks grow with every added prescription.
The National Institute on Aging notes that drug interactions and dosing errors are among the most preventable causes of hospitalization in older adults. When you add dementia to the picture, those risks compound.
A parent with dementia may:
- Take a dose twice because they don't remember the first one
- Skip doses entirely without realizing it
- Be unable to describe side effects they're experiencing
- Struggle to manage a pill organizer independently, even a simple one
For an adult child managing this from across the Monterey Peninsula, or from Salinas, or King City, the coordination challenge is real. You can't be there for every dose. And the stakes of a mistake are high.

What a Skilled Nursing Medication Visit at Home Actually Looks Like
This is not a wellness check or a friendly drop-in. A skilled nursing medication management visit is licensed clinical work, performed by a Registered Nurse in the patient's home.
Here's what happens during that visit:
- The RN collects and reviews every medication the patient is taking, prescriptions, over-the-counter drugs, and supplements
- Each drug is checked for correct dose and timing against the physician's orders
- The nurse screens for drug interactions that may not have been flagged when prescriptions came from different specialists
- If adjustments are needed, the RN coordinates directly with the prescribing physician
- The patient and family receive clear education on what each medication does and what warning signs to watch for
- A daily schedule is established that works for the household, not just for a chart
For a family where one parent has dementia and the other is managing recovery from cancer treatment, this kind of structured visit changes the daily reality. It moves the household from guesswork to a clear, clinically reviewed plan.
You can read more about what a nurse actually does on one of these visits in this overview of what a skilled nurse actually does on a home visit.
How a Medication Management Home Visit Works
This step-by-step breakdown shows what happens from the first phone call to an established medication plan in the home.
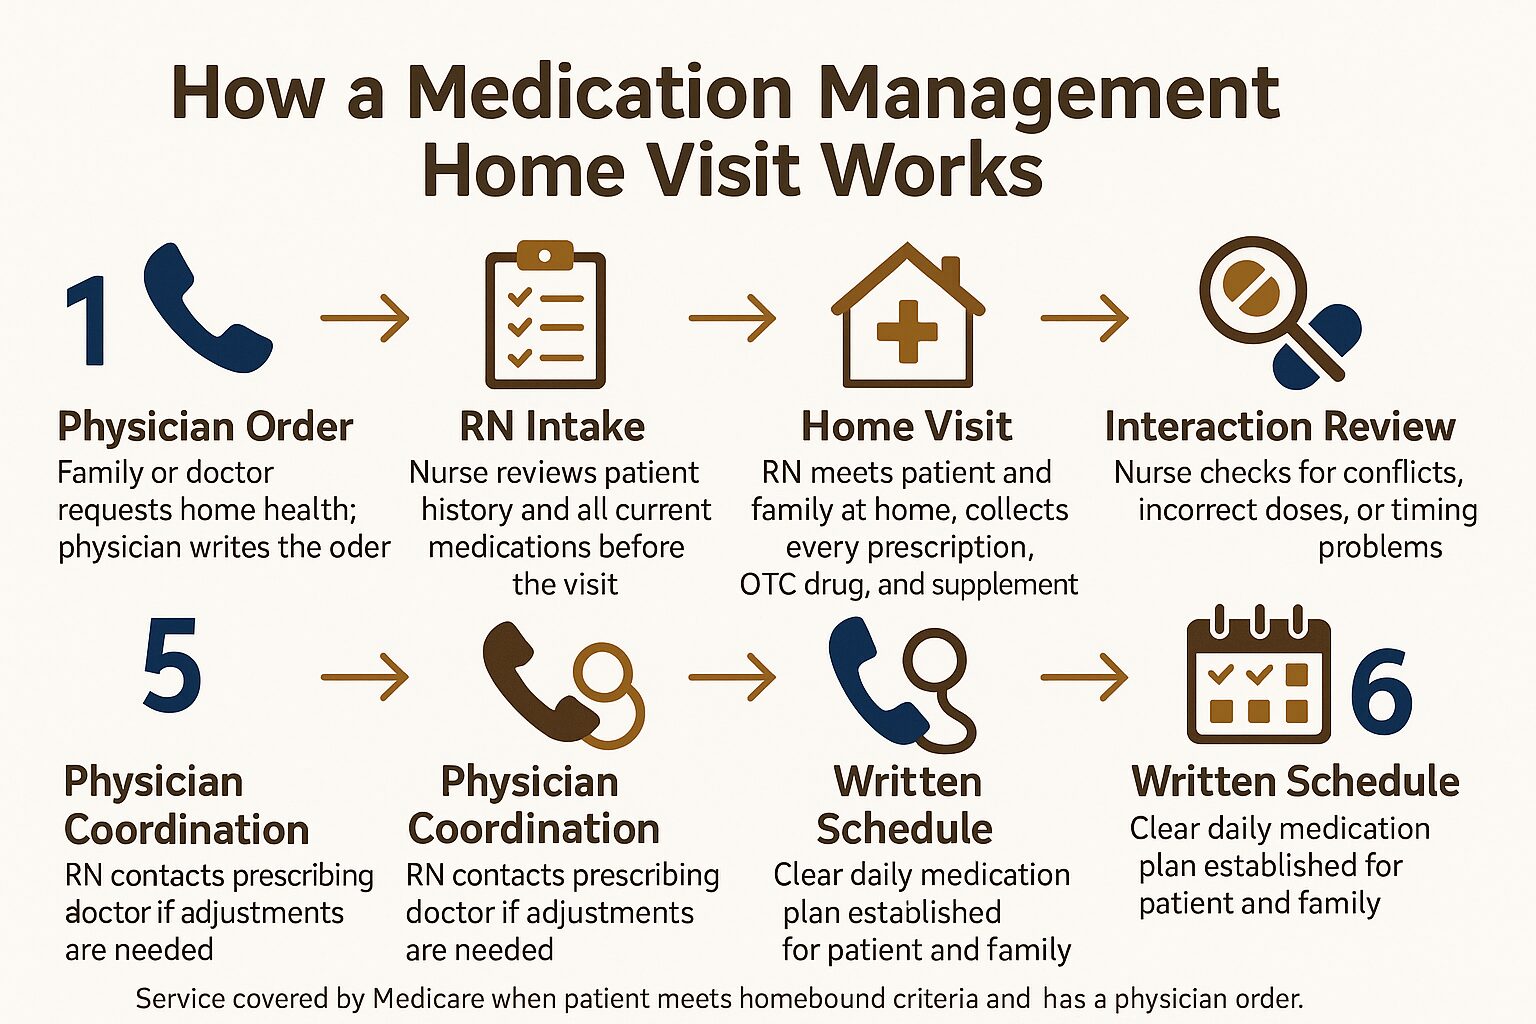
Does Medicare Cover This, and How Do You Get It Started?
Medicare Part A and Part B both cover skilled nursing home visits when the patient meets homebound criteria and has a physician order for the service. Homebound does not mean bedridden, it means that leaving home requires a considerable effort due to illness, injury, or cognitive decline.
For a parent with dementia and multiple complex medications, that threshold is often met. The conversation starts with the patient's physician.
Many families are surprised to learn that a physician referral is required before a skilled nurse can come to the house. It's not a barrier, it's how the clinical and insurance systems connect. If you're not sure how that process works, this explanation of why a physician referral is required for home health walks through it clearly.
VNA accepts Medicare, Medi-Cal, and Veterans benefits for qualifying home health services. For families navigating both parents' needs simultaneously, knowing that coverage exists for this kind of skilled visit is often the piece of information that changes everything.
Skilled Nursing at Home vs. Managing Medications Without Help
This comparison shows what changes when a Registered Nurse steps in to manage a complex medication situation at home.
| Area of Risk | Without Skilled Nursing Support | With RN Medication Management |
|---|---|---|
| Drug interactions | Unknown unless a pharmacist flags it at pickup | Clinically screened during the visit; physician contacted if needed |
| Missed or doubled doses | Common, especially with dementia; often undetected | Daily schedule established and reviewed; family educated on monitoring |
| Side effect recognition | Patient may not self-report; family may not know warning signs | RN educates family on what to watch for and when to call the doctor |
| Coordination between specialists | Falls to the family to relay information between offices | RN communicates directly with prescribing physicians on the patient's behalf |
| Medicare coverage | Not applicable | Covered when patient meets homebound criteria and has a physician order |
The Emotional Weight Nobody Talks About
Managing two aging parents with serious health histories, one with dementia, one recovering from cancer, is not a logistical problem. It's an emotional one that happens to have logistical symptoms.
Families in this situation often describe the same feelings: they're afraid of making a mistake, they don't know where to start, and they feel like they're doing it alone. Those feelings are completely understandable. The medication situation is genuinely complex. It's not something a pill organizer and a spreadsheet can solve when cognitive decline is in the picture.
Calling a nurse to the home is not an admission of failure. It's the right tool for a genuinely difficult clinical situation. The skilled nursing care at home article addresses a lot of the assumptions families carry into this, including the worry that asking for help means giving something up.
For families managing a parent with dementia specifically, it can also help to understand the full picture of what support looks like as the disease progresses. The article on hospice criteria for dementia addresses questions families often don't feel ready to ask out loud, but frequently need answered.
Why Local, Nonprofit Care Makes a Difference Here
In 2025, VNA's nurses and clinicians made more than 73,000 home visits across Monterey County, serving over 3,800 patients across the full spectrum of care. Medication management is one of the core services that Registered Nurses and Licensed Vocational Nurses deliver on those visits every week, in Salinas, in Pacific Grove, in King City, and throughout the Salinas Valley.
For a family trying to coordinate care for two aging parents from across town, that local presence matters. A nonprofit with 75 years of community history in Monterey County knows the area's physicians, the local hospital discharge teams, and the real geography of getting to a patient's home.
That's a meaningfully different experience from navigating a large regional agency that doesn't know the Central Coast. And for families wondering how to keep a parent at home safely as their needs grow, understanding how long aging in place can realistically work is a worthwhile starting point.
Frequently Asked Questions About Medication Management at Home
Can a nurse really come to my parent's house just to review medications?
Yes. A Registered Nurse can come to the home specifically to review all medications, check for interactions, confirm correct dosing, and set up a daily schedule. This is a skilled nursing service covered by Medicare when the patient meets homebound criteria and has a physician order. It is not a general wellness visit, it is clinical work.
My father has dementia. Does that change what kind of help is available?
It changes how care is delivered, not whether it's available. For a patient with dementia, the RN will work closely with family members to establish a system that accounts for the patient's cognitive limitations. The nurse also educates the family on warning signs, because the patient may not reliably report how they're feeling. The physician is kept in the loop throughout.
We have two parents with different health histories. Can a nurse help with both?
Home health services are ordered per patient, so each parent would have their own plan and physician order. But a skilled nursing team can coordinate visits and care planning for both. That's a conversation worth having with a care coordinator when you first reach out.
Does Medicare cover medication management visits at home?
Medicare Part A and Part B both cover skilled nursing home visits when the patient is homebound and has a physician order. Homebound doesn't mean bedridden, it means leaving home takes considerable effort. Many patients with dementia or serious chronic illness qualify. Medi-Cal and Veterans benefits may also apply depending on the patient's coverage.
How do I get this started for my parent in Monterey County?
The first step is a physician order. Talk to your parent's primary care physician and ask for a home health referral specifically for skilled nursing and medication management. If you're not sure how to have that conversation, a VNA care coordinator can walk you through the process. You can reach the care team at 831-372-6668 or visit ccvna.com.
Ready to Get a Clearer Picture of Your Parent's Medication Situation?
If you're managing a parent's medications in Monterey County and things have gotten too complex to handle alone, Central Coast VNA & Hospice has care coordinators who can help you figure out the right next step. You can reach the team at 831-372-6668 or visit ccvna.com to learn more about home health services and what Medicare covers.

Why a Physician Referral Is Required for Home Health, and How It Works
One of the most common things families say when they first call about home health is some version of: "I didn't know I needed a referral to get started." It comes up again and again, and usually the family is already frustrated, because no one at the hospital or the doctor's office explained this step to them.
In Monterey County, many families are navigating a loved one's discharge from Community Hospital of the Monterey Peninsula or Salinas Valley Health for the first time. The process moves quickly, and the referral requirement can feel like a surprise obstacle when it should be a routine part of the discharge plan.
This article explains what a physician referral for home health actually is, how it gets started, and what your family's role looks like through the process, so you are not caught off guard when the moment comes.
What a Physician Referral for Home Health Actually Means
A physician referral is a written order from a licensed physician that does two things at once. It certifies that the patient has a medical need for skilled care at home, and it confirms that the patient meets the homebound standard Medicare requires.
Without this order, a home health agency cannot legally admit a patient for skilled services. That includes skilled nursing, physical therapy, occupational therapy, speech therapy, and wound care. It is not a paperwork formality, it is the clinical and legal authorization that makes Medicare coverage possible in the first place.
The referring physician also takes on an ongoing role. Medicare requires that a physician review and sign the patient's plan of care within a specific window after services begin, and that the plan be recertified if care continues beyond the initial period. So the referral is not a one-time event. It is the beginning of a documented, physician-supervised relationship between the patient and the home health team.
For a closer look at what happens once a skilled nurse actually arrives at the home, What Does a Skilled Nurse Actually Do on a Home Visit? walks through that process in plain terms.
What 'Homebound' Means, and Why It Trips People Up
The word "homebound" sounds more restrictive than it actually is. Many families assume it means their loved one cannot leave the house under any circumstances. That is not the standard.
Medicare considers a patient homebound when leaving the home requires considerable effort, meaning the patient uses a wheelchair, walker, or crutches, or has a condition that makes leaving medically inadvisable. The patient can still go to a medical appointment, attend a religious service, or step outside occasionally. What matters is that leaving is the exception, not the routine.
Families do not have to make this determination on their own. A Registered Nurse from the home health team will assess homebound status during the first visit. That assessment becomes part of the clinical record that supports Medicare billing.
Here are common situations that typically qualify:
- Recent surgery with limited mobility
- Recovering from a fall or fracture
- Significant weakness from a cardiac event or stroke
- A condition where leaving the home poses a genuine medical risk
- Dependence on a walker, wheelchair, or assistive device to leave safely
If you are unsure whether your family member qualifies, that question is worth asking a care coordinator directly rather than guessing.

How the Referral Process Actually Starts
Most families have no idea who initiates the referral, which is exactly where the confusion starts. The answer depends on where the patient is at the time.
If the patient is being discharged from a hospital: A hospital discharge planner or medical social worker typically handles the referral. At Community Hospital of the Monterey Peninsula or Salinas Valley Health, this is a standard part of the discharge planning process. The family does not have to track down a physician or submit paperwork on their own, the hospital team is supposed to coordinate this.
If the patient is already at home and the situation has changed, a new diagnosis, a fall, a medication issue, increasing difficulty managing daily tasks, the referral comes from the primary care physician. In this case, it often starts with a phone call to the doctor's office describing what has changed.
In both situations, the family does not have to manage this alone. A home health agency can also help facilitate the referral by sending the necessary paperwork directly to the physician's office. That removes most of the burden from the family.
For a broader look at what happens in the days right after a hospital stay, After the Hospital Discharge, What Comes Next? is worth reading before a discharge date arrives.
How a Home Health Referral Moves from Order to First Visit
This step-by-step flow shows what happens between a physician writing an order and a nurse arriving at the patient's home.
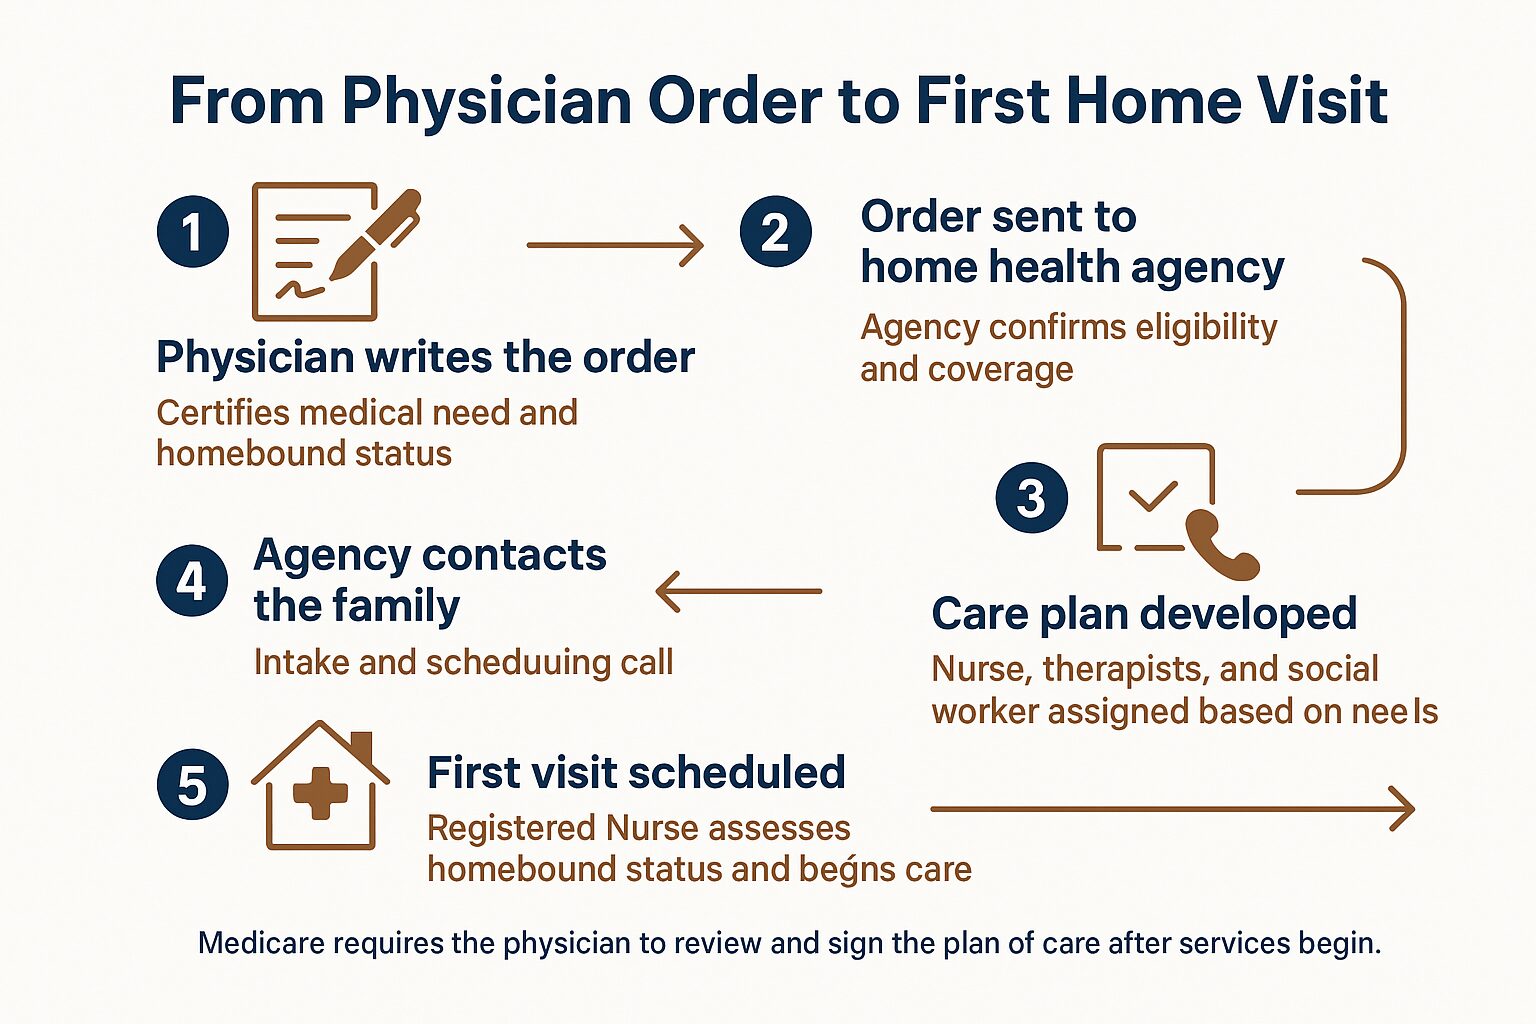
Hospital Discharge vs. Home-Based Referral: What's Different
The referral process looks slightly different depending on where the patient is when care is first needed. This table shows the key differences at a glance.
| Situation | Who Initiates the Referral | What the Family Typically Does |
|---|---|---|
| Patient being discharged from a hospital | Hospital discharge planner or medical social worker | Confirm the referral is in progress and state your agency preference |
| Patient already at home with a changing condition | Primary care physician (after a call or visit) | Contact the doctor's office and describe what has changed |
| Patient with a specialist managing a chronic condition | Specialist or primary care physician, coordinated together | Ask the specialist whether a home health referral is appropriate |
You Can Choose Your Own Home Health Agency
This is one of the most important things families do not know: Medicare gives patients the right to choose their own home health provider. A referring physician or discharge planner cannot require you to use a specific agency.
If a hospital social worker suggests a particular provider and you would prefer a local nonprofit organization, one that has served someone you know, or that has been part of the Monterey Peninsula community for decades, that choice is yours to make. You can say so directly, and the referral will be directed to the agency you select.
This matters because not all home health agencies are the same. Nonprofit agencies, for example, are structured differently from for-profit companies. The mission and the margins work differently. Families who do not know they have a choice sometimes end up with whichever agency is suggested first, rather than the one that actually fits their situation.
If you are trying to think through whether home health is even the right type of care for your loved one right now, Home Health vs. Hospice: How Families Know Which One Fits Right Now lays out the distinction clearly. And if a physician has raised the possibility of palliative care alongside treatment, What Palliative Care Actually Means, and When It Can Start is a useful read.
Frequently Asked Questions About the Home Health Referral Process
Can I request a home health referral myself, or does it have to come from the doctor?
The order itself has to come from a licensed physician, that is a Medicare requirement. But you can absolutely prompt the conversation. Call the doctor's office, describe what has changed with your loved one, and ask whether a home health referral is appropriate. Most physician offices are familiar with the process and can move quickly once the request is made.
What if the discharge planner at the hospital doesn't mention a referral?
Ask directly. Before a loved one leaves Community Hospital of the Monterey Peninsula or any other hospital, it is reasonable to ask the discharge team: "Is a home health referral being placed, and who is it going to?" You can also state your agency preference at that point. Discharge planners handle many cases at once, and a direct question ensures nothing is overlooked.
Does Medicare cover home health if I have a referral?
Medicare covers 100% of approved home health services when the patient meets eligibility criteria, including the homebound standard and a documented need for skilled care. There is no copay for home health under Medicare Part A or Part B when those criteria are met. The Medicare.gov home health coverage page has the full eligibility details straight from the source.
My mother's condition has been stable for months. Can she still qualify?
Stability alone does not disqualify a patient. Medicare allows home health services for patients managing chronic conditions, such as heart disease, COPD, or diabetes, when skilled care is needed to maintain that stability or prevent a decline. The key is that a Registered Nurse or therapist needs to be doing something that requires clinical training, not just general assistance.
How long does it take to get services started after a referral is sent?
Once a referral is received, many home health agencies aim to initiate contact with the family quickly, often within 24 to 48 hours for standard cases. For patients being discharged from the hospital, the goal is typically to have care in place before or immediately after the patient arrives home. If urgency is a factor, say so when you call.
What if my family member is not technically homebound but still needs skilled nursing at home?
If a patient does not meet the homebound standard, Medicare home health benefits would not apply. However, there may be other coverage options depending on the patient's insurance situation, and some services can be arranged privately. A care coordinator can help clarify what options exist based on the specific situation.
Questions About Getting Started With Home Health in Monterey County?
Central Coast VNA & Hospice has been supporting families across Monterey County, Santa Cruz County, San Benito County, and South Santa Clara County since 1951. If you are trying to figure out whether a referral is already in motion, which agency to request, or whether your family member qualifies for skilled care at home, a care coordinator can talk through the specifics with you. Call 831-372-6668 or visit ccvna.com to reach someone who knows this process and can help you take the right next step.

Finding Grief Support in Monterey County After a Loss
Losing someone you love is one of the hardest things a person goes through. And in the hours and days right after, one of the most common things people reach for is connection, someone who understands what this actually feels like.
For families in Monterey County, that search is real and immediate. A woman in Monterey recently submitted a message that said simply: she had lost her husband of 56 years the day before, he had been in hospice at Community Hospital of Monterey Peninsula, and she needed a local grief support group. That single message captures what many people in this situation feel, a need for something concrete, nearby, and soon.
This article explains what grief support actually looks like in practice, who it is for, and how people in communities like Monterey, Pacific Grove, Seaside, and Salinas can find their way to it.
What Grief Support Actually Looks Like
Many people have never used bereavement support before and aren't sure what to expect. There are two main forms, and they serve different needs.
One-on-one grief counseling involves meeting privately with a Bereavement Specialist, a trained professional who helps you process the emotional weight of loss over a series of conversations. This is a form of psychotherapy, though it doesn't feel clinical. It's a place to say what you can't easily say to the people around you.
Group support brings together people who have experienced similar losses, usually with a trained facilitator guiding the conversation. Groups are especially valuable for people whose grief feels invisible to those around them. Friends and family mean well, but they move on. A group stays with you.
Neither form requires you to have used a specific hospice or healthcare provider. Grief doesn't follow a schedule, and the support available to you doesn't either, both options are open to anyone in the community who has lost someone.
The two forms also aren't mutually exclusive. Some people start with a group and later move to individual counseling. Others do both at the same time. What matters is finding something that fits where you are.

Spousal Grief Is Different, and Often the Most Isolated
There is a reason the loss of a long-term spouse hits the way it does. When someone loses a partner of 50 or 60 years, they lose far more than one person. They lose a daily routine, a financial partner, a social anchor, and often their closest confidant.
Research from the National Institute on Aging shows that spousal bereavement carries real physical and mental health risks, particularly in the first year after a loss. Sleep changes, appetite loss, and depression are common, and often go unaddressed because the grieving person is focused on practical logistics rather than their own wellbeing.
In Monterey County, where a large portion of the population is older and long-term couples are common in communities like Carmel, Pacific Grove, and Pebble Beach, this situation is far from rare. But it is also easy to fall through the cracks, especially when friends and family assume that after a few months, things should be settling down.
They often don't. And that's something grief support groups understand in a way that general social networks usually don't. When mourning feels stuck, the problem isn't the person, it's that grief was never meant to be carried alone.
When People Search for Grief Support, and Why It's Never Too Late
Grief doesn't arrive on a schedule, and neither does the need for help. This shows when people most often reach out, and why any of these moments is the right time.
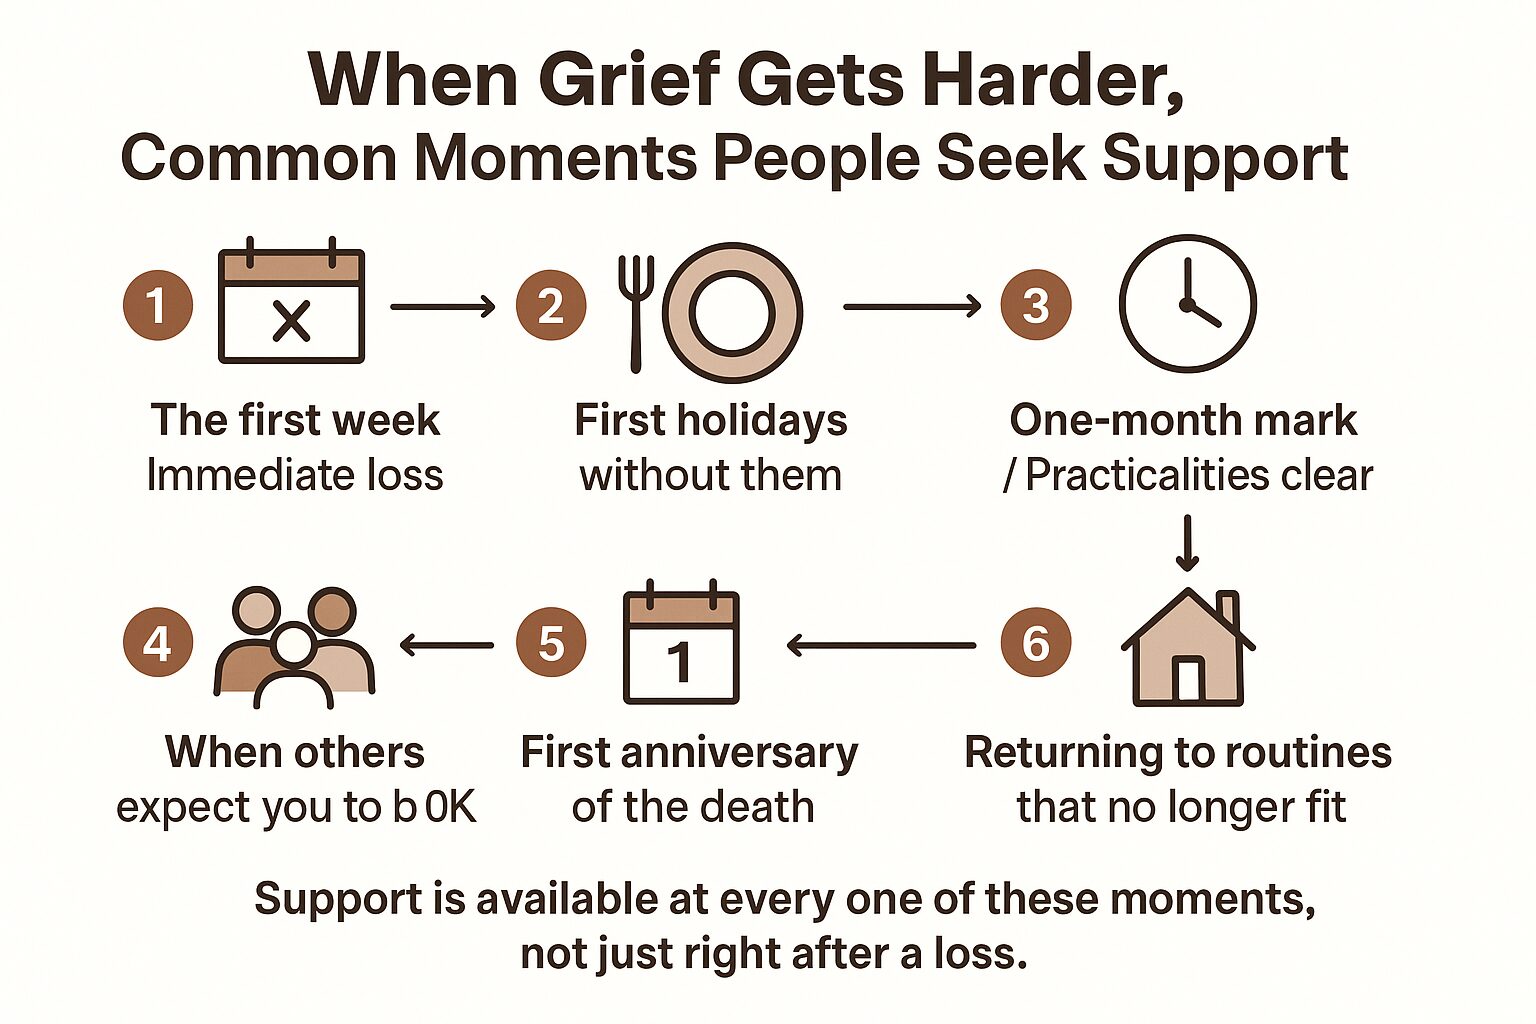
Grief Support Is Not Just for the Immediate Aftermath
People often search for grief support groups weeks or even months after a loss, not in the first few days. That's worth saying plainly, because many people assume they missed a window.
There is no window. Grief doesn't run on a linear track, and the need for support often intensifies at specific moments that come later:
- The first major holidays without the person who is gone
- The first anniversary of their death
- The point when other people seem to expect things to be back to normal
- Returning to routines, a morning coffee, a Sunday walk, that used to involve the person you lost
Someone who lost a spouse eight months ago and finds that it's getting harder rather than easier isn't doing anything wrong. That experience is documented and common. And it's exactly the kind of moment when a group of people who understand can make a real difference.
For adult children grieving a parent, which is also extremely common in Monterey County, the same applies. The loss of a parent reshapes a person's sense of place in the world, sometimes in ways that take months to fully register.
One-on-One Counseling vs. Group Support: A Quick Comparison
Both forms of bereavement support serve real needs, but they work differently. Here is how they compare across the factors most people ask about.
| Factor | One-on-One Counseling | Group Support |
|---|---|---|
| Setting | Private, with a Bereavement Specialist | Small group with a trained facilitator |
| Best for | Personal, specific grief work | Connection with others in similar situations |
| Requires prior relationship with hospice? | No | No |
| Cost | Varies; often covered by Medicare or insurance | Often low-cost or free through community programs |
| Availability in Monterey County | Yes, through community programs | Yes, through community and nonprofit programs |
| Timeline | Ongoing, at your pace | Scheduled sessions, often weekly or biweekly |
What's Available Locally, and Who Can Access It
In 2025, Central Coast VNA & Hospice expanded bereavement support to more than 2,200 individuals across its service area, according to the organization's annual report. That figure reflects a program operating at meaningful scale, with trained Bereavement Specialists and facilitated groups available to families across Monterey County.
Importantly, VNA's bereavement support is not limited to families who used VNA's hospice services. It is available to the broader community. Families in Salinas, Seaside, Pacific Grove, and King City can access the same support as anyone in Monterey proper, without needing a prior connection to the organization.
For people navigating the financial side of grief support, it's worth knowing that Medicare covers certain mental health and counseling services, and community-based grief programs through nonprofits are often low-cost or free. Costs vary depending on the type of support and how it's structured, so contacting a local program directly is the most reliable way to understand what applies to your situation.
If you are also trying to understand what the end-of-life care journey looked like for your loved one, or making sense of the decisions that were made, articles like what families often miss when planning a hospital discharge to home and how families describe the moment they chose hospice may offer some grounding as you process things.
Frequently Asked Questions About Grief Support in Monterey County
Do I have to have used VNA's hospice services to access their bereavement support?
No. Bereavement support through Central Coast VNA & Hospice is available to anyone in the community who has experienced a loss, not only families who were enrolled in their hospice program.
What if I'm not ready for a group? Can I start with individual counseling?
Absolutely. One-on-one sessions with a Bereavement Specialist are available and don't require you to participate in a group setting. Many people start there and later decide whether a group feels right for them.
Is there a cost for grief support groups?
It depends on the program. Community-based grief groups through nonprofits are often low-cost or free. Individual grief counseling may be covered in part by Medicare or private insurance, but costs vary. Contacting the program directly is the fastest way to find out what applies to your situation.
I lost my spouse eight months ago and I feel like it's getting harder, not easier. Is that normal?
Yes, and you are not alone in that experience. Grief often intensifies at specific points, the first holidays, the first anniversary, the moment when everyday life no longer fits the way it used to. Reaching out for support now, months after a loss, is exactly as valid as reaching out in the first week.
How do I find out when grief support groups meet in Monterey County?
The most direct step is to call or visit ccvna.com to ask about current group schedules and availability. Group meeting times and formats change, so checking directly gives you the most accurate information.
Ready to Find Local Grief Support?
If you are in Monterey County and looking for a grief support group or one-on-one bereavement counseling, Central Coast VNA & Hospice can help you understand what is available and when. You can reach their care team at 831-372-6668 or visit ccvna.com to learn more, no prior connection to their services is required to ask.

Hospice Criteria for Dementia: What Families Are Really Asking
Dementia is one of the hardest conditions for families to navigate when thinking about hospice. Unlike cancer or heart failure, it doesn't follow a predictable curve. It moves slowly, plateaus, then shifts again, and families often find themselves watching a parent decline for years without ever feeling certain that the moment has arrived.
Families across Monterey County ask versions of this question regularly. A daughter calling after a sleepless night. A son managing his father's medications alongside a cancer survivor mother. The situation is different each time, but the core question is always the same: how do we know when it's time?
This article won't give you a script or a shortcut. But it will walk through what the clinical markers actually look like in everyday life, what Medicare requires before hospice can begin, and how to start a conversation with a physician that most families wait too long to have.
What Does Medicare Actually Require for Hospice with Dementia?
Medicare's hospice benefit requires a physician to certify that the patient's life expectancy is six months or less if the disease runs its natural course. That standard applies to all diagnoses, but dementia makes it particularly hard to apply because the disease can stretch across a decade or more.
For dementia specifically, physicians look at a cluster of functional and medical changes that, taken together, indicate the illness has progressed to its final stage. There is no single test that triggers eligibility. It is a clinical picture built from several markers, assessed together.
The changes physicians and hospice nurses typically look for include:
- Significant weight loss, often 10% or more of body weight in six months, even when nutrition support is offered
- Recurrent infections, especially pneumonia or urinary tract infections that keep returning
- Severe loss of functional ability, the person can no longer walk without full physical support from another person
- Loss of meaningful verbal communication, speaking fewer than six intelligible words per day is one recognized threshold
- Inability to swallow safely, leading to choking, aspiration risk, or refusal to eat
These changes don't announce themselves on a single day. Families usually recognize them in hindsight, looking back at the last few months and realizing how much shifted. That's actually one of the most important things to understand: you don't have to wait for a crisis to ask whether hospice criteria have been met. A conversation with the physician can happen at any point. The hospice eligibility question most families are afraid to ask is often one of the most relieving ones to finally ask out loud.

When a Parent Has Dementia and Something Else Too
One situation that comes up regularly in conversations with Monterey County families involves a parent who has dementia alongside one or more other serious diagnoses. Heart failure and dementia. A cancer history and dementia. Diabetes and dementia. This is not unusual, it is actually the common picture for people in their 80s.
A family recently described their situation this way: an 83-year-old mother who is a cancer survivor, and an 86-year-old father who was recently diagnosed with dementia and takes more than five medications. Coordinating that care had become overwhelming.
When multiple serious conditions overlap, the path to hospice eligibility can shorten faster than families expect. A physician evaluating whether hospice criteria are met looks at the whole patient, not each diagnosis in isolation. Heart failure that is worsening alongside advanced dementia may meet eligibility thresholds much sooner than dementia alone would.
The harder truth is that many families don't bring this up with the physician because they aren't sure it's appropriate to ask. It is. Any family member can request that a physician assess whether their loved one may now qualify for hospice. The physician makes the determination, your job is to start the conversation.
If you are not yet at the hospice threshold but your loved one needs more support than they are getting, there is another option worth understanding before you get there.
What Is the Difference Between Palliative Care and Hospice for Someone with Dementia?
This distinction matters enormously, and many families searching for hospice information don't yet realize that palliative care exists as a separate, earlier option.
Palliative care can begin at any stage of dementia. It focuses on managing symptoms, reducing discomfort, supporting the family, and coordinating care, all while the patient continues whatever medical treatment the physician recommends. Choosing palliative care does not mean stopping treatment. It does not require a six-month prognosis.
Hospice begins when curative or life-prolonging treatment is no longer the goal, typically when a physician and family agree that comfort and quality of life matter more than further medical intervention.
For a family with a parent in early or middle-stage dementia who is struggling with symptoms, recurrent hospitalizations, or caregiver exhaustion, palliative care is often the right fit right now. Central Coast VNA & Hospice has offered a home-based palliative care program since 2015, and it remains available to patients across Monterey County, including Salinas, Hollister, and King City.
You can read more about what this program actually involves in what palliative care actually means, and when it can start. Understanding comfort care vs. hospice can also help clarify which path fits your family's situation right now.
Palliative Care vs. Hospice: A Side-by-Side Look for Dementia Families
This comparison shows the key differences between palliative care and hospice for patients with dementia, so families can identify which level of support fits their current situation.
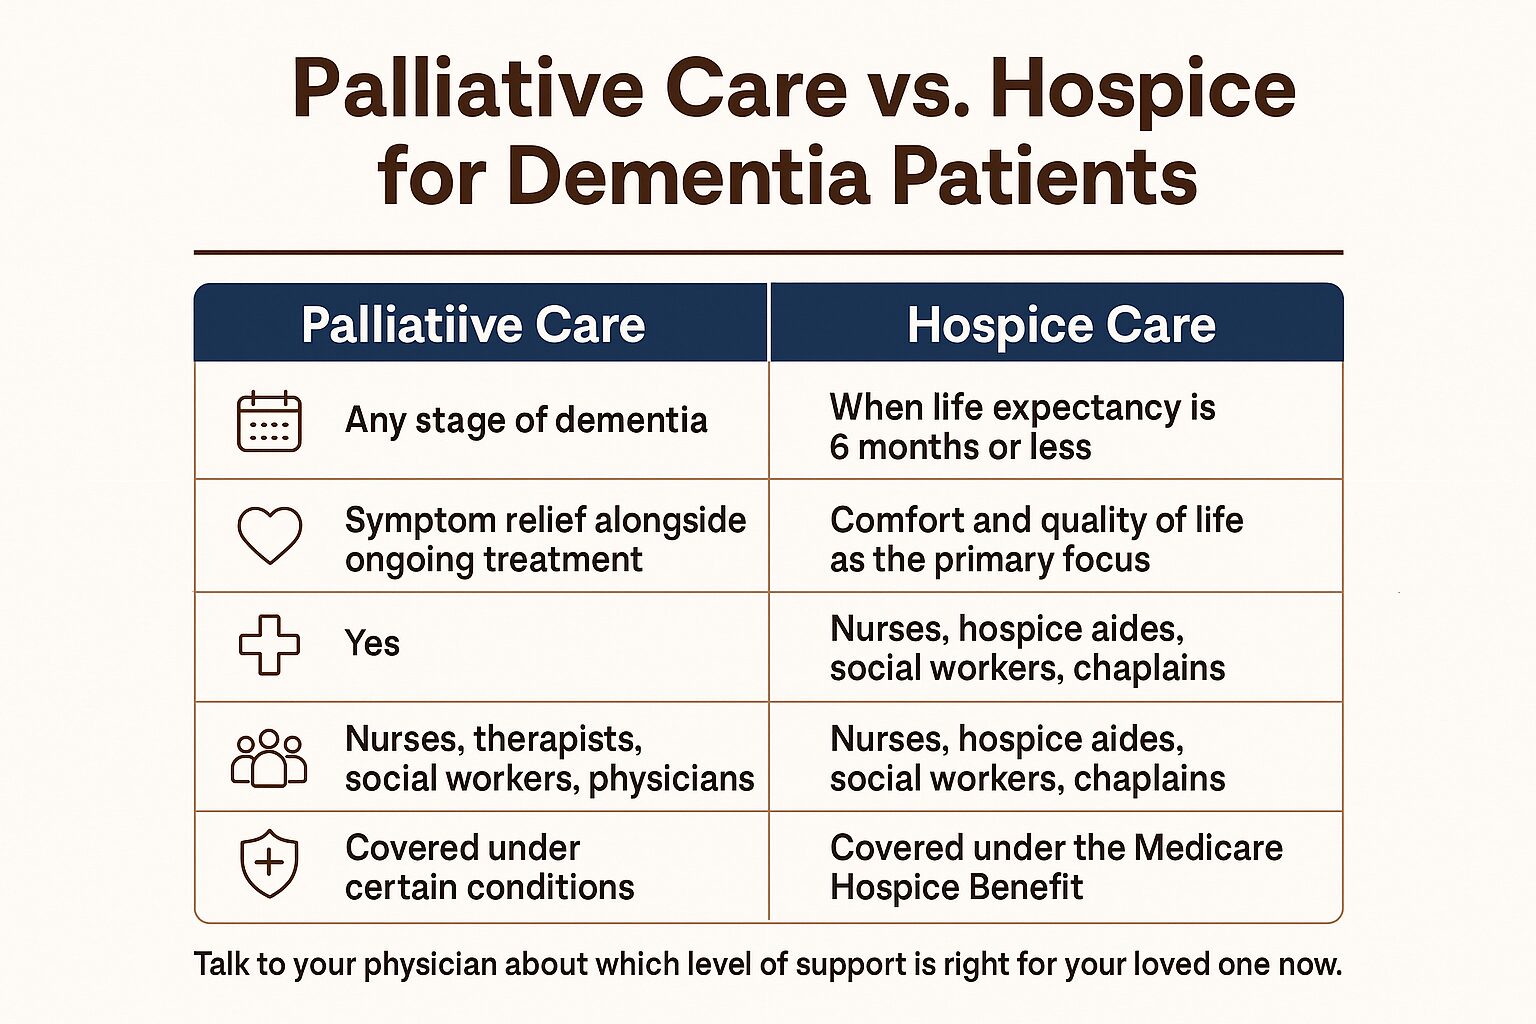
Dementia Hospice Eligibility: What Physicians Are Looking For
These are the clinical markers physicians commonly use when assessing whether a dementia patient may meet hospice eligibility. No single marker determines eligibility on its own, the physician looks at the full picture.
| Clinical Marker | What It Looks Like in Daily Life | Why It Matters |
|---|---|---|
| Significant weight loss | Losing noticeable weight over several months despite eating attempts | Signals the body is no longer able to maintain itself |
| Recurrent infections | Repeated bouts of pneumonia or urinary tract infections | Indicates the immune system is significantly weakened |
| Loss of mobility | Cannot stand or walk without full physical support from another person | Reflects late-stage neurological decline |
| Loss of verbal communication | Fewer than six intelligible words spoken per day | One recognized clinical threshold for late-stage dementia |
| Unsafe swallowing | Choking, gagging, or refusing food and liquids | Raises aspiration risk and signals end-stage progression |
Does Choosing Hospice Mean Giving Up on My Parent?
This fear is real, and it comes up constantly, in phone calls, in form submissions, in the hesitation families carry into every conversation about this topic. The word "hospice" can feel like a door closing.
But the clinical evidence points in a different direction. Many patients with dementia who transition to hospice stabilize in the early weeks of enrollment. With consistent pain and symptom management, fewer disruptive hospitalizations, and a team visiting regularly at home, some patients become more comfortable and more settled than they had been in months.
Hospice does not accelerate death. What it does is shift the focus from fighting a disease to caring for a whole person. According to research published by the National Hospice and Palliative Care Organization, hospice patients often report better symptom control and family members report less distress than those who do not enroll.
The interdisciplinary team on a hospice program includes nurses, Hospice Aides, a Medical Social Worker, a Chaplain, and Volunteers. That team addresses not just the physical symptoms your parent is experiencing, but the emotional and spiritual weight your entire family is carrying. For families in Monterey County who have been shouldering this alone, that kind of support often arrives as a genuine relief.
If you are still sorting through what to expect, how families describe the moment they chose hospice offers a grounded look at what that decision actually felt like for real families.
Frequently Asked Questions About Hospice and Dementia
Can someone with dementia qualify for hospice if they don't have another terminal diagnosis?
Yes. Dementia alone can meet hospice eligibility criteria when it has progressed to a late stage. Medicare does not require a secondary diagnosis. The physician must certify that the patient's life expectancy is six months or less based on the current trajectory of the disease, and late-stage dementia with the markers described above can meet that standard on its own.
What if my parent seems stable, can they still be evaluated for hospice?
Stability in dementia can be misleading. A person may appear calm or comfortable at home while still meeting hospice eligibility criteria based on weight, swallowing, mobility, or communication. "Stable" does not mean improving. A physician evaluation looks at the full clinical picture, not just how a patient seems on a given day. It is always appropriate to ask for that assessment.
Does Medicare cover hospice for dementia?
Yes. The Medicare Hospice Benefit covers hospice services when a physician certifies a terminal prognosis of six months or less. This includes nursing visits, Hospice Aide services, medication for comfort, medical equipment, and support for the family. Central Coast VNA & Hospice accepts Medicare, Medi-Cal, and Veterans benefits. For a full picture of what is covered and how to access it, a care coordinator can walk you through the specifics for your family's situation.
My parent has dementia and heart failure. Could they qualify sooner than I expect?
Quite possibly. When dementia overlaps with another serious condition, the combined effect on a patient's health often brings eligibility timelines forward. A physician evaluating hospice criteria looks at the whole patient, and two serious illnesses progressing together can meet the eligibility standard more quickly than either would alone. The important step is asking the physician to evaluate where things actually stand right now rather than waiting for an obvious crisis.
What if my parent isn't ready for hospice, is there anything in between?
Palliative care is exactly that. It can begin at any stage of dementia, continues alongside treatment, and focuses on symptom management, care planning, and family support. Central Coast VNA & Hospice has offered a home-based palliative care program in Monterey County since 2015, including Salinas, Hollister, and King City. If you are not sure whether your family is at the hospice threshold but know that more support is needed, what palliative care actually means, and when it can start is a good place to begin.
How do I start the conversation with my parent's doctor about hospice?
You can simply ask: "Has my parent reached the point where a hospice evaluation would make sense?" That is enough. Physicians are accustomed to this question, and a good physician will welcome it rather than dismiss it. If you are not sure how to frame the conversation or what to bring to the appointment, the article on advance care planning offers practical guidance for preparing for exactly this kind of discussion.
Not Sure Where Your Family Stands Right Now?
Families in Monterey County, Salinas, Hollister, King City, and the surrounding communities are welcome to call Central Coast VNA & Hospice at 831-372-6668 to speak with a care coordinator, no referral needed to start that conversation. If you would rather reach out online first, visit ccvna.com to learn more about the hospice and palliative care programs available in your area.