

Does your parent's POLST still work after California's January 1 change?
There is a pale pink sheet of paper taped to the side of your parent's refrigerator. You may not remember exactly what it says, but you know paramedics look for it. Families who contact us often describe it the same way: the colored paper form the paramedics ask about.
Then you hear that California changed the rules on January 1, 2027, and the worry sets in. Is the form on the fridge now worthless? Does your mom have to go back to her doctor and sign a new one?
The short answer is no, and this article walks through why. We will cover what SB 1088 actually changed, who can sign the forms now, and the one new protection that matters most for families comparing care options across Monterey County.
The short answer: January 1 did not void the form on your parent's fridge
SB 1088, authored by State Senator Catherine Blakespear, was approved by the Governor on September 27, 2026 and chaptered as Chapter 677, Statutes of 2026. It took effect January 1, 2027.
The law updates how these forms are named, signed, and dated going forward. It does not cancel orders that were already signed and in place.
So if your dad in Salinas completed a POLST with his cardiologist in 2023, that form still speaks for him. Emergency responders in Monterey County are still trained to look for it, and it still tells them whether he wants CPR, a breathing tube, or comfort-focused care at home.
What the law changes is the paperwork going forward. You can read the bill summary from the Office of California State Senator Catherine Blakespear, and CalMatters Digital Democracy tracked the bill through both chambers before it passed.
If your parent's form is faded, torn, or you cannot find it at all, that is a reason to get a fresh one. A law change by itself is not.

What SB 1088 actually changed
The bill makes several practical updates. Here is the list, in plain terms:
- The name changed. POLST now stands for Portable Orders Listing Scope of Treatment instead of Physician Orders for Life Sustaining Treatment. The four letters stay the same.
- Electronic signatures are allowed on requests regarding resuscitative measures.
- Nurse Practitioners and Physician Assistants can sign the prehospital do-not-resuscitate form. Previously that signature came from a narrower group of providers.
- The forms must be dated. A missing date used to create real confusion in the field.
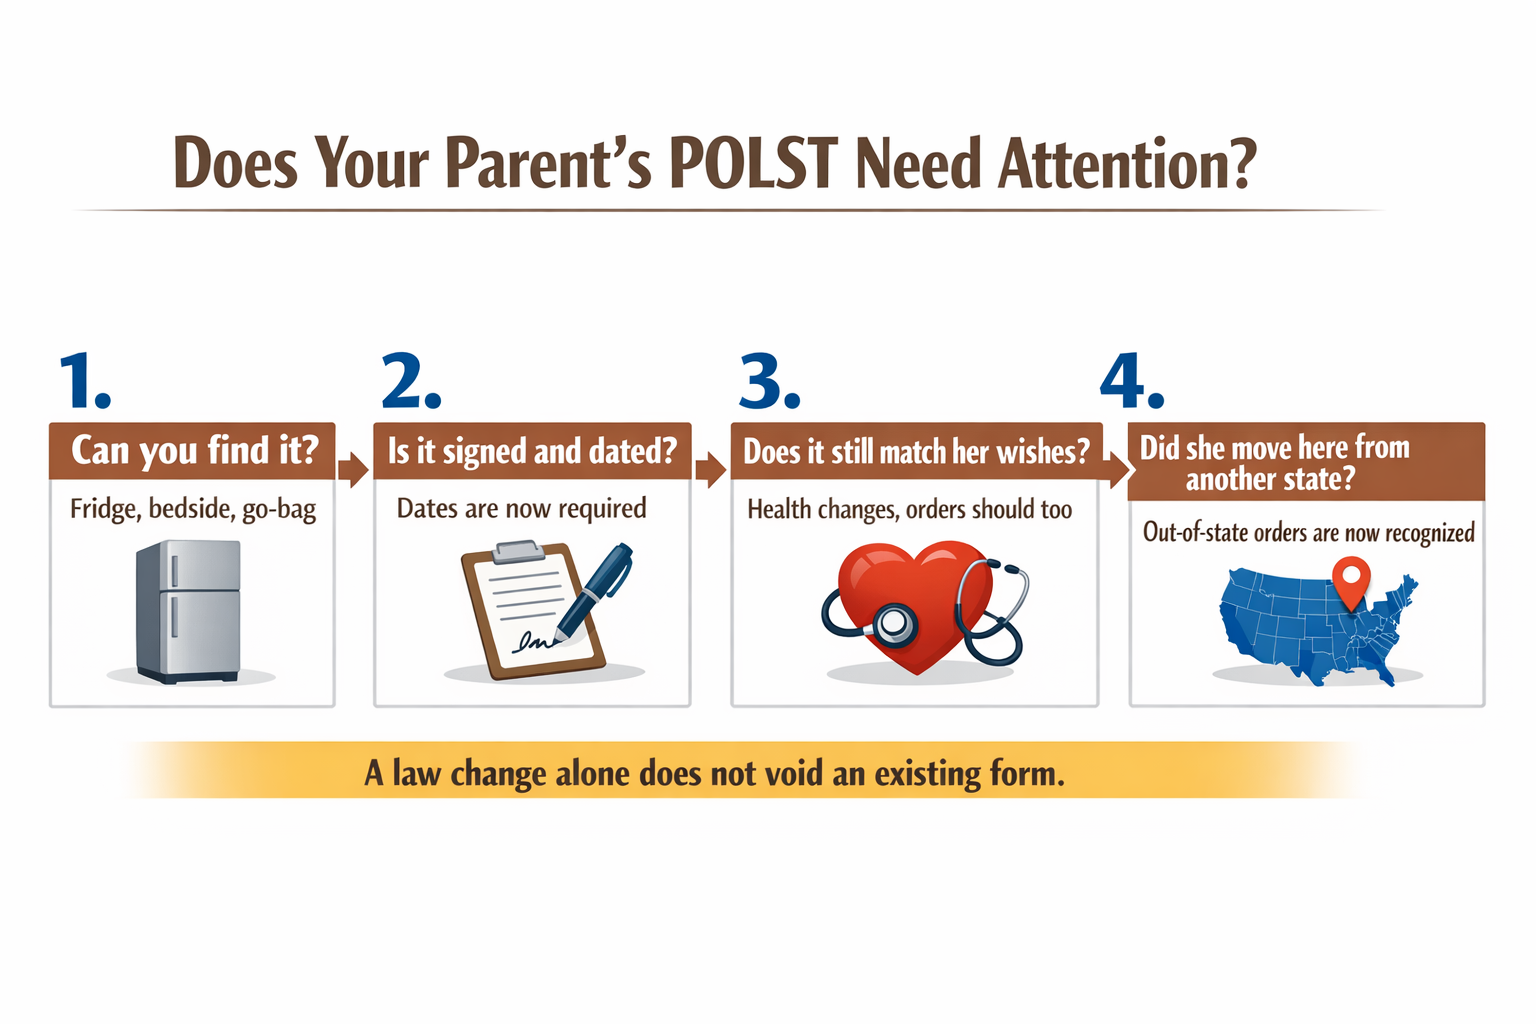
- Out-of-state POLST and DNR orders are recognized in California.
- Completing one is voluntary. It cannot be made a condition of care or of admission to a facility.
None of those changes reach backward. They shape the next form your parent signs, not the one already hanging in the kitchen.
If you want a side-by-side look at which documents are worth re-signing and which are fine as-is, we covered that separately in California POLST and DNR forms change January 1: what to re-sign.
Before and after January 1, 2027
A quick reference for the pieces families ask about most.
| Item | Before January 1, 2027 | On and after January 1, 2027 |
|---|---|---|
| Form name | Physician Orders for Life Sustaining Treatment | Portable Orders Listing Scope of Treatment |
| Existing signed forms | Valid | Still valid, no re-signing required |
| Who signs the prehospital DNR | Narrower set of providers | Also Nurse Practitioners and Physician Assistants |
| Signatures | Wet signature expected | Electronic signatures allowed on resuscitative measure requests |
| Date on the form | Not consistently required | Required |
| Out-of-state orders | Unclear standing in California | Recognized |
| Required for admission | Sometimes pressured | Voluntary, cannot be a condition of care or admission |
Does your parent's form need attention?
Four quick checks that tell you whether to leave the form alone or ask the doctor for a new one.
Who can sign now, and why the date matters
The signature change sounds small. In South Monterey County it is not.
Families in King City, Greenfield, and the farther reaches of San Benito County often see a Nurse Practitioner or Physician Assistant as their regular provider. Waiting weeks for a physician appointment just to get a signature was a real barrier. Letting those clinicians sign the prehospital DNR closes that gap.
The dating requirement matters for a different reason. Paramedics arriving at 2 a.m. have seconds to decide whether a form is current and whether it belongs to the person in front of them.
An undated form invites hesitation. A dated one does not.
There is generally no charge for the form itself, though an office visit to discuss it may be billed like any other appointment. Coverage depends on the plan, so it is worth asking the provider's front desk before you go. For a plain-language breakdown of how this form differs from a standard DNR, see what the colored paper form paramedics ask about really is.
No facility can require a POLST to admit your parent
This is the line in SB 1088 that families should remember. Completing a POLST is voluntary, and it cannot be made a condition of care or of admission to a facility.
If a skilled nursing facility or residential community tells your mother she has to sign one before she can move in, that is not how the law reads. She can say no, or say not yet, and still be admitted.
The out-of-state recognition piece pairs with this. About a quarter of the families who call us are coordinating from somewhere else, sometimes from another state, trying to get a parent settled on the Peninsula or in Salinas.
If your father completed a POLST in Oregon or Arizona and then moved in with you in Marina, California now recognizes that order. You should still review it with his new provider here, because his health may have changed since he signed it. But the document does not evaporate at the state line.
What to actually do in the next month
Four steps, and none of them require an attorney.
- Find the form. Fridge door, bedside drawer, hospital discharge folder. If it is not somewhere a stranger could spot it in thirty seconds, move it.
- Check for a signature and a date. If either is missing, ask the provider's office for a fresh copy at the next visit.
- Read it out loud with your parent. Orders written during a 2022 hospital stay may not reflect what she wants today.
- Tell the people who need to know. Siblings, the primary care office, and anyone providing care in the home.
One more thing worth saying plainly. A POLST is not a hospice form, and signing one does not start hospice or end treatment. It is a medical order about what happens in an emergency.
Families weighing bigger decisions often find it helps to understand the sequence first. We walked through that timeline in the first 48 hours after a family calls about hospice.
Frequently Asked Questions About California POLST Changes in 2027
Does my mom have to re-sign her POLST because of SB 1088?
No. A POLST signed before January 1, 2027 remains valid. Re-sign it if her health or her wishes have changed, if the form is damaged, or if it is missing a signature or a date, not because of the law itself.
Is a POLST the same thing as a DNR?
They are related but not identical. A DNR addresses CPR specifically. A POLST covers a broader set of medical orders, including whether your parent wants a breathing tube, hospital transfer, or comfort-focused care at home. Many people in Monterey County have one, not both.
Can a nursing home refuse to admit my father if he will not sign one?
Under SB 1088, completing a POLST is voluntary and cannot be a condition of care or admission to a facility. If you are told otherwise, ask for it in writing and raise it with the facility administrator.
My parent signed a POLST in another state. Does it count here?
As of January 1, 2027, California recognizes out-of-state POLST and DNR orders. Still, review it with her new provider on the Central Coast so the orders match her current condition.
Who should actually have a copy?
Keep the original somewhere visible in the home, usually the refrigerator. Give copies to the primary care office, any specialist actively treating her, and the adult child most likely to be called first. If she travels between homes, send a copy with her.
Does signing a POLST mean we are giving up on treatment?
No. It records what she wants in an emergency, nothing more. People with POLST forms continue chemotherapy, surgery, dialysis, and rehab every day.
Still unsure what your parent's paperwork means?
Sorting through advance directives, POLST forms, and care options is a lot to carry alone, especially when a parent's health is shifting. Central Coast VNA & Hospice has supported families across Monterey County and the surrounding Central Coast since 1951, and a care coordinator can talk through where things stand without any pressure to start services. You can reach the team at 831-372-6668 or find more information at ccvna.com.

Medi-Cal Asset Limit Falls to $21,000 on July 1, 2027
If your mother qualifies for Medi-Cal today with a modest savings account, she may not qualify in the summer of 2027. Under current California law, the asset limit drops sharply on July 1, 2027, and the change hits exactly the people who rely on it most: seniors, disabled adults, and anyone who needs nursing home or other long term care.
For families across the Monterey Peninsula, Salinas, King City, and Hollister, this is not an abstract policy debate. It changes how you plan for in-home nursing, long term care, and the support that comes with a serious illness.
Here is what changes, who it applies to, and what matters in the months before the date arrives.
What the 2027 Medi-Cal asset limit change actually says
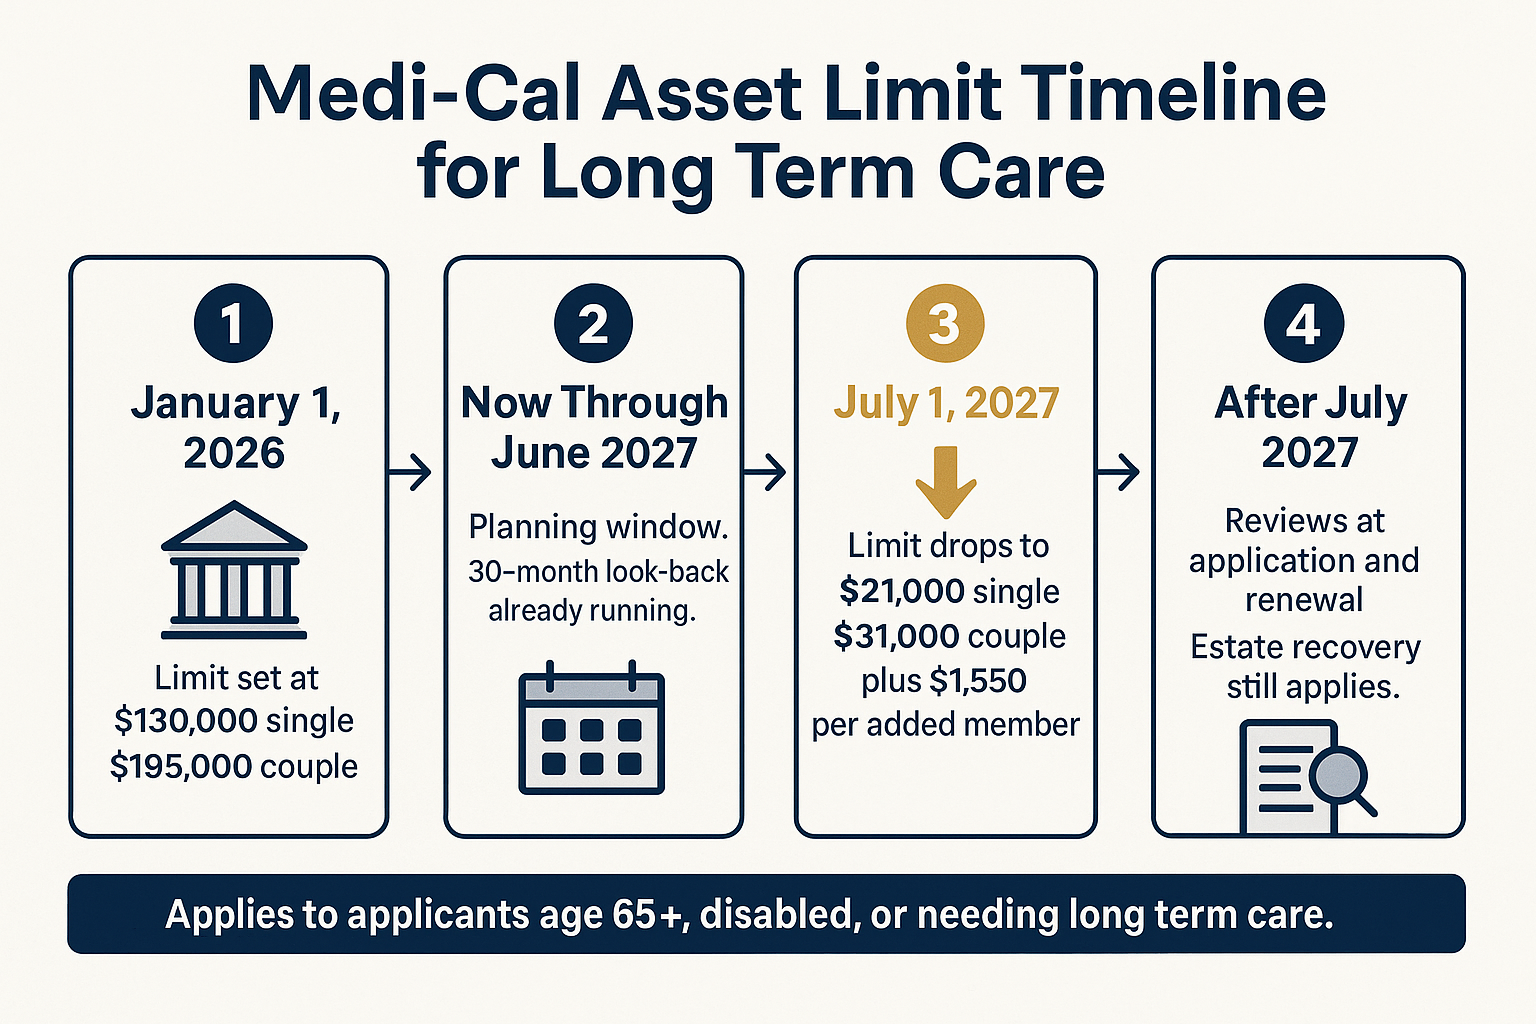
California eliminated most asset counting in 2024, then brought a limit back. The current limit of $130,000 for an individual and $195,000 for a couple took effect January 1, 2026.
Starting July 1, 2027, that limit drops to:
- $21,000 for an individual
- $31,000 for a married couple
- Plus $1,550 for each additional qualifying household member, up to 10 people
That is a drop of $109,000 for a single person. Someone who qualifies comfortably today could be over the line overnight.
Who does it apply to? The change primarily affects Medi-Cal applicants and members who qualify based on age (65 or older), a disability, or a need for nursing home or other long-term care. It is not aimed at working-age adults who qualify through income-based categories.
One detail worth holding onto: implementation is tied to the Department of Health Care Services having its systems ready, and the change can occur no sooner than July 1, 2027. DHCS has posted the schedule on its consumer Medi-Cal Help Center and asset limit FAQ pages. You can check current guidance directly with the California Department of Health Care Services. Analyses from elder law practices including Orange County Elder Law and Ridley Law Offices describe the same schedule.

The 30-month look-back is why timing matters now
Families often assume the answer is simple: move the money. It is not that simple, and the reason is the look-back period.
In California, the look-back for nursing facility level of care is 30 months. That means when someone applies, the county can review asset transfers made during the two and a half years before the application.
Do the math backward from July 1, 2027. Transfers made today already sit inside a 30-month window for an application filed in 2028 or 2029.
A few things families get wrong:
- Revocable living trusts do not hide assets. DHCS counts revocable trust assets as available to you while you are alive. The benefit shows up later, by keeping assets out of probate and therefore out of the state's estate recovery claim.
- Gifting to adult children is not a free move. An untimed transfer can create a penalty period right when care is needed.
- Spend down is not the same as spending. Paying off a mortgage, repairing a roof, or buying needed medical equipment is different from handing cash to a relative.
This is attorney territory, not blog territory. If your family is weighing long term care in Monterey County, an elder law attorney licensed in California should look at the actual numbers before anyone moves a dollar.
Current limit versus the July 1, 2027 limit
Here is the side-by-side, based on the schedule in current California law.
| Household | Now (since Jan 1, 2026) | Starting July 1, 2027 |
|---|---|---|
| One person | $130,000 | $21,000 |
| Married couple | $195,000 | $31,000 |
| Each additional qualifying member | Not applied the same way | Add $1,550, up to 10 people |
| Who it applies to | Age 65+, disabled, or long term care need | Same groups |
| Look-back for nursing facility level of care | 30 months | 30 months |
The timeline families should be working from
A simple view of the dates that matter and what belongs in each window.
What this means for care at home on the Central Coast
Most families in Monterey County are not planning for a nursing home. They are trying to keep a parent in the house in Marina, Seaside, Greenfield, or Carmel for as long as it is safe.
That distinction matters, because Medi-Cal and Medicare cover different things.
- Medicare covers physician-ordered, intermittent skilled home health: nursing visits, wound care, medication management, physical therapy, occupational therapy, speech therapy. It also covers the hospice benefit.
- Medi-Cal is the program that carries long term care costs, including nursing facility care, and it fills gaps for people who are dual eligible.
- Non-medical help with cooking, cleaning, and rides to appointments is a separate category, and it is the one families most often pay for out of pocket.
In Monterey County, most Medi-Cal members get their care through the Central Coast Alliance for Health. Plan rules shape which agencies a family can use, which is a separate headache from eligibility. We cover that issue in when your Medicare plan limits which home health agency you can use.
Private-pay in-home help is expensive on the Peninsula. Rates vary a lot by hours, overnight coverage, and agency, so get a written quote rather than trusting a number you read online. If a family drops off Medi-Cal in 2027 and has to self-fund, that gap is where savings disappear fastest. How long you can age in place usually comes down to exactly this math.
Four things worth doing before July 2027
You do not need to solve everything this month. You do need to stop treating 2027 as far away.
- Find out which Medi-Cal category your parent is in. Age-based, disability-based, and long term care eligibility are the categories affected. A county eligibility worker can confirm it.
- Write down the actual assets. Checking, savings, CDs, a second vehicle, life insurance cash value. The primary residence is treated differently from cash, and that difference drives most planning.
- Talk to a California elder law attorney, not a general financial advisor. The 30-month look-back makes timing the whole game, and bad timing is expensive to undo.
- Get the care paperwork in order while your parent can still participate. Advance directives, a POLST, and a named decision-maker. Advance care planning is not just paperwork, and it is far easier to complete before a hospital stay than during one.
If your parent is a veteran, add one more item to the list. VA benefits sit alongside Medicare and Medi-Cal, and families routinely miss them. Veterans and home-based care walks through what to ask about.
Frequently Asked Questions About the 2027 Medi-Cal Asset Limit
Will my mom automatically lose Medi-Cal on July 1, 2027?
Not automatically. The limit changes, and eligibility gets reviewed at application and at renewal. But if her countable assets sit above $21,000 at that point, she is at real risk of losing coverage, which is why families are looking at this now rather than in 2027.
Does the house count toward the $21,000 limit?
A primary residence has historically been treated differently from cash and investments, and rules around it are detailed. Do not assume either way. Confirm with the county or an elder law attorney before making any decision about the home, especially if estate recovery is a concern.
Can I just put everything in a living trust?
A revocable living trust will not get assets below the limit. DHCS counts revocable trust assets as available to you while you are alive. The trust's value shows up later, by keeping assets out of probate and therefore out of the state's recovery claim. Those are two different goals.
Does this change affect hospice coverage?
Hospice for most patients 65 and older is covered through the Medicare hospice benefit, which is a separate program from Medi-Cal. The asset limit change matters more for long term care and for dual eligible patients. If your family is weighing options, how to know when it is time to consider hospice is a better starting point than the finances.
What is the look-back period if we move money now?
30 months for nursing facility level of care in California. Count backward from the application date, not from today. A transfer made in late 2026 is still inside the window for an application filed in early 2029.
Could the state push the date back again?
Possibly. Implementation is tied to the Department of Health Care Services having its systems ready, and the change can occur no sooner than July 1, 2027. Plan for the date in current law, and check DHCS guidance before you rely on a delay.
Sorting out care at home while the rules are changing
Eligibility questions are for the county and an elder law attorney. Questions about what skilled nursing, therapy, palliative care, or hospice at home actually looks like in Monterey County are ones a care coordinator can talk through with you, without pressure. Central Coast VNA & Hospice has been part of this region since 1951 and accepts Medicare, Medi-Cal, and Veterans benefits. You can reach a care coordinator at 831-372-6668 or read more at ccvna.com.

How Do You Get Your Dog Certified as a Therapy Animal?
Direct Answer: You register through a recognized therapy animal organization. The path is usually a temperament and obedience evaluation, one or more supervised visits, then formal registration with proof of vaccinations and a recent vet exam.
You have watched your dog work a room. He leans into strangers, ignores the vacuum, and has never once flinched at a wheelchair at the Monterey Bay Coastal Trail. Someone has probably told you he would make a great therapy dog.
Then you look into it and hit a wall of acronyms. TDI, ATD, Pet Partners, CGC. It is not clear which one matters, what the test involves, or whether your dog would actually pass.
That confusion shows up in the numbers. Pet therapy volunteer posts get more engagement than any other volunteer content local hospice programs share, but the applications never match the interest. This guide walks through what certification really requires, what evaluators look for, and what visiting looks like once you are approved.
What “certified therapy dog” actually means
There is no state license for therapy dogs in California and no government registry. When people say “certified,” what they usually mean is registered with a national therapy animal organization that tested your dog and carries liability insurance for your visits.
That registration is what hospitals, skilled nursing facilities, and home-based hospice programs across Monterey County ask to see before you walk in the door. Without it, most programs cannot accept you, no matter how sweet your dog is.
It also helps to know what a therapy dog is not:
- Service dog: individually trained to do tasks for one person with a disability. Has public access rights under the ADA.
- Emotional support animal: provides comfort to its owner. No task training, no public access rights.
A therapy dog, by contrast, is trained and evaluated to visit other people, by invitation, in a facility or private home. No public access rights.
That last distinction matters. A therapy dog goes where he is invited, on a schedule, as part of a care team. The American Veterinary Medical Association keeps a clear breakdown of these animal-assisted intervention definitions if you want the clinical version.
The three organizations most Central Coast handlers use
Three registries come up again and again: Therapy Dogs International (TDI), Alliance of Therapy Dogs (ATD), and Pet Partners. All three are recognized by facilities on the Peninsula. They just get you there differently.
Therapy Dogs International runs a single hands-on test with a certified evaluator. The test borrows heavily from the AKC Canine Good Citizen exam and adds exposure to medical equipment like crutches and wheelchairs. Dogs generally must be at least one year old and have a current vet health record on file.
Alliance of Therapy Dogs tests the handler and dog together, then requires a set of supervised visits with a tester observing before you are registered. If you learn better by doing, this path gives you real practice before you are on your own.
Pet Partners asks the handler to complete a course first, then evaluates the team. It registers species beyond dogs and typically renews every two years rather than annually.
One practical Monterey County note: evaluators are not on every corner. Depending on the organization and the season, you may need to drive to Salinas, San Jose, or a scheduled group test date to get evaluated. Start by asking each organization where its nearest tester is before you commit.
Comparing the three main registration paths
Fees and requirements change, so treat this as general market context and confirm current details directly with each organization.
| Organization | How evaluation works | Typical cost and renewal |
|---|---|---|
| Therapy Dogs International | One in-person test with a certified evaluator, including exposure to medical equipment and unfamiliar people | Costs vary, but testing plus first-year membership commonly lands in the low to mid double digits. Annual renewal. |
| Alliance of Therapy Dogs | Handler and dog tested together, followed by supervised visits observed by a tester | Application and membership fees are usually modest, often somewhere in the $30 to $100 range combined. Annual renewal. |
| Pet Partners | Handler completes a course first, then the team is evaluated together | Course plus team evaluation and registration typically runs higher than the other two. Renews about every two years. |
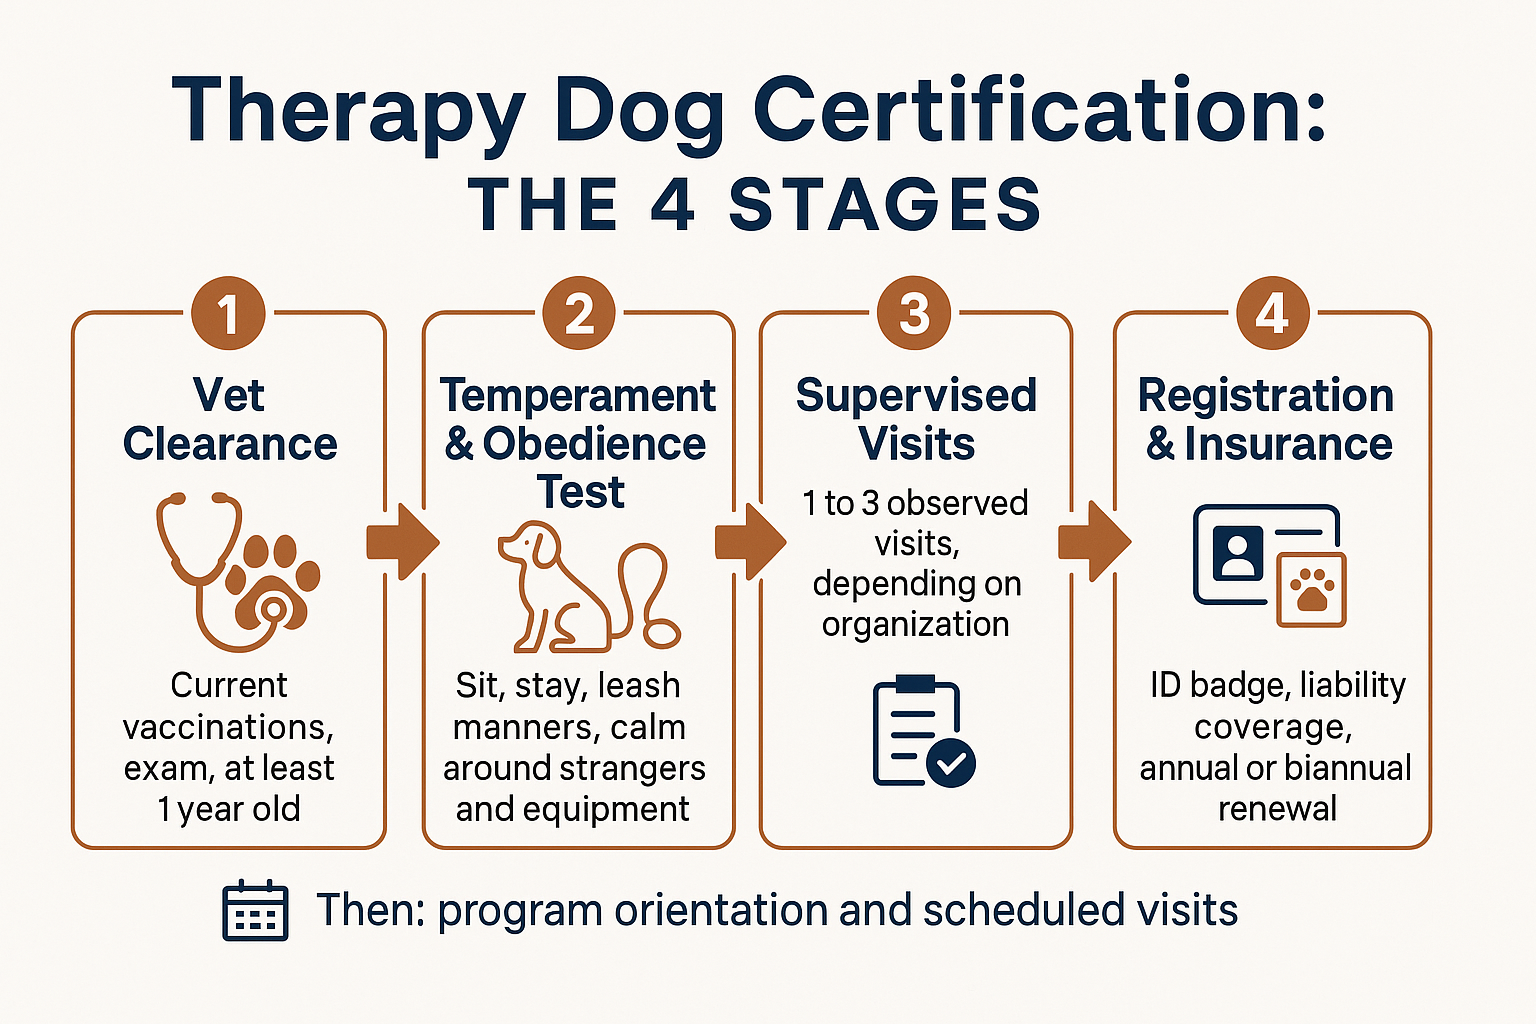
The certification path, step by step
Most first-time handlers move through four stages. Knowing the order up front keeps the process from feeling like a maze.
What evaluators are really looking for
Before you pay any fees, sit down and assess your dog honestly. Evaluators are not looking for tricks or a competition-level heel. They are looking for a dog who stays calm when things get strange.
Here is what tends to decide pass or fail:
- Neutral response to strangers. The dog accepts petting from someone unfamiliar without jumping, mouthing, or shrinking away.
- Comfort around medical equipment. Walkers, wheelchairs, oxygen tubing, hospital beds, and the beeping that comes with them.
- Reliable basic obedience. Sit, down, stay, come, and walking on a loose leash without pulling.
- Recovery after a startle. A dropped tray or a raised voice happens. The dog can flinch. He needs to settle within seconds.
- No interest in food on the floor. Dropped pills and dropped snacks are real hazards in a patient’s home.
- Tolerance of clumsy handling. Hands that grip fur too hard or pat too heavily are common from someone with limited strength or dementia.
A dog who barks at the door, guards you, or gets wound up around other dogs is not disqualified for life. He is just not ready. Six months of steady work with a local trainer, plus practice walks near busy spots like the Del Monte Center parking lot, can change that answer.
One honest filter: therapy work asks more of the handler than the dog. You are reading the room, watching your dog for stress signals, and knowing when to end a visit early.
What visiting actually looks like once you are registered
Registration is the paperwork. The part people underestimate is what comes after.
Most local hospice and home health programs add their own onboarding on top of your national registration. Expect a volunteer application, a background check, a TB test, an orientation covering patient privacy and infection control, and a match with a volunteer coordinator who knows the families.
Then you get scheduled. Pet therapy visits in a program like Central Coast VNA & Hospice usually happen in private homes across Monterey, Carmel, Seaside, Salinas, and out to King City and Hollister, not in a facility lobby. You visit the same patients over time, which is the whole point.
You are also one part of a larger team. Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, Hospice Aides, Chaplains, and other Volunteers are all working the same care plan. Your visit gets coordinated around theirs, which is why home health visit schedules tend to be set in advance rather than day of.
The work itself is quieter than people expect. A dog resting his head on a bed rail while a patient who cannot speak easily strokes his ears. Companionship for a spouse who has not left the house in a week. Presence during a long afternoon.
In 2025 alone, volunteers across this region contributed close to 40,000 hours and more than 1,080 visits, accounting for over 5% of all direct hospice care. That is not a side program. It is built into how care gets delivered.
Frequently Asked Questions About Therapy Dog Certification
How long does the whole process take from start to finish?
Plan on two to four months for most people. The evaluation itself is under an hour, but scheduling with an evaluator, completing supervised visits, and getting through a program’s volunteer onboarding takes the bulk of the time. If your dog needs obedience work first, add several months to that.
Does my dog need to be a specific breed or size?
No. Temperament decides it, not breed. Small dogs work well for bedside visits because they can be lifted onto a lap or bed, and large calm dogs work well for patients who want to reach down and pet without bending. What matters is that the dog is at least a year old, has lived with you long enough for you to read him honestly, and stays steady in a strange room.
Do I need a Canine Good Citizen title first?
It is not required, but it helps. The CGC test overlaps heavily with therapy dog evaluations, so passing it first is good practice and tells you whether the real test is worth scheduling.
Can my dog visit hospice patients if he is certified but I am not affiliated with a program?
Generally no. Visits to patients happen through an established program that handles patient consent, privacy rules, infection control, and scheduling. Showing up independently is not an option, which is why registration and volunteer onboarding go together.
What if my dog fails the evaluation?
Most organizations let you retest after a waiting period, usually several months. Ask the evaluator exactly what the dog struggled with. Reactivity around other dogs and startle recovery are the two most common issues, and both respond well to focused training with a local trainer.
Are there volunteer roles if my dog is not a good fit?
Yes, and they are needed. Vigil sitting, companionship visits, reading aloud, respite so a family member can run errands, and office support are all real roles. One long-time VNA volunteer described the work simply: sitting bedside, providing comfort, being present when it matters most.
Thinking about pet therapy volunteering on the Central Coast?
VNA has been serving families in Monterey, San Benito, Santa Cruz, and South Santa Clara counties since 1951, and 2026 marks its 75th year. A new pet therapy volunteer joins a program with decades of structure behind it, not one being figured out from scratch. If you want to talk through whether your dog is a fit, or ask about other volunteer roles, you can reach a coordinator at 831-241-8423 or find details at ccvna.com.

Hospice Criteria for Dementia: What Families Are Really Asking
Dementia is one of the hardest conditions for families to navigate when thinking about hospice. Unlike cancer or heart failure, it doesn't follow a predictable curve. It moves slowly, plateaus, then shifts again, and families often find themselves watching a parent decline for years without ever feeling certain that the moment has arrived.
Families across Monterey County ask versions of this question regularly. A daughter calling after a sleepless night. A son managing his father's medications alongside a cancer survivor mother. The situation is different each time, but the core question is always the same: how do we know when it's time?
This article won't give you a script or a shortcut. But it will walk through what the clinical markers actually look like in everyday life, what Medicare requires before hospice can begin, and how to start a conversation with a physician that most families wait too long to have.
What Does Medicare Actually Require for Hospice with Dementia?
Medicare's hospice benefit requires a physician to certify that the patient's life expectancy is six months or less if the disease runs its natural course. That standard applies to all diagnoses, but dementia makes it particularly hard to apply because the disease can stretch across a decade or more.
For dementia specifically, physicians look at a cluster of functional and medical changes that, taken together, indicate the illness has progressed to its final stage. There is no single test that triggers eligibility. It is a clinical picture built from several markers, assessed together.
The changes physicians and hospice nurses typically look for include:
- Significant weight loss, often 10% or more of body weight in six months, even when nutrition support is offered
- Recurrent infections, especially pneumonia or urinary tract infections that keep returning
- Severe loss of functional ability, the person can no longer walk without full physical support from another person
- Loss of meaningful verbal communication, speaking fewer than six intelligible words per day is one recognized threshold
- Inability to swallow safely, leading to choking, aspiration risk, or refusal to eat
These changes don't announce themselves on a single day. Families usually recognize them in hindsight, looking back at the last few months and realizing how much shifted. That's actually one of the most important things to understand: you don't have to wait for a crisis to ask whether hospice criteria have been met. A conversation with the physician can happen at any point. The hospice eligibility question most families are afraid to ask is often one of the most relieving ones to finally ask out loud.

When a Parent Has Dementia and Something Else Too
One situation that comes up regularly in conversations with Monterey County families involves a parent who has dementia alongside one or more other serious diagnoses. Heart failure and dementia. A cancer history and dementia. Diabetes and dementia. This is not unusual, it is actually the common picture for people in their 80s.
A family recently described their situation this way: an 83-year-old mother who is a cancer survivor, and an 86-year-old father who was recently diagnosed with dementia and takes more than five medications. Coordinating that care had become overwhelming.
When multiple serious conditions overlap, the path to hospice eligibility can shorten faster than families expect. A physician evaluating whether hospice criteria are met looks at the whole patient, not each diagnosis in isolation. Heart failure that is worsening alongside advanced dementia may meet eligibility thresholds much sooner than dementia alone would.
The harder truth is that many families don't bring this up with the physician because they aren't sure it's appropriate to ask. It is. Any family member can request that a physician assess whether their loved one may now qualify for hospice. The physician makes the determination, your job is to start the conversation.
If you are not yet at the hospice threshold but your loved one needs more support than they are getting, there is another option worth understanding before you get there.
What Is the Difference Between Palliative Care and Hospice for Someone with Dementia?
This distinction matters enormously, and many families searching for hospice information don't yet realize that palliative care exists as a separate, earlier option.
Palliative care can begin at any stage of dementia. It focuses on managing symptoms, reducing discomfort, supporting the family, and coordinating care, all while the patient continues whatever medical treatment the physician recommends. Choosing palliative care does not mean stopping treatment. It does not require a six-month prognosis.
Hospice begins when curative or life-prolonging treatment is no longer the goal, typically when a physician and family agree that comfort and quality of life matter more than further medical intervention.
For a family with a parent in early or middle-stage dementia who is struggling with symptoms, recurrent hospitalizations, or caregiver exhaustion, palliative care is often the right fit right now. Central Coast VNA & Hospice has offered a home-based palliative care program since 2015, and it remains available to patients across Monterey County, including Salinas, Hollister, and King City.
You can read more about what this program actually involves in what palliative care actually means, and when it can start. Understanding comfort care vs. hospice can also help clarify which path fits your family's situation right now.
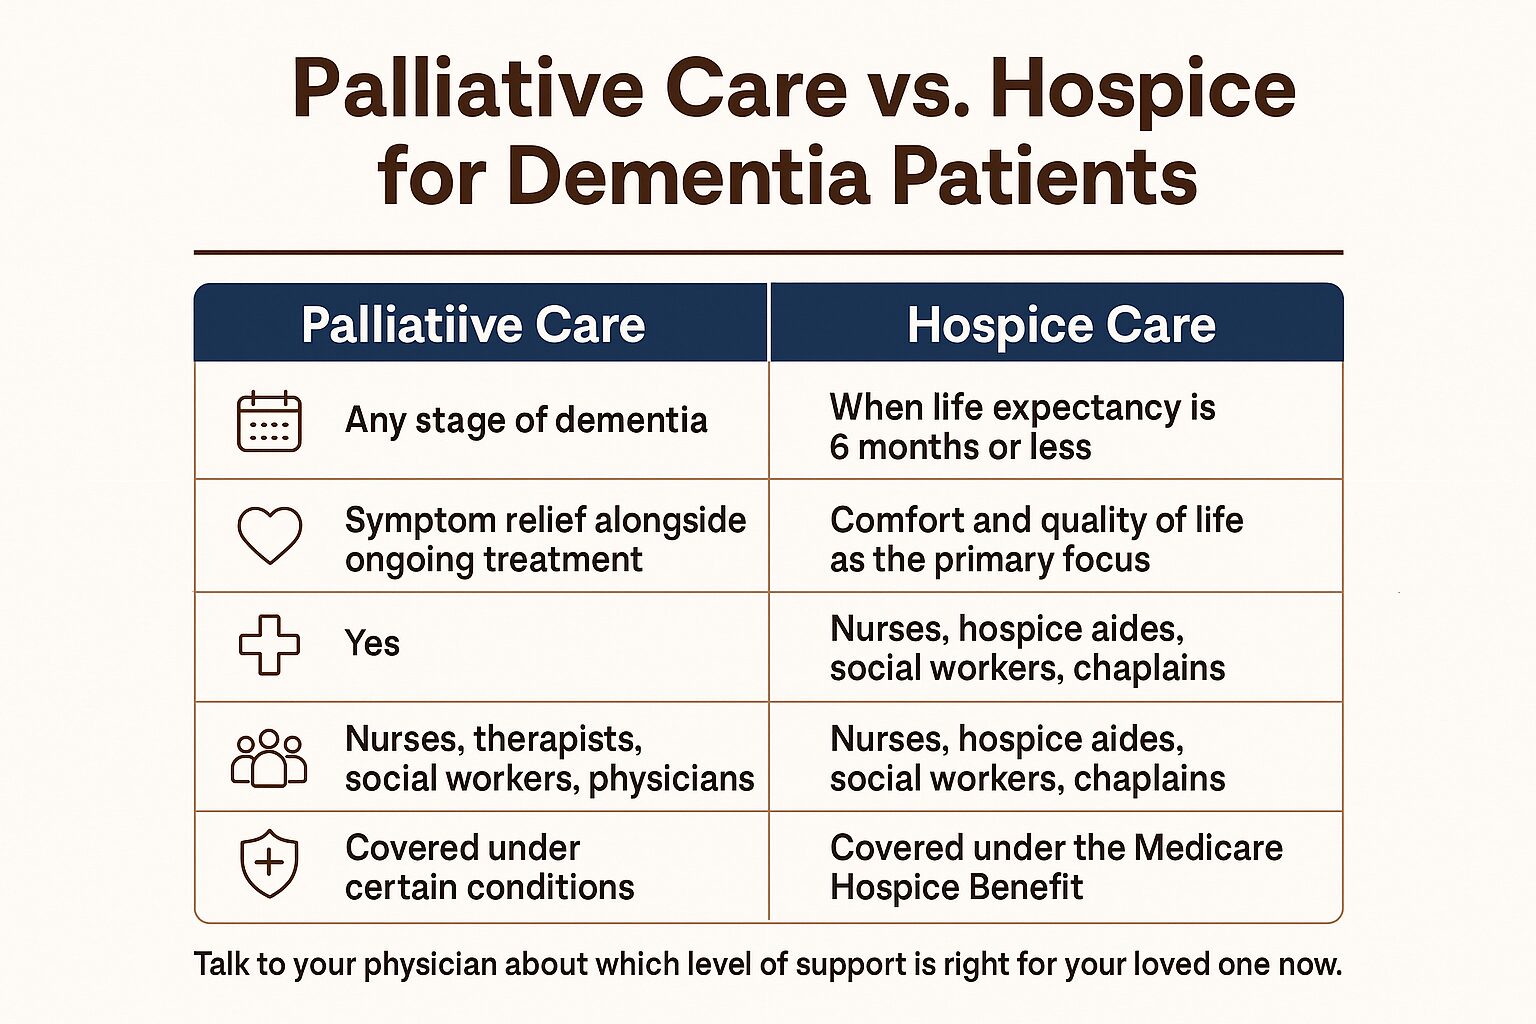
Palliative Care vs. Hospice: A Side-by-Side Look for Dementia Families
This comparison shows the key differences between palliative care and hospice for patients with dementia, so families can identify which level of support fits their current situation.
Dementia Hospice Eligibility: What Physicians Are Looking For
These are the clinical markers physicians commonly use when assessing whether a dementia patient may meet hospice eligibility. No single marker determines eligibility on its own, the physician looks at the full picture.
| Clinical Marker | What It Looks Like in Daily Life | Why It Matters |
|---|---|---|
| Significant weight loss | Losing noticeable weight over several months despite eating attempts | Signals the body is no longer able to maintain itself |
| Recurrent infections | Repeated bouts of pneumonia or urinary tract infections | Indicates the immune system is significantly weakened |
| Loss of mobility | Cannot stand or walk without full physical support from another person | Reflects late-stage neurological decline |
| Loss of verbal communication | Fewer than six intelligible words spoken per day | One recognized clinical threshold for late-stage dementia |
| Unsafe swallowing | Choking, gagging, or refusing food and liquids | Raises aspiration risk and signals end-stage progression |
Does Choosing Hospice Mean Giving Up on My Parent?
This fear is real, and it comes up constantly, in phone calls, in form submissions, in the hesitation families carry into every conversation about this topic. The word "hospice" can feel like a door closing.
But the clinical evidence points in a different direction. Many patients with dementia who transition to hospice stabilize in the early weeks of enrollment. With consistent pain and symptom management, fewer disruptive hospitalizations, and a team visiting regularly at home, some patients become more comfortable and more settled than they had been in months.
Hospice does not accelerate death. What it does is shift the focus from fighting a disease to caring for a whole person. According to research published by the National Hospice and Palliative Care Organization, hospice patients often report better symptom control and family members report less distress than those who do not enroll.
The interdisciplinary team on a hospice program includes nurses, Hospice Aides, a Medical Social Worker, a Chaplain, and Volunteers. That team addresses not just the physical symptoms your parent is experiencing, but the emotional and spiritual weight your entire family is carrying. For families in Monterey County who have been shouldering this alone, that kind of support often arrives as a genuine relief.
If you are still sorting through what to expect, how families describe the moment they chose hospice offers a grounded look at what that decision actually felt like for real families.
Frequently Asked Questions About Hospice and Dementia
Can someone with dementia qualify for hospice if they don't have another terminal diagnosis?
Yes. Dementia alone can meet hospice eligibility criteria when it has progressed to a late stage. Medicare does not require a secondary diagnosis. The physician must certify that the patient's life expectancy is six months or less based on the current trajectory of the disease, and late-stage dementia with the markers described above can meet that standard on its own.
What if my parent seems stable, can they still be evaluated for hospice?
Stability in dementia can be misleading. A person may appear calm or comfortable at home while still meeting hospice eligibility criteria based on weight, swallowing, mobility, or communication. "Stable" does not mean improving. A physician evaluation looks at the full clinical picture, not just how a patient seems on a given day. It is always appropriate to ask for that assessment.
Does Medicare cover hospice for dementia?
Yes. The Medicare Hospice Benefit covers hospice services when a physician certifies a terminal prognosis of six months or less. This includes nursing visits, Hospice Aide services, medication for comfort, medical equipment, and support for the family. Central Coast VNA & Hospice accepts Medicare, Medi-Cal, and Veterans benefits. For a full picture of what is covered and how to access it, a care coordinator can walk you through the specifics for your family's situation.
My parent has dementia and heart failure. Could they qualify sooner than I expect?
Quite possibly. When dementia overlaps with another serious condition, the combined effect on a patient's health often brings eligibility timelines forward. A physician evaluating hospice criteria looks at the whole patient, and two serious illnesses progressing together can meet the eligibility standard more quickly than either would alone. The important step is asking the physician to evaluate where things actually stand right now rather than waiting for an obvious crisis.
What if my parent isn't ready for hospice, is there anything in between?
Palliative care is exactly that. It can begin at any stage of dementia, continues alongside treatment, and focuses on symptom management, care planning, and family support. Central Coast VNA & Hospice has offered a home-based palliative care program in Monterey County since 2015, including Salinas, Hollister, and King City. If you are not sure whether your family is at the hospice threshold but know that more support is needed, what palliative care actually means, and when it can start is a good place to begin.
How do I start the conversation with my parent's doctor about hospice?
You can simply ask: "Has my parent reached the point where a hospice evaluation would make sense?" That is enough. Physicians are accustomed to this question, and a good physician will welcome it rather than dismiss it. If you are not sure how to frame the conversation or what to bring to the appointment, the article on advance care planning offers practical guidance for preparing for exactly this kind of discussion.
Not Sure Where Your Family Stands Right Now?
Families in Monterey County, Salinas, Hollister, King City, and the surrounding communities are welcome to call Central Coast VNA & Hospice at 831-372-6668 to speak with a care coordinator, no referral needed to start that conversation. If you would rather reach out online first, visit ccvna.com to learn more about the hospice and palliative care programs available in your area.

How to Tell If a Hospice Provider Is Actually Trustworthy
When a loved one's health is declining, most families in Monterey County focus on finding someone who can help quickly. What they rarely think to ask is whether the hospice they are considering is legally operating at all.
That is not an abstract concern in California right now. The California Department of Public Health has revoked the licenses of more than 280 hospice providers in the past two years, with roughly 300 more currently under evaluation. Many of those cases involved billing fraud, failure to deliver required services, or inadequate staffing. Families who enrolled without checking their provider's credentials had no idea anything was wrong until care fell apart.
This article focuses on three things that actually matter when evaluating a hospice: how to verify that a provider is licensed and compliant under California's new 2026 regulations, what questions to ask about geographic coverage so you are not left without care at the worst moment, and what real families consistently describe as the signs of a trustworthy team.
California's Hospice Licensing Landscape Changed in June 2026
For decades, hospice oversight in California was thin. The California Hospice Licensure Act of 1990 set a framework, but enforcement was inconsistent and the regulatory gap allowed poorly run agencies to operate with little accountability.
That changed on June 22, 2026, when California enacted its first updated, comprehensive hospice licensing framework through emergency CDPH regulations. The new rules introduced specific requirements that families can now ask about directly:
- Nurse-to-patient ratios, providers must meet defined staffing levels, not just claim adequate coverage
- Management qualifications, agency leadership must meet documented experience requirements
- Unannounced inspections, CDPH can now conduct surprise reviews, not just scheduled ones
- Individualized care planning, each patient must have a documented, specific care plan, not a generic template
The practical meaning for families is that the bar for what a licensed, compliant hospice must provide is now higher and more specific than it has ever been. You can and should ask any prospective provider directly: Are you currently licensed by CDPH, and are you in full compliance with the June 2026 emergency regulations?
A trustworthy provider will answer that question directly. One that hedges or changes the subject is worth a second look.
For broader context on how CMS oversees hospice quality and what transparency tools are being developed, the CMS Hospice Center is worth bookmarking. CMS is actively developing a public scoring tool to flag providers with concerning utilization patterns, and new telehealth restrictions now apply to any hospice operating under enhanced oversight.

The Geographic Question Families Forget to Ask
Monterey County is large. Salinas, King City, Hollister, and Pacific Grove are all in the service area of some providers but not others. And there is a real source of confusion specific to this region: Central Coast VNA & Hospice, based in Monterey, is sometimes mistaken for other organizations with similar names serving areas like Santa Cruz.
Callers to VNA's intake line regularly ask whether the organization serves their specific neighborhood. Some have already started the enrollment conversation before discovering the provider they called does not actually cover their address. That kind of mix-up, when it happens during a health crisis, can leave a family without care at exactly the wrong moment.
Before a loved one is admitted to any hospice program, ask these questions and get specific answers:
- Does this agency serve [your exact city or zip code]? Not the county in general, your neighborhood.
- Do you have nurses and other clinicians already working in this area, or would my loved one require a long travel window for every visit?
- If I am in Hollister or King City, does your coverage there match what you offer in Monterey?
- Are you the same organization as [any similar-sounding agency], or are you independent?
If a provider cannot answer those questions cleanly and specifically, that is information worth having before you sign anything.
If you are unsure whether hospice is even the right fit right now, this overview of how families describe the moment they chose hospice may help you think through where your family actually stands.
Five Questions to Ask Any Hospice Provider Before Enrollment
These five questions give families a practical checklist for evaluating a hospice before agreeing to any admission.

How to Read the Public Record on Any Hospice
Most families do not realize there is a public paper trail on every Medicare-certified hospice in the country. You do not have to take a provider's word for how well they operate.
Here is what you can ask about or look up directly:
- CMS Star ratings, the Centers for Medicare and Medicaid Services publishes ratings on Medicare.gov for hospice providers. Ask any provider you are considering for their current Star rating.
- HHCAHPS patient satisfaction scores, these are standardized surveys completed by families after a hospice stay. A provider's score reflects how real patients and families rated their communication, responsiveness, and emotional support.
- CDPH survey history, you can ask a hospice directly whether they have had any unannounced inspections, deficiency citations, or enforcement actions in the past two years. Under the new June 2026 regulations, that history is more relevant than ever.
- License verification, CDPH maintains a database of licensed hospice agencies. A quick check can confirm whether the agency you are speaking with is currently in good standing.
CMS is also developing a public icon system for its Medicare.gov comparison tool that will flag hospices that have not submitted required quality data. Until that feature is live, ask providers directly for their submission history.
A nonprofit organization with 75 years of continuous service in a community, a public track record, and a verified license is a materially different thing from a recently licensed agency with no local history and no public data trail. That difference is worth understanding before you commit to a provider.
For more background on what the hospice benefit actually covers and when it applies, this explanation of hospice eligibility questions families are afraid to ask is a useful starting point.
What Trustworthy Hospice Providers Can Show You
A compliant, accountable hospice should be able to answer or provide documentation for each of the items below. This is not an exhaustive legal checklist, but a practical starting point for families evaluating a provider.
| What to Ask For | What It Tells You | Red Flag If... |
|---|---|---|
| Current CDPH license number | The agency is legally authorized to operate in California | They cannot provide a number or deflect the question |
| CMS Star rating on Medicare.gov | How their quality compares to other hospices nationally | They have no published rating or refuse to share it |
| HHCAHPS patient satisfaction score | How families rate their communication and responsiveness | Scores are unavailable or the provider is unaware of the metric |
| Recent CDPH survey/inspection history | Whether they have had deficiencies or enforcement actions | They have had actions in the past 24 months they cannot explain |
| Specific coverage confirmation for your address | That they actually serve your loved one's neighborhood | They confirm 'Monterey County' without specifying your area |
| Named care team roles | That a full team, including chaplains and social workers, is in place | They describe a team vaguely or cannot name specific roles |
What Real Families Say Makes a Hospice Team Worth Trusting
Marketing materials from hospice agencies tend to emphasize the same things: experience, compassion, and 24/7 availability. Those claims are worth little without a way to evaluate them.
What real families consistently describe as meaningful is different from what brochures emphasize. One reviewer described a team that explained what was happening and why, translated the parts that did not make sense, and made the path forward feel possible. Another noted staff who seem to truly care about helping others, not just showing up to complete tasks.
The pattern across real feedback is consistent. Families remember:
- Whether nurses showed up consistently and communicated proactively, not just when called
- Whether the Medical Social Worker actually helped navigate decisions rather than just handing over a pamphlet
- Whether Chaplains and Volunteers were present and genuine, not perfunctory
- Whether the team spoke clearly about what was happening medically, without hiding behind clinical language
Scheduling inconsistency is also a real concern families raise. When visits happen at unpredictable times, or when patients do not know who is coming or when, the anxiety that creates is significant. A reliable hospice team should be able to tell you, before enrollment, how visit windows are communicated and what happens when a scheduled clinician cannot make a visit.
If you are still working through whether your loved one's situation calls for hospice or something earlier, this piece on comfort-focused care and when to ask about it may help clarify the options. And for families earlier in the process, understanding what palliative care actually means is often the right first conversation to have.
Frequently Asked Questions About Choosing a Hospice Provider in California
How do I verify that a hospice is currently licensed in California?
You can ask the provider directly for their CDPH license number and then verify it through the California Department of Public Health's licensing database. Under the new June 2026 regulations, licensed hospices must meet specific staffing, planning, and inspection requirements. If a provider cannot give you a license number or hesitates to confirm their compliance status, that is worth taking seriously.
What is a CMS Star rating and where do I find it?
The Centers for Medicare and Medicaid Services assigns Star ratings to hospice providers based on quality measures and patient satisfaction surveys. You can look up ratings at Medicare.gov. You can also ask any provider you are considering to tell you their current rating directly. A provider that does not know their rating or cannot share their HHCAHPS patient satisfaction scores is missing a basic level of transparency.
Does Medicare cover hospice at home?
Yes. Medicare Part A covers hospice services for patients who meet eligibility requirements, which generally means a physician has certified a prognosis of six months or less if the illness follows its expected course. Medi-Cal and Veterans benefits also cover hospice in most cases. There is typically no out-of-pocket cost for covered hospice services under Medicare. For more detail on what the eligibility question actually involves, this article on hospice eligibility walks through it plainly.
What should I do if I'm not sure whether a hospice covers my area in Monterey County?
Ask directly and ask specifically. Give the provider your city, zip code, or neighborhood and ask whether they have clinicians currently serving that area. There is real confusion in this region between organizations with similar names, and assuming coverage by county rather than confirming by location has left some families without care. If you are in Salinas, Hollister, King City, or a smaller community in the area, get a specific yes before moving forward.
Is a nonprofit hospice meaningfully different from a for-profit one?
The organizational structure does matter in practice. A nonprofit hospice reinvests any surplus back into services and community programs rather than returning it to shareholders. That does not automatically make every nonprofit better than every for-profit, but it does mean the incentive structure is different. When combined with a long track record, public accountability, and a verifiable history in the community, nonprofit status is one reasonable factor to weigh.
Can I switch hospice providers if I am unhappy with the care being given?
Yes. Under Medicare, patients have the right to change hospice providers. You can discharge from one hospice and re-enroll with another. The process involves paperwork and a transition period, so it is not seamless, but it is possible. If care is falling short of what was promised or what the new CDPH regulations require, you do not have to stay. Document your concerns and speak with a Medical Social Worker or patient advocate if you need help navigating the transition.
Questions About Hospice Care in Monterey County?
Central Coast VNA & Hospice has been serving families across Monterey County, San Benito County, and surrounding communities since 1951. If you want to talk through what questions to ask, confirm whether your loved one's address falls within the service area, or simply understand what the process looks like, a care coordinator is available to help without pressure. You can reach the team at 831-372-6668 or visit ccvna.com to learn more.

Advance Care Planning Is Not Just Paperwork. Here Is What It Actually Does.
Most families in Monterey County think they have handled advance care planning the moment someone signs an advance directive. The form gets filed away, and the subject gets dropped. Then a health crisis arrives, and no one in the room, including the person holding the form, actually knows what the patient would want.
The document was never the hard part. The conversation was.
Advance care planning as a real process means something much deeper than filling out paperwork. It means that a patient and the people they trust have actually talked through what kind of life is worth sustaining, what they fear most about serious illness, and who they want making decisions if they cannot speak for themselves. This article is about that process, and about who can help families get through it before a crisis makes it impossible.
The Difference Between a Signed Form and a Real Plan
An advance directive tells medical staff what interventions a patient does or does not want in a medical emergency. That matters. But a form that no one has talked through is a document no one fully understands.
Consider what happens in practice. A patient arrives at Community Hospital of the Monterey Peninsula after a stroke. The family is asked whether their loved one would want aggressive intervention. There is a signed advance directive somewhere, but the adult children remember the conversation differently, or there was no real conversation at all. The form says something, but no one can explain the reasoning behind it.
Advance care planning as a process changes that. It means the patient has answered harder questions with the people who will carry those answers:
- What does a good day look like to me, and would I still value life if that changed significantly?
- Who do I trust to make decisions when I cannot?
- What do I fear most, pain, loss of independence, being a burden, something else?
- Are there conditions under which I would want care to focus on comfort rather than treatment?
When those conversations have happened, the signed form becomes a reflection of real choices. Without them, it is just a document. As one reviewer of an existing article on this topic put it, the guidance was clear but they wished someone had explained what to do with the form after signing it. That gap, between documentation and understanding, is what advance care planning is designed to close.
For families navigating serious illness, what palliative care actually means and when it can start is worth reading alongside this, because palliative care teams are often the first to open these conversations with patients at home.

Who Should Be Part of the Conversation, and When
The research on this is consistent: most families start end-of-life planning too late, often not until a crisis has already forced the decision. The ideal time for advance care planning is when no immediate decision is required, which means now, for most families reading this.
But the "who" matters just as much as the "when."
The obvious participants are the patient and the people they designate as decision-makers. But one role that often gets overlooked is the Medical Social Worker on a home health or palliative care team. Medical Social Workers are trained specifically to help patients and families do three things that are genuinely difficult:
- Articulate what matters most in plain language, even when the feelings are complicated
- Work through disagreements between family members who see things differently
- Translate those conversations into documentation that travels with the patient through every care setting
For patients already receiving home health care in Salinas, King City, Pacific Grove, or Hollister, this kind of conversation does not require a separate appointment or a formal meeting. A Medical Social Worker visiting a patient at home can open and guide these discussions in a living room, with the people who know the patient's history. That context changes the conversation considerably compared to a clipboard in a doctor's office.
The care team involved in these conversations typically includes Registered Nurses, Nurse Practitioners, Medical Social Workers, and depending on the patient's situation, Chaplains and other clinicians who know the patient's full picture. Advance care planning is not a one-time event. It is a conversation that may happen more than once as a person's health changes, and having a consistent care team at home means someone is always there to revisit it.
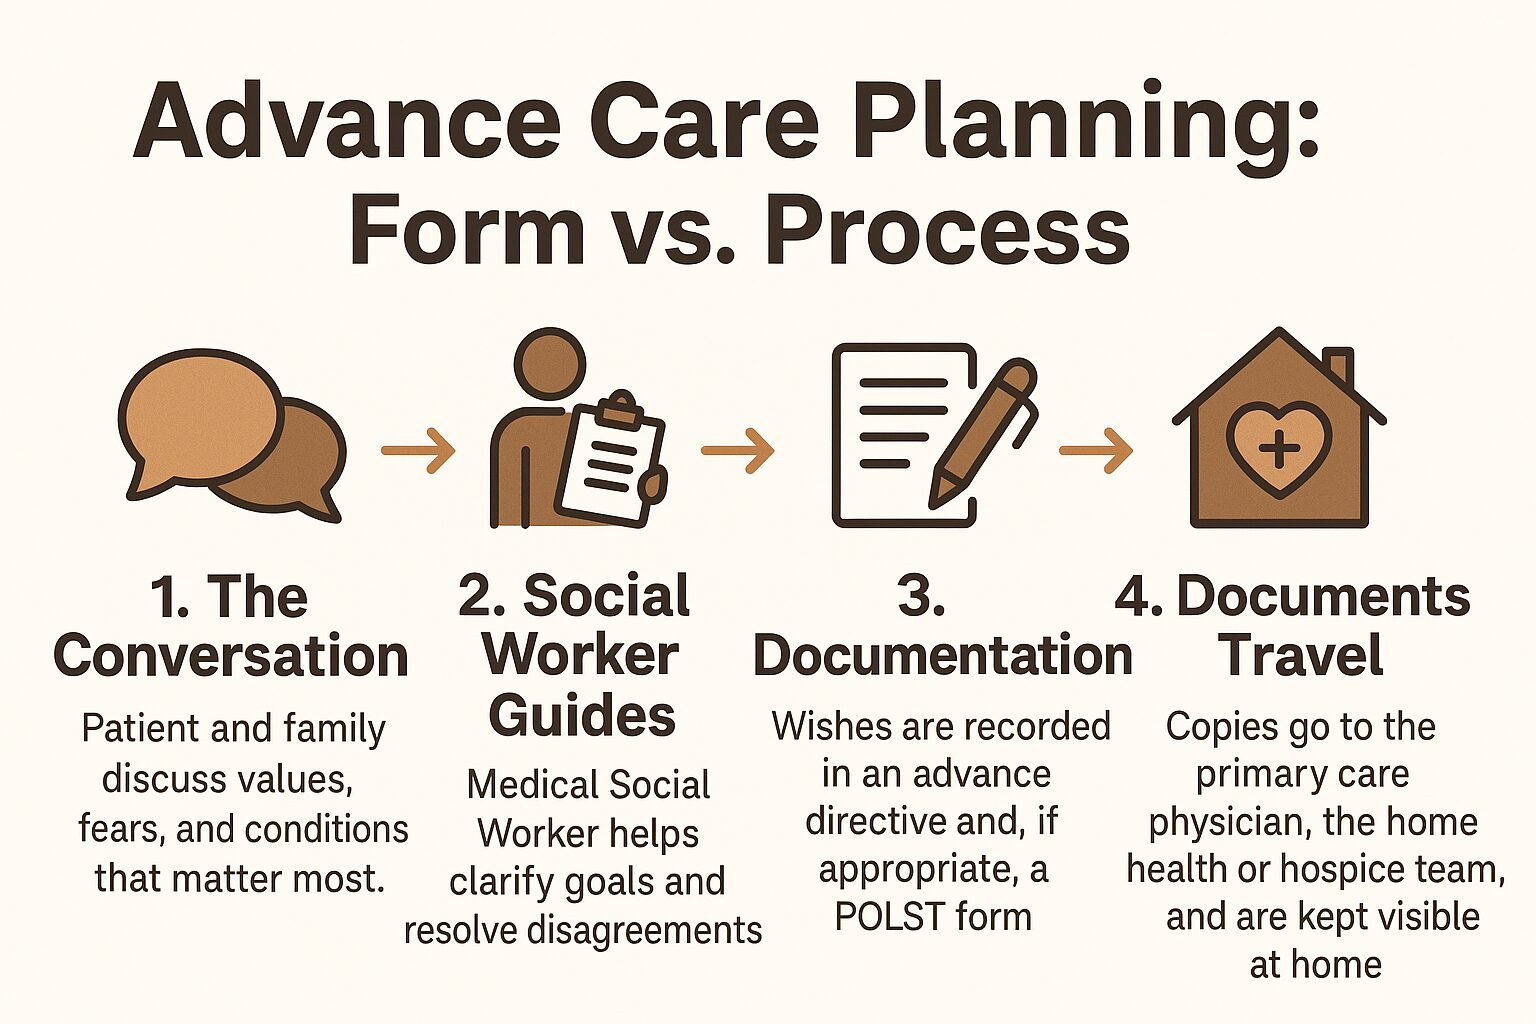
Advance Care Planning: The Process at a Glance
This overview shows the difference between signing a directive and completing the full planning process, including who is involved and what each step produces.
Where the Documents Need to Go After You Sign Them
This is the practical piece that a reader of VNA's earlier advance directives article specifically raised, and it deserves a direct answer.
An advance directive or POLST form (Physician Orders for Life-Sustaining Treatment) is only useful if the right people can find the most current version at the right moment. In Monterey County, POLST forms carry specific medical orders and are designed to travel with a patient between care settings, including Salinas Valley Health, Community Hospital of the Monterey Peninsula, and home. But that only works if the form exists, is current, and is accessible.
Here is where copies should go:
- Primary care physician, the form should be in the patient's medical record
- Specialists, if the patient sees any regularly
- Home health or hospice team, clinicians visiting at home need to know what the patient's documented wishes are
- A visible location at home, the refrigerator door is standard guidance for a reason: first responders in Monterey County are trained to look there
One detail families often miss: if an advance directive is updated, the old version should be destroyed or clearly marked as superseded. A care team acting on an outdated document is not acting on the patient's actual wishes.
The California Attorney General's office provides standardized advance directive forms that meet state legal requirements, which is a useful starting point for families who want to make sure the paperwork is valid before the conversations begin.
For families sorting out what all of this means alongside a home health transition, what families often miss when planning a hospital discharge to home covers related ground that is worth reading together with this.
Advance Directive vs. POLST: What Each One Does
These two documents serve different purposes and are not interchangeable. Understanding which one applies in a given situation helps families make sure the right document is in the right hands.
| Document | What It Does | Who Acts on It |
|---|---|---|
| Advance Directive | Records a patient's general values and wishes about future medical care, including who makes decisions | Physicians, hospitals, and care facilities when the patient cannot speak for themselves |
| POLST Form | Carries specific, immediately actionable medical orders (e.g., DNR, hospitalization preferences) | First responders, emergency staff, home health and hospice clinicians in any care setting |
| Healthcare Power of Attorney | Legally designates a specific person to make medical decisions on the patient's behalf | Any medical provider when the patient lacks decision-making capacity |
When Palliative Care and Home Health Teams Are Already Involved
Families sometimes assume advance care planning requires scheduling a special meeting or hiring an attorney. For patients already receiving home-based care, that assumption is worth setting aside.
Registered Nurses, Nurse Practitioners, and Medical Social Workers who visit patients at home in Monterey County, Salinas, King City, and Hollister regularly engage in these conversations as part of ongoing care. A nurse assessing a patient's pain management may naturally open the question of what the patient's goals for treatment are. A Medical Social Worker helping a family coordinate care may be the first person to ask who the patient wants making decisions if they cannot.
These are not bureaucratic checkboxes. They are conversations that happen because the care team has built enough of a relationship with the patient to have them. That relationship is part of what makes home-based care different from a clinic visit. For families thinking about what that kind of support looks like in practice, what a skilled nurse actually does on a home visit gives a realistic picture.
If a family member is dealing with a serious or progressive illness and has not yet had any of these conversations, how do you know when it is time to consider hospice care is another place to start, particularly if the question of comfort-focused care is beginning to feel more pressing.
Frequently Asked Questions About Advance Care Planning
Does my loved one need an attorney to complete an advance directive in California?
No. California law allows advance directives to be signed without an attorney as long as the document is witnessed by two people who are not the patient's healthcare providers or heirs. Some families do choose to have a document notarized for extra certainty, but it is not required. The California Attorney General's office provides a free standardized form.
What if family members disagree about what the patient would want?
This is one of the most common and most painful situations families face. A Medical Social Worker on a home health or palliative care team is specifically trained to help families work through these disagreements, not by deciding for them, but by helping everyone articulate what they understand and what they fear. Getting those conversations on the table before a crisis is far less painful than having them in a hospital hallway.
How is a POLST different from a Do Not Resuscitate (DNR) order?
A DNR is one specific order within a POLST, which covers a broader set of decisions including hospitalization preferences, artificial nutrition, and other interventions. A POLST form is a physician-signed medical order that travels with the patient and can be acted on immediately by first responders. A DNR alone may not address what happens in other situations where intervention is possible but not desired.
Can an advance directive be changed after it is signed?
Yes, and it should be updated whenever a patient's health situation, values, or wishes change significantly. The most important step after updating is making sure old versions are replaced in every location where the document was previously distributed, including the patient's physician, any specialist offices, and the home health or hospice team.
At what age or health stage should someone start advance care planning?
There is no minimum age or health condition that makes it appropriate. Most planning guides recommend starting these conversations well before any diagnosis, while the person has full capacity to articulate what matters to them. For people already managing a serious or chronic illness, the conversation becomes more urgent, but it is rarely too late to have it meaningfully.
Ready to Start This Conversation With Someone Who Knows Your Family's Situation?
For patients already receiving home health or palliative care in Monterey County, these conversations do not have to happen in a waiting room or a formal meeting. Central Coast VNA & Hospice has been supporting families across the Central Coast since 1951, and the nurses, Medical Social Workers, and other clinicians on its home-based teams are available to help patients and families think through what advance care planning actually looks like for their situation. You can reach VNA at 831-372-6668 or visit ccvna.com to connect with a care coordinator.

What Palliative Care Actually Means, and When It Can Start
On a Tuesday afternoon, palliative care might look like a Registered Nurse reviewing a pain management plan at a kitchen table in Salinas. It might look like a Medical Social Worker helping a family figure out why their father keeps ending up in the emergency room. It might look like a simple phone call that finally gives a spouse the words she needs to describe what her husband is going through to his oncologist. That is the palliative care meaning that matters, not the policy definition, but what it actually does for a person on an ordinary day.
Most families on the Central Coast first hear the phrase during a hospital stay or a difficult appointment. And most of them assume it means something is ending. It usually doesn't. Palliative care can begin the day a serious illness is diagnosed, whether that's Parkinson's disease, heart failure, COPD, or cancer, and it can continue for months or years while a patient is still pursuing treatment.
This article explains what palliative care actually is, who it's for, what the team looks like in a home-based setting, and how families in Monterey County can ask for it without waiting until things get worse.
What Palliative Care Means, in Plain Language
Palliative care is specialized medical support focused on relieving the symptoms and stress caused by serious illness. The goal is not to treat the underlying disease, that's the job of the patient's primary physicians, but to make the experience of living with that disease more manageable.
Symptoms that palliative care commonly addresses include:
- Pain that isn't well controlled by a primary care plan
- Shortness of breath, especially common in heart failure and COPD
- Fatigue and sleep disruption that leave patients exhausted and families worn down
- Anxiety and depression that develop alongside serious illness
- Nausea, appetite loss, and medication side effects
- Confusion about care options and what decisions need to be made
That last one matters more than people expect. A significant part of palliative care is helping patients and families understand what is happening, what choices exist, and how to communicate those choices to the broader care team. One family described calling their loved one's physician's office and not knowing which questions to even ask, a palliative care team addresses exactly that gap.
For families wondering about coverage, what Medicare covering palliative care could mean for your family is worth reading before you assume cost is a barrier.

Is Palliative Care the Same as Hospice?
This question comes up in nearly every family conversation about serious illness, and the confusion is completely understandable.
Palliative care is the broader category. Hospice is one specific type of palliative care. Here is the clearest way to think about it:
- Palliative care can begin at any stage of illness, runs alongside curative treatment, and has no required prognosis. A patient can receive palliative care for two years while actively treating cancer.
- Hospice care is for patients who have decided to stop pursuing curative treatment and whose physician estimates a prognosis of six months or less if the illness runs its natural course.
Someone on palliative care is not giving up. They are getting help managing symptoms so they can tolerate treatment, stay out of the emergency room, and keep living at home. That distinction changes everything about how families receive the idea.
If you are already weighing where hospice fits into the picture, how do you know when it's time to consider hospice care covers that question with the same directness.
The National Institute on Aging also describes the distinction clearly and is worth bookmarking for family conversations.
Palliative Care vs. Hospice: Side by Side
This table shows the practical differences between palliative care and hospice, two terms that are often used interchangeably but mean very different things.
| Palliative Care | Hospice Care | |
|---|---|---|
| When it starts | At diagnosis, any stage of illness | When curative treatment has stopped |
| Prognosis required? | No | Yes, 6 months or less |
| Can patient still pursue treatment? | Yes | No, hospice is comfort-focused only |
| Focus | Symptom relief and care planning alongside treatment | Comfort, dignity, and quality of life at end of life |
| How long it lasts | Months to years | Up to 6 months (renewable if eligible) |
| Medicare coverage | Varies by plan and setting | Covered under Medicare Hospice Benefit |
Why Starting Earlier Almost Always Helps
Most families wait too long. The pattern is familiar to anyone who has worked with seriously ill patients on the Central Coast, a spouse managing a husband's Parkinson's progression alone, an adult child flying in from out of state to handle a parent's heart failure crisis, a family member in Pacific Grove who didn't know palliative care was even an option until the third ER visit in two months.
Earlier palliative care involvement is tied to fewer ER visits, better sleep, reduced anxiety, and longer time at home. Those outcomes are not accidental. When a palliative team is involved early, medication plans are adjusted before symptoms spiral. Emotional support is in place before families hit a wall. Care decisions get made with time to think, not in a hospital hallway at midnight.
For families managing chronic, progressive illnesses like COPD, advanced heart failure, or neurodegenerative conditions, the question is rarely "is it time for palliative care?", it's "why haven't we started yet?"
If you're navigating whether your situation calls for this kind of support, when caring for an aging parent becomes more than you can do alone describes the signs families often recognize too late.
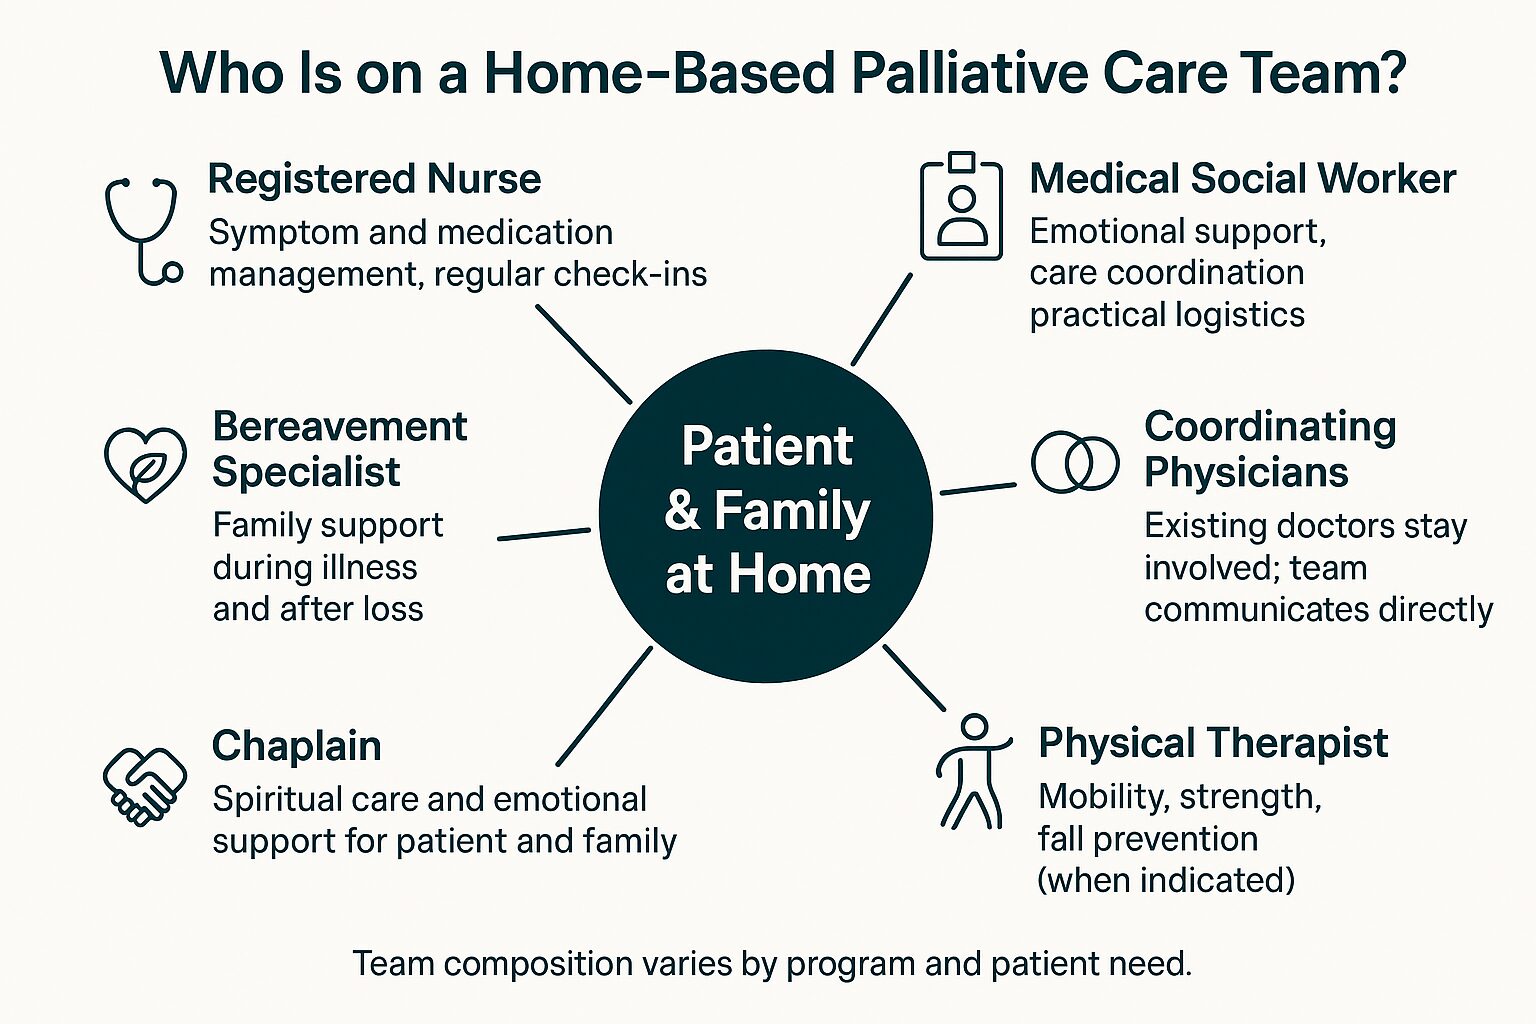
What the Palliative Care Team Actually Looks Like
Home-based palliative care involves more than one nurse checking in. This shows who is on the team and what each person does.
How to Ask Your Doctor for a Palliative Care Referral
One of the most common things families say after getting connected to palliative care is that they didn't know they could ask for it. Many assume a specialist has to bring it up first.
Any patient with a serious illness can ask their primary care physician or specialist for a palliative care referral. You don't need to be near the end of life. You don't need to have stopped treatment. You just need to be dealing with a serious illness that is affecting quality of life.
A straightforward way to start the conversation with a physician:
- "My [husband/mother/father] is having a hard time managing [pain/fatigue/shortness of breath] alongside treatment. Is a palliative care referral something we should consider?"
- "We're feeling overwhelmed trying to coordinate all of this at home. Is there a palliative care team that could help us with care planning?"
- "I've heard palliative care can help people stay out of the ER. Would that be appropriate given where we are?"
After a referral is placed, the process typically involves an initial home visit to assess the patient's symptoms, medications, and overall situation. From there, the team develops a plan and begins coordinating with existing physicians. In a home-based program, the team comes to the patient, whether that's a home in King City, an apartment in Salinas, or a residence in Pacific Grove. That matters a great deal for older adults who find clinic visits exhausting or physically difficult.
For those who aren't sure whether their situation calls for palliative care or something closer to home health, skilled nursing care at home is different from what most people picture explains that distinction clearly.
Frequently Asked Questions About Palliative Care
Does palliative care mean my loved one is dying?
No. Palliative care can start at any stage of a serious illness, including shortly after diagnosis, and it runs alongside curative treatment. Many patients receive palliative care for a year or more while still actively treating their illness. It is focused on quality of life, managing symptoms, reducing stress, and supporting the whole family, not on end-of-life preparation.
Who pays for palliative care at home?
Coverage depends on the setting and your specific plan. Medicare, Medi-Cal, and Veterans benefits may cover various components of home-based palliative care, though the rules differ from hospice coverage. A care coordinator can walk through what applies to your situation before any services begin. Central Coast VNA & Hospice accepts Medicare, Medi-Cal, and Veterans benefits.
Can my loved one receive palliative care and still see their regular doctors?
Yes, and that's actually the point. Palliative care is designed to coordinate with, not replace, the patient's existing care team. Registered Nurses and Medical Social Workers communicate directly with the treating physicians so the whole picture stays connected.
How do I know if palliative care is the right fit right now versus hospice?
If your loved one is still pursuing curative or disease-managing treatment, palliative care is almost certainly the right conversation to start. Hospice applies when curative treatment has stopped and a physician estimates six months or less. The table above in this article breaks down the practical differences, and comfort care vs. hospice: why the difference matters goes deeper on where the lines are.
What if I'm not sure my loved one qualifies or where to start?
That uncertainty is exactly where a care coordinator can help. Many families call not knowing whether they qualify, what a physician referral requires, or whether their area is covered. A single phone call can answer those questions without any commitment. Central Coast VNA & Hospice serves all of Monterey County, including Salinas, King City, the Monterey Peninsula, and surrounding communities, as well as parts of San Benito and South Santa Clara counties.
Ready to Talk Through Whether Palliative Care Fits Your Situation?
If you are managing a serious illness, yours or a loved one's, and you're not sure whether palliative care is an option yet, a conversation with a care coordinator is the simplest first step. Central Coast VNA & Hospice has served families across Monterey County, Salinas, King City, the Monterey Peninsula, and surrounding communities since 1951, and that kind of local experience makes a real difference when you're trying to understand what is available and where to start. You can reach their team at 831-372-6668 or learn more at ccvna.com.

Comfort Care vs. Hospice: Why the Difference Matters
If you've heard a doctor use the phrase comfort care and walked away unsure what it actually meant, you're not alone. Families across Monterey County hear this term during hospitalizations, in physician offices, and from discharge planners, and almost no one uses it the same way. Some clinicians mean palliative support alongside active treatment. Others use it to signal a shift toward end-of-life focus. A few use it interchangeably with hospice. The term itself is genuinely inconsistent across hospitals, insurers, and physicians, and the confusion that follows is completely understandable.
What matters is that the phrase almost always carries more weight than people realize in the moment. When a doctor brings up comfort care, it usually means something specific is being proposed, and the family deserves to know exactly what that is. This article breaks down what comfort care actually means in a clinical context, how it differs from hospice, and what questions will help any family in Monterey, Salinas, or the surrounding Central Coast communities understand what's being offered before they agree to anything.
What 'Comfort Care' Actually Means When a Doctor Says It
In most clinical settings, when a physician or hospital team uses the phrase comfort care, they are signaling a shift in treatment goals, from curing or controlling a disease to managing how a patient feels day to day. That means focusing on pain, breathlessness, anxiety, nausea, and other symptoms that reduce quality of life.
But here is what many families miss: that shift in goals does not automatically mean treatment is ending. Comfort-focused care can run alongside active medical treatment. A patient receiving chemotherapy, for example, can also receive symptom management support for the side effects of that treatment. These are not mutually exclusive approaches.
When you hear a physician propose comfort care, the most important thing you can do is ask a few direct questions:
- Is this being offered alongside my loved one's current treatment, or instead of it?
- What specific symptoms are you hoping to address?
- Does this change any of the medications or therapies already in place?
- Are you recommending a referral to a palliative care team or to hospice?
Those four questions will tell you almost everything you need to know about what is actually being proposed. Families who understand this early tend to accept appropriate support sooner, and that timing genuinely affects how much relief their loved one receives.
For a broader look at what comfort-focused care looks like in practice, What "Comfort-Focused Care" Really Means, and When to Ask About It is worth reading before or after any conversation with a physician.

Hospice Is a Specific Program, Not Just a Philosophy
Hospice is not a vague idea or a general approach to care. It is a structured, medically defined program with specific eligibility requirements, a dedicated team, and its own coverage under Medicare and Medi-Cal.
To qualify for hospice, a physician must certify that a patient's life-limiting illness may result in death within six months if the illness follows its expected course. That is the threshold. It does not mean a patient will die in six months, some patients on hospice live longer and are discharged. But that medical determination is required before the program can begin.
Once enrolled, hospice brings an interdisciplinary team into the home that most families did not know existed. That team typically includes:
- Registered Nurses who assess symptoms, manage medications, and are available around the clock
- Hospice Aides who help with personal care and daily routines
- Medical Social Workers who address practical needs, family stress, and care coordination
- Chaplains who offer spiritual support to patients and families of any faith background or none
- Bereavement Specialists who continue supporting the family after the patient passes
- Volunteers who provide companionship and give family members a break
Medicare covers hospice as a distinct benefit, including medications related to the terminal diagnosis, equipment like a hospital bed or wheelchair, and all of the team visits described above. Medi-Cal and Veterans benefits also cover hospice, though the specifics vary. If you want to understand how that eligibility question actually works in practice, The Hospice Eligibility Question Most Families Are Afraid to Ask addresses it directly.
Comfort care, by contrast, has no formal eligibility threshold. A patient at any stage of illness can receive comfort-focused symptom support. That is one of the most important distinctions families need to hear: you do not have to qualify for hospice to get meaningful relief.
Comfort Care vs. Hospice: A Side-by-Side Look
These are the practical differences families most often need to understand when weighing their options.
| Feature | Comfort Care (General) | Hospice Program |
|---|---|---|
| Eligibility requirement | None, available at any illness stage | Physician certifies 6-month prognosis |
| Can continue curative treatment? | Yes | Generally no, goals shift to comfort only |
| Medicare/Medi-Cal benefit | Covered based on diagnosis and how services are ordered | Distinct Medicare Hospice Benefit with defined coverage |
| Team involved | Varies, may include nurses, therapists, social workers | Full interdisciplinary team: nurses, aides, social workers, chaplains, volunteers, bereavement specialists |
| Where care is provided | Home, clinic, or hospital setting | Primarily in the home or a homelike setting |
| Duration | As long as clinically appropriate | Recertified in 90-day periods; no set end date |
The Team Behind Comfort-Focused Care
Most families are surprised by how many clinicians can be involved before a hospice decision is ever made. This shows who is typically part of a comfort-focused care team.

Why Families Hear 'Comfort Care' and Think It Means Giving Up
This is one of the most consistent patterns in conversations with families navigating a serious illness. Someone hears a physician recommend comfort care during a hospitalization and interprets it as the medical team stepping back, as giving up on their loved one.
That interpretation is understandable. And it is also often wrong.
Focusing on comfort does not require stopping other care. In many cases, physicians recommend a palliative layer of support specifically because a patient is in active treatment and the treatment itself is causing significant suffering. Adding symptom management in that context is not a retreat. It is an expansion of care.
The phrase that tends to create the most confusion is when comfort care is offered as a goal-of-care conversation, a discussion about what matters most to the patient as a person, not just as a medical case. Those conversations can feel heavy, and physicians do not always frame them in a way that feels reassuring. But families who engage with those conversations openly tend to find that their loved one's wishes become clearer, and that the care that follows is more aligned with those wishes.
If your family is in the middle of that conversation right now, How Families Describe the Moment They Chose Hospice offers real perspective from people who have been through it, and may help the decision feel less isolating.
For families in Salinas, King City, Hollister, or the Monterey Peninsula who are trying to figure out what comes next after a hospitalization, What Families Often Miss When Planning a Hospital Discharge to Home is also worth a read before discharge day arrives.
How Coverage Works, and Why It Should Not Stop You from Asking
One question that comes up constantly, from families in Pacific Grove to patients in King City, is whether Medicare or Medi-Cal will pay for comfort-focused care. The short answer is: it depends on how the services are ordered and what the underlying diagnosis is.
Medicare's Hospice Benefit is one of the most clearly defined coverages in all of Medicare. Once a patient is enrolled in a certified hospice program, Medicare covers the team visits, medications related to the terminal diagnosis, and equipment delivered to the home, with little to no cost to the patient.
Palliative and comfort-focused care outside of hospice is covered differently. Skilled nursing visits, physical therapy, and other home health services are generally covered under Medicare Part A or Part B when a physician orders them and the patient meets homebound criteria. The Medicare website has a useful breakdown of what home health services Medicare covers and the conditions that apply.
The most practical step any family can take is to ask two questions of their physician and their care team:
- How will these services be billed, and under what part of my coverage?
- Is there anything I need to do to make sure the referral is in place before care begins?
Coverage should never be the reason a family waits to ask for help. If there is uncertainty, a care coordinator can help clarify what applies to a specific situation before anything is scheduled. For more on how Medicare coverage intersects with palliative care specifically, What Medicare Covering Palliative Care Could Mean for Your Family explains the landscape in plain language.
Frequently Asked Questions About Comfort Care and Hospice
Can my loved one receive comfort care and still try to get better?
Yes. Comfort care and curative treatment can run at the same time. Focusing on symptoms like pain or breathlessness does not require stopping chemotherapy, dialysis, or other active treatment. The two goals can coexist, and in many cases, managing symptoms actually helps a patient tolerate treatment better.
How is hospice different from just having a nurse come to the house?
Home nursing visits and hospice are very different programs. A skilled nursing visit through home health focuses on a specific clinical task, wound care, medication management, post-surgical recovery. Hospice brings a full team into the home on an ongoing basis: Registered Nurses, Hospice Aides, Medical Social Workers, Chaplains, and Volunteers, all coordinated around one goal, which is quality of life for the patient and support for the family. It is a much broader program than a single nursing visit.
Does choosing hospice mean we're giving up?
Most families who have been through it say the opposite. Hospice shifts the focus from fighting the illness to focusing on the person, their comfort, their dignity, and their wishes. Families often describe feeling that hospice gave their loved one more presence, more peace, and more control over their final months than continued aggressive treatment would have. That is not giving up. It is a different kind of commitment.
What if my parent isn't ready for hospice but is still struggling with symptoms?
This is exactly the situation where palliative and comfort-focused care is most valuable. There is no eligibility threshold for comfort-focused symptom support. A patient does not have to be near the end of life to benefit from a Medical Social Worker helping with stress, or a Registered Nurse managing pain more effectively. If your loved one is suffering and you are not sure whether hospice is the right step, asking about palliative care first is a completely reasonable path.
Does a physician referral have to come first?
For most home health and hospice services, yes, a physician order is required to get started. Many families don't realize this until they call, which can create frustrating delays. If you know care is coming, the fastest thing you can do is contact the physician's office and ask them to send a referral directly to the home health or hospice agency. A care coordinator can walk you through that process and often help facilitate the paperwork.
What happens to the family after a hospice patient passes away?
Hospice care does not end at the moment of death. Bereavement support, including grief counseling and ongoing check-ins from Bereavement Specialists, continues for the family after their loved one passes. This is a covered part of the Medicare Hospice Benefit and can make a meaningful difference for spouses, adult children, and others navigating loss.
Still Trying to Sort Out What Your Family Actually Needs?
Families across Monterey County, from Pacific Grove to Salinas to Hollister, are often working through these questions in real time, after a hospitalization, during a health decline, or in the middle of a conversation with a physician that left more questions than answers. Central Coast VNA & Hospice has been helping families in this region find clarity since 1951, and a care coordinator is available to talk through what options may apply to your specific situation. You can reach the team at 831-372-6668 or visit ccvna.com to learn more.

What Medicare Covering Palliative Care Could Mean for Your Family
Most families who call asking about palliative care say the same thing: they assumed it was another word for hospice. That misunderstanding has real costs. Families in Salinas, Pacific Grove, and King City who waited until hospice was the only conversation left often lost months of symptom management and care planning support they were already entitled to.
On July 1, 2026, the Centers for Medicare and Medicaid Services proposed that community-based palliative care be covered through the existing Medicare home health benefit, separate from hospice, and available earlier in a serious illness. CMS stated that 'skilled palliative care services can be furnished and billed under existing Medicare home health benefits for eligible patients with serious illnesses.' That is a meaningful shift in federal policy, even before it becomes final.
This article explains what palliative care meaning actually is in plain terms, what Medicare covers today and what the proposed change could add, and what the referral process looks like for families in Monterey County who want to ask about it now.
Palliative Care Meaning: What It Actually Is and What It Isn't
Palliative care is specialized medical support focused on managing the symptoms, pain, and stress of a serious illness. It is not the same as hospice. The single most important thing to understand is that palliative care can begin at any stage of illness, even while a patient is still receiving treatment meant to cure or slow the disease.
A patient in Monterey County with advanced heart failure, COPD, advanced cancer, or dementia can receive palliative care at home while still seeing their cardiologist, oncologist, or primary care physician. The palliative team does not replace those specialists. It adds a layer of support those physicians rarely have the bandwidth to provide on their own, structured symptom management, help understanding options, and emotional and spiritual support for the whole family.
Hospice, by contrast, is end-of-life care that generally requires a patient to stop pursuing curative treatment. The two are related in philosophy but very different in timing and purpose. Families who understand this distinction early are the ones who tend to use palliative care when it can do the most good.
Conditions that commonly qualify for home-based palliative care support include:
- Advanced cancer at any stage of treatment
- Congestive heart failure with recurring hospitalizations
- COPD with significant functional decline
- Dementia with complex care management needs
- End-stage renal or liver disease
- Neurological conditions such as ALS or Parkinson's disease

What Medicare Covers Now and What the Proposed Rule Would Change
Right now, Medicare does not have a standalone palliative care benefit. Coverage depends on whether the services involve skilled nursing or therapy that meets the existing home health eligibility criteria. That means many patients with serious illness already qualify for home health services today that can include palliative-focused symptom management, they just don't always know it.
The July 2026 CMS proposed rule would clarify and expand this significantly. It would allow community-based palliative care to be billed explicitly under the Medicare home health benefit for eligible patients with serious illnesses, separate from hospice. If finalized, this could open access to structured palliative support for many Central Coast families who currently fall through the gap between standard home health and hospice.
Families should not wait for a final rule to ask about their options. The proposed change signals the direction Medicare is heading, but the care itself, skilled nursing visits, symptom management, social work support, coordination with treating physicians, is available today for patients who meet existing home health eligibility criteria. The Medicare.gov overview of home health services provides a baseline explanation of what Medicare home health currently covers and who qualifies.
For families in Monterey County navigating a loved one's serious diagnosis right now, the practical question is whether their family member already qualifies under current rules, not whether to wait for the proposed rule to finalize.
Palliative Care vs. Hospice: Key Differences at a Glance
Families often come in thinking these two terms mean the same thing. This table shows the clearest points of difference.
| Factor | Palliative Care | Hospice Care |
|---|---|---|
| When it begins | Any stage of serious illness | When curative treatment ends and life expectancy is estimated at 6 months or less |
| Curative treatment | Patient continues treatment | Patient typically stops curative treatment |
| Goal | Symptom management + quality of life alongside treatment | Comfort and quality of life at end of life |
| Medicare coverage (current) | Through home health eligibility criteria, not a standalone benefit yet | Medicare Hospice Benefit, covered separately |
| Who is on the team | RN or Nurse Practitioner, Medical Social Worker, Chaplain, coordinating with existing physicians | Nurses, Hospice Aides, Medical Social Workers, Chaplains, Volunteers, Bereavement Specialists |
| Family support | Care planning, emotional support, system navigation | Emotional, spiritual, and bereavement support through and after loss |
How Palliative Care at Home Actually Works: The Path from Referral to First Visit
Many families in Monterey County don't realize a physician referral is required to start home-based palliative care. This shows what the process typically looks like once a referral is made.
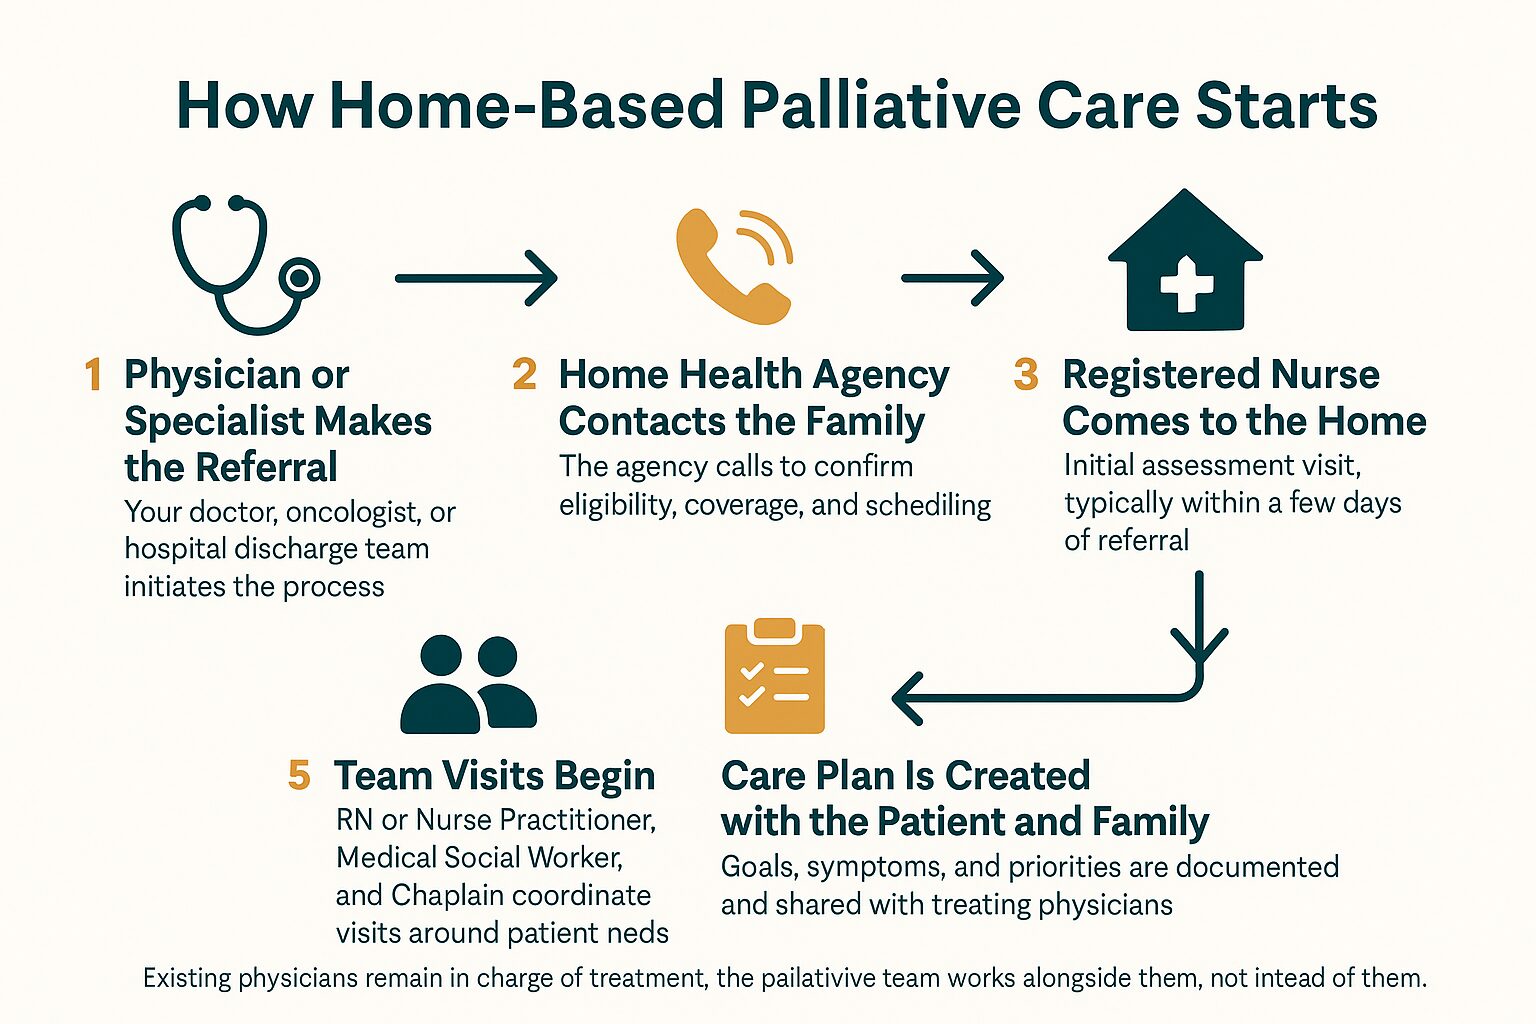
What the Referral Process Actually Looks Like, and Why It Surprises Families
One of the most consistent patterns in calls from Monterey County families is that they don't know a physician referral is required to begin any home health or palliative care service. They often assume they can simply call an agency and get started. When they learn there is a referral step, the process feels more complicated than it actually is.
In practice, it works like this: the patient's physician, oncologist, or specialist makes the referral. The home health agency then contacts the family directly to confirm eligibility, insurance coverage, and scheduling. A Registered Nurse comes to the home for an initial assessment, typically within a few days of the referral being received. From there, the full team begins coordinating visits.
Patients keep their existing physicians throughout. A palliative care team visiting a home in Pacific Grove or Salinas typically includes:
- A Registered Nurse or Nurse Practitioner managing pain and symptoms
- A Medical Social Worker helping the patient and family understand options and navigate the system
- A Chaplain providing emotional and spiritual support
All three coordinate with the patient's treating physicians rather than replacing them. For families who feel overwhelmed and don't know where to start, that first call to ask about a referral is usually the simplest step. You can also read more about what a skilled nurse actually does on a home visit to understand what that first assessment typically covers.
Why Starting Earlier Matters More Than Most Families Realize
Families who access palliative care early in a serious illness consistently describe a different experience than those who come to it late. Symptoms are better controlled. The patient has more say in their own care. The family has time to understand what lies ahead rather than making decisions in crisis mode.
The families who wait, often because they don't know palliative care exists as a separate option from hospice, sometimes describe the opposite: a scramble near the end when options narrow quickly. The article Most Families Start End-of-Life Planning Too Late goes deeper on that pattern and what changes when families ask the question earlier.
For a parent with advancing dementia in Salinas or a spouse managing heart failure on the Monterey Peninsula, the window for palliative support is often longer than families assume. The question worth asking, ideally at the next physician appointment, is not whether it's time for hospice. It is whether the current symptom load and care complexity would benefit from a dedicated palliative support team. Those are different questions, and the answer to the second one may be yes months or years before the first one becomes relevant.
If you are still weighing whether it's time to consider hospice care, understanding palliative care as a distinct earlier option often reframes that question entirely.
Frequently Asked Questions About Palliative Care and Medicare Coverage
Does Medicare pay for palliative care at home right now?
The honest answer is: it depends on how the care is structured. Medicare does not currently have a standalone palliative care benefit. But many patients with serious conditions like heart failure, COPD, advanced cancer, or dementia already qualify for home health services under existing Medicare criteria, and those services can include palliative-focused symptom management. The July 2026 proposed CMS rule would clarify and expand this, but families should not wait for it to finalize before asking about their options.
Is palliative care the same as hospice?
No. Palliative care can begin at any stage of serious illness, even while a patient is still pursuing treatment. Hospice is end-of-life care that generally involves stopping curative treatment. They share some of the same philosophy around comfort and quality of life, but they are different services with different eligibility requirements and timing.
Can my family member keep their regular doctors if they start palliative care?
Yes. The palliative care team, nurses, a Medical Social Worker, a Chaplain, works alongside the patient's existing physicians. The oncologist, cardiologist, or primary care doctor stays in charge of treatment. Palliative care adds support those specialists often don't have the bandwidth to provide, without replacing anyone.
How do we get started? Do we just call an agency?
A physician referral is required to begin home-based palliative care. The patient's doctor or specialist initiates the referral, the home health agency contacts the family, and a Registered Nurse typically comes to the home within a few days of that referral being received. Many families don't know this step is required, asking the treating physician at the next appointment is usually the fastest way to get the process moving.
What does a palliative care team actually do when they visit someone at home?
A typical home visit involves a Registered Nurse or Nurse Practitioner managing pain and symptoms, a Medical Social Worker helping the patient and family understand their options and navigate the system, and a Chaplain providing emotional and spiritual support. The team communicates regularly with the patient's treating physicians and adjusts the care plan as the patient's needs change.
What if we're not sure whether our family member needs palliative care or hospice?
That uncertainty is very common. A good starting point is reading what comfort-focused care really means and the difference between home health and hospice. A care coordinator can also walk through the specific situation and help a family understand which type of support fits where their loved one is right now.
This Care Has Been Available on the Central Coast for Over a Decade
The proposed Medicare change is new. The care itself, for families in Monterey County who know to ask for it, is not.
Central Coast VNA and Hospice has operated the only home-based palliative care program in its service area since 2015, well before palliative care at home became a national conversation. That team includes Registered Nurses, Nurse Practitioners, Physical Therapists, Occupational Therapists, Medical Social Workers, and Chaplains who have been coordinating with Monterey Peninsula physicians, Salinas Valley Health, and Community Hospital of the Monterey Peninsula for over a decade.
For a family in King City, Hollister, or on the Monterey Peninsula, the path to palliative support doesn't start with waiting to see how federal policy evolves. It starts with a conversation with the treating physician about whether a referral makes sense now. And for families who are also thinking ahead about what happens if the illness progresses, having that conversation early is consistently what families say, afterward, they wish they had done sooner.
Want to Know If Your Family Member Qualifies Right Now?
Central Coast VNA and Hospice has been serving families across Monterey County, Santa Cruz County, San Benito County, and South Santa Clara County since 1951. If your family is navigating a serious diagnosis and you want to understand whether palliative care at home is an option today, a care coordinator can walk through the specifics with you. Call 831-372-6668 or visit ccvna.com to learn more.

Respite Care for Family Caregivers: Knowing When You Need a Break
One caller described her situation in a single sentence: she was elderly herself, caring for her husband alone, and didn't know where to turn. She wasn't calling to find help for him — she was exhausted and quietly looking for permission to need something for herself. That call captures what family caregivers across Monterey County, Salinas, and the surrounding communities rarely say out loud: I am running out.
The word "respite" sounds formal, even clinical. But what it means is simple — a defined break, built into the care plan, so the person holding everything together doesn't collapse. It's not a luxury. Burnout in family caregivers has documented clinical consequences: higher rates of medication errors, missed early warning signs in the person being cared for, and serious health events in the caregiver themselves.
This article focuses on three things that actually matter to family caregivers in Monterey County right now: how to recognize when you've crossed from tired into depleted, what skilled home health and hospice services provide as real caregiver relief, and what local resources exist — specific programs, specific phone numbers — that most families never hear about until it's too late.
When Tired Becomes Something Else
Every family caregiver is tired. That's not the signal. The signal is when tired stops lifting after sleep — when you wake up at 3 a.m. reviewing a medication schedule, or you realize you haven't been to your own doctor in over a year, or you snap at your spouse over something small and then sit in the car and cry.
Clinicians who work with families navigating serious illness describe a recognizable pattern. The caregiver starts skipping their own appointments. They stop accepting invitations to leave the house. They become so attuned to the care recipient's needs that they lose track of their own physical state entirely. This isn't devotion — it's a physiological and psychological state with a name, and it carries real risks.
Burned-out family caregivers are more likely to:
- Miss early signs of deterioration in the person they're caring for
- Make medication errors — wrong dose, wrong timing, missed doses
- Experience health crises of their own — including falls, cardiac events, and hospitalization
- Delay calling for help because asking feels like failure
None of that is a personal failing. It is what happens when one person carries more than one person can carry, for longer than the human body is designed to sustain. When caring for an aging parent becomes more than you can do alone is a threshold most family caregivers cross quietly — often weeks or months before they name it.

What Skilled Home Health Actually Provides — and Why It's Different From Companionship
When most people think of getting help at home, they picture a companion — someone who sits with a loved one so the family member can run errands. That's a real service, but it's not the same as what skilled nursing care at home provides.
Skilled home health visits involve licensed clinicians — Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, and Medical Social Workers — doing work that requires clinical training. For a family caregiver, that distinction matters enormously. When a Registered Nurse comes to the home on a scheduled basis to handle:
- Medication management — reviewing the full medication list, identifying interactions, adjusting timing
- Wound care — post-surgical wound assessment, dressing changes, infection monitoring
- Condition monitoring — vitals, symptom tracking, early identification of changes that need a physician's attention
...the caregiver doesn't have to do those things that day. They can sleep. They can go to their own appointment. They can leave the house for three hours without carrying the clinical weight of the visit in their head.
This is a meaningful, structured form of respite — not because someone is keeping the patient company, but because a trained clinician is handling tasks the family would otherwise carry alone. For families in Salinas, King City, Pacific Grove, and across Monterey County, this can make the difference between sustainable home care and a crisis admission. What a skilled nurse actually does on a home visit is often a surprise to families who've never experienced it.
The Medicare Hospice Inpatient Respite Benefit — What It Covers
Most families enrolled in hospice don't know this benefit exists. Here's how the inpatient respite benefit works under the Medicare Hospice Benefit.

The Hospice Respite Benefit Most Families Don't Know About
For patients already enrolled in hospice, the Medicare Hospice Benefit includes a specific provision that almost no family hears about until a social worker or chaplain mentions it in passing: the inpatient respite benefit.
Here's what it means in plain terms. If your loved one is receiving hospice care at home, Medicare will cover a short inpatient stay — up to five consecutive days — at an approved facility. The patient receives the same hospice-level care during that stay. And the family caregiver gets a real, defined break — not a few hours, but days.
This isn't a workaround or a gray area. It is a written benefit under the Medicare Hospice program, specifically designed to support family caregivers. It does not require a medical crisis or a change in the patient's condition. It requires only that the family asks.
Many families in Monterey County discover this option only after a caregiver has already hit a breaking point. A Medical Social Worker on the hospice team can help families understand eligibility, identify an approved local facility, and coordinate the admission. If you're unsure whether a loved one qualifies for hospice and this benefit, the hospice eligibility question most families are afraid to ask addresses that directly.
Local Respite Resources for Family Caregivers in Monterey County
These are real, specific programs available to families on the Central Coast. They vary in what they offer, but each provides a form of relief that doesn't require a clinical referral to access.
| Organization | What They Offer Caregivers | Contact / How to Start |
|---|---|---|
| Monterey County Area Agency on Aging | Caregiver support programs, resource referrals, case management for older adults and their families | Call 831-755-4501 or visit the Monterey County website |
| Community Bridges — Elderday | Adult day health services in Santa Cruz area; provides structured daytime supervision so family caregivers can work or rest | Contact Community Bridges at cbridges.org |
| Community Bridges — Meals on Wheels | Home-delivered meals for homebound older adults; reduces meal preparation burden on family caregivers | Request through Community Bridges, 831-688-8840 |
| Community Bridges — Transportation | Medical and essential trip transportation for older adults and people with disabilities | Contact Community Bridges for eligibility and scheduling |
| Central Coast VNA & Hospice — Volunteer Program | Trained volunteers who can sit with patients, providing the family caregiver time away from the home | Call 831-372-6668 or visit ccvna.com |
Asking for Help Is a Clinical Decision, Not a Personal One
The emotional weight around asking for respite is real, and it runs deep. Family caregivers — especially spouses caring for a partner, or adult children caring for a parent in communities like Hollister, Seaside, or Carmel Valley — often feel that stepping back, even briefly, is a betrayal of their commitment.
But the clinical framing matters here. A family caregiver who is burned out is a less safe caregiver. The person receiving care is directly affected by the caregiver's physical and mental state. Respite isn't abandonment — it's what keeps the whole arrangement from breaking.
The National Alliance for Caregiving has documented that more than half of family caregivers report their own health has declined as a result of caregiving responsibilities. On the Central Coast, where so many older adults are cared for by spouses who are themselves in their seventies or eighties — sometimes managing their own chronic conditions — this isn't an abstract statistic. It's a pattern that families and clinicians see regularly.
The families who hold together longest are usually the ones who accepted help earlier than felt comfortable. That's not a coincidence. When is it time to think about getting help at home? is a question most families ask a few months too late.
Frequently Asked Questions About Respite Care for Family Caregivers
Does Medicare pay for respite care for family caregivers?
It depends on the situation. If the patient is enrolled in the Medicare Hospice Benefit, Medicare covers inpatient respite — up to five consecutive days at an approved facility — specifically to give the family caregiver a break. For patients receiving skilled home health (not hospice), Medicare covers skilled nursing and therapy visits based on the patient's medical needs, which can reduce the burden on the family but isn't framed as "respite" in the traditional sense. A Medical Social Worker can help you understand exactly what's covered in your specific situation.
How do I know if I'm burned out or just tired?
Tiredness lifts with rest. Burnout doesn't. If you're sleeping but waking up still depleted, skipping your own medical appointments, feeling detached from the person you're caring for, or noticing that small mistakes — like a missed medication dose — are happening more often, those are signals worth paying attention to. You don't need to be in crisis to ask for help.
Can a hospice volunteer come sit with my loved one so I can leave the house?
Yes. Trained hospice volunteers are specifically available for this. A volunteer can sit with the patient at home for a defined period — giving the family caregiver time to rest, attend appointments, or simply step away. Volunteer availability varies, but this is a legitimate and often underused part of what a hospice team offers. Ask the care coordinator or chaplain on the team about scheduling.
What's the difference between a companion service and skilled home health when it comes to giving me a break?
A companion or home aide provides supervision and personal care — bathing, meals, company. That's real support. Skilled home health brings a Registered Nurse or therapist who is doing clinical work: wound care, medication reconciliation, physical therapy assessment, disease monitoring. Both can give you a break, but skilled home health handles tasks that require clinical training — things you've probably been doing yourself without that training. That's a different kind of relief.
My parent lives in Salinas and I live in San Jose. How do we even start?
A phone call to VNA at 831-372-6668 is the simplest first step. A care coordinator can explain what services your parent might qualify for, whether a physician referral is needed, and what the coverage situation looks like. You don't need to have everything figured out before you call.
Does the patient have to agree to hospice for me to get respite help?
No. Respite support through skilled home health doesn't require a hospice enrollment — it's based on the patient's medical needs and physician orders. The inpatient respite benefit is specific to hospice, but other forms of caregiver relief through skilled nursing visits, community programs, and volunteers are available regardless of where the patient is in their care. Home health vs. hospice explains the difference between the two in plain terms.
Ready to Talk Through Your Options?
Central Coast VNA & Hospice has been supporting families across Monterey County — from Salinas to Carmel Valley to King City — for over 70 years, and the team has navigated these conversations with families at every stage. If you're wondering whether respite support is available to you, or what it would actually look like in your situation, a care coordinator can walk you through it without pressure. Call 831-372-6668 or visit ccvna.com to start the conversation.