

When a Parent With Dementia Stops Eating and Drinking Before Coming Home
Your dad is in a rehab bed in Salinas with a discharge date coming. The staff mention he is not eating much. Then someone says the word dementia in the same sentence as the words not eating or drinking, and your stomach drops.
One family wrote to a local home care team twice in about a week. The first message asked practical questions about a father with moderate dementia and a new pacemaker coming home. The second said, "My dad has multiple health challenges, one of which is dementia, which is causing him not to eat or drink."
That shift from a practical question to a frightened one is common on the Central Coast, and it usually happens in the days right before discharge. This article stays with what the change actually means, what to ask before you leave the building, how swallowing gets handled at home, and what the feeding tube decision really involves.
When Dementia Stops Eating and Drinking, It Is the Illness, Not the Food
Families read appetite loss as a problem to solve. Clinicians usually read it as the disease moving into a later stage.
In late dementia, the parts of the brain that manage hunger, thirst, chewing, and the timing of a swallow stop working the way they used to. The body also needs less fuel as activity drops. This is expected, and it is not a sign that you failed to feed your parent properly.
What that looks like at the table:
- Turning the head away or keeping the mouth closed
- Holding food in the cheek without swallowing
- Coughing or a wet, gurgly voice after thin liquids like water, coffee, or juice
- Falling asleep partway through a meal
- Eating two bites of a favorite food and being finished
Families often respond by pushing harder. More snacks, more coaxing, a bigger plate. That usually raises the stress in the room and increases the chance of food going down the wrong way.
It helps to separate two different worries. One is whether your parent is uncomfortable right now. The other is whether their intake matches a number someone wrote on a chart. The first one matters at home. The second one rarely changes the course of advanced dementia.

The Days Between the Rehab Room and the Front Door
This short window is where families in Monterey County lose the most time. Roughly a third of the calls home care teams here field each month come from people whose loved one was discharged days, or sometimes hours, earlier. Several call back just to ask whether a referral their doctor sent ever arrived.
So picture yourself in that hallway in Salinas, or at a rehab in Seaside or Hollister, with a folder you have not opened yet. While staff are still standing in front of you, ask these four things out loud:
- Has the physician written orders for home health? This is the piece that starts skilled care at home. Without an order, nothing moves. Why a physician referral is required for home health explains how that paperwork travels.
- What are the swallowing recommendations, in writing? Ask for the exact food textures and liquid consistency, not a verbal summary you will try to remember in the car.
- What medications changed during this stay? Doses get adjusted in rehab constantly, and the list you had at home is probably out of date.
- Who do we call at 2 a.m. the first night? Get a real number and a real name, not a general line.
Write the answers on the outside of the folder. The drive home from King City or Greenfield is long enough that details slip, and the first night is usually the hardest one. What the first 72 hours of home health look like covers what should happen once the car is in the driveway.
Who Does What When Eating and Drinking Change
Families often say they do not know which professional handles which part. Here is how the roles break down when swallowing is the issue.
| Role | What they work on | What you see at home |
|---|---|---|
| Speech Therapist | Evaluates swallowing, recommends food textures and liquid thickness, coaches pacing and positioning | Sits with you through an actual meal and adjusts what is on the plate and how it is offered |
| Registered Nurse | Watches hydration, skin condition, mouth care, and medication timing around meals | Checks for dryness, pressure areas, and whether pills can still be swallowed safely |
| Occupational Therapist | Works on the mechanics of getting food from plate to mouth | Brings adapted utensils, adjusts chair and table height, simplifies the setup |
| Medical Social Worker | Connects benefits, community programs, and family decision support | Helps sort out coverage questions and family disagreement about what to do next |
Swallowing Is the Part Almost Nobody Explains
A Speech Therapist is not coming to the house to help your father talk. In this situation, their job is to help him swallow without food or liquid slipping into his lungs.
That evaluation happens at the kitchen table, not in a clinic. The therapist watches a real meal, listens to his voice after a sip, and then makes concrete recommendations:
- Which liquids need thickening, and how thick
- Whether food should be soft, minced, or pureed
- How upright he needs to sit, and for how long after eating
- How long to wait between bites, and how to cue a swallow
- Which foods are high risk and which are easiest
A Registered Nurse works the other side of it, tracking hydration, mouth care, and whether medications still go down safely. Dry mouth alone can make eating miserable, and it is one of the easiest things to improve. An Occupational Therapist handles the mechanics, from the weighted spoon to the height of the chair.
Care at home is delivered by a team, and that is the point. Nurses, therapists, social workers, chaplains, volunteers, and other clinicians can be in the same house around the same plan. Speech therapy at home and who qualifies goes deeper on that specific service.
Callers here often put it simply. They just need someone to come to the house and help them figure out what to do next. That is a reasonable thing to want, and it is what an in-home evaluation is for.
Four Questions to Ask Before You Leave the Rehab Building
Ask these while staff are still in front of you. Each answer saves a phone call later.

The Feeding Tube Question, Answered Plainly
At some point a clinician may raise the option of a feeding tube. Families are asked to decide fast, often while exhausted, and almost nobody explains the tradeoffs honestly.
So here it is. For people with advanced dementia, research summarized in the medical literature has not shown that tube feeding extends life, prevents pneumonia from food going down the wrong way, heals pressure wounds, or improves comfort. Tubes also bring their own problems, including agitation and attempts to pull at them.
Declining a feeding tube is not withdrawing care. The alternative has a name, and it is comfort feeding.
Comfort feeding looks like this:
- Small amounts of favorite foods, offered for pleasure rather than a calorie target
- Ice chips, cold liquids, or a spoonful of ice cream when he wants them
- Stopping when he turns away, and trying again later
- Steady mouth care so dryness does not cause discomfort
- No clock, no quota, no forcing
This is a values conversation as much as a medical one. Your parent's physician and the home team should be in it with you, and what you decide should be written down so it holds at 2 a.m. when someone new is on the phone.
Families who choose comfort feeding are still feeding. They are still present, and they are still caring for their parent.
What Actually Drives the Cost of Help at Home
The same family that asked about their father's eating also asked what things cost. That question comes up constantly, and insurance is the single most common gateway question on local phone lines.
The honest answer starts with a category, not a number. There are two very different kinds of help, and they are paid for in different ways:
- Intermittent skilled visits, ordered by a physician and delivered by Registered Nurses and therapists. Medicare generally covers this when a patient meets the qualifying criteria, and Medi-Cal and Veterans benefits are commonly involved too.
- Hourly personal help with meals, bathing, and household tasks. This is not skilled medical care, and it is usually paid through programs like In-Home Supportive Services in Monterey County, long term care insurance, or private hire.
The cost difference between those two categories is large. One local reviewer described a situation where someone had personally hired help at a cost they put near $8,000 a month, and noted that different coverage would have changed that picture entirely. That is one family's account of their own arrangement, not a published rate, and your situation may look nothing like it.
What shifts your number: how many hours a day someone needs to be present, whether the need is medical or hands-on daily help, and which benefits your parent already has. How IHSS, home health, and private duty differ sorts those lanes out, and what home health costs families in Monterey County walks through the Medicare side. For anything specific to your parent, a care coordinator can check coverage against their actual plan.
Frequently Asked Questions About Dementia and Appetite Loss at Home
Is my parent starving if they stop eating and drinking?
It does not feel to them the way it would feel to you. In advanced illness, the body's hunger and thirst signals fade, and discomfort usually comes from dry mouth rather than an empty stomach. Steady mouth care, ice chips, and small sips often do more for comfort than a full plate.
Does a parent who stops eating automatically need hospice?
No. Appetite loss is one change among many, and it does not sort a person into a single program. Some families start with skilled home health for nursing and therapy, some add palliative care for symptom management while treatment continues, and some are ready for hospice. The right starting point depends on your parent's overall condition and what their physician recommends.
Can a speech therapist really come to the house for swallowing?
Yes, and it is one of the most useful visits a family can get in this situation. The therapist watches an actual meal in your kitchen, then gives you specific textures, positioning, and pacing to use. It is physician-ordered, like other skilled home health services.
What if we bring him home and it turns out we cannot handle it?
That fear is extremely common among families on the Peninsula and in the Salinas Valley, and bringing someone home is not a locked door. Care plans get adjusted, visit frequency changes, equipment comes and goes, and a Medical Social Worker can help you look at other options if the situation shifts. You are allowed to change course.
Who do we call if something changes overnight?
Get this answer before discharge and write it down. Home health and hospice patients should have an after-hours number that reaches a clinician, not a general voicemail. If your parent is in acute distress, chest pain, or cannot breathe, call 911 first.
If You Are Weighing What Comes Next
Central Coast VNA & Hospice has been a nonprofit serving Monterey County since 1951, now in its 75th year, with home based teams reaching Salinas, King City, Greenfield, the Monterey Peninsula, Hollister, and South Santa Clara County. Because the Speech Therapist, the Registered Nurse, and the Medical Social Worker come from one organization, families do not have to explain the same situation to three different agencies. A care coordinator can talk through what your parent's situation calls for at 831-372-6668 or at ccvna.com.

The Part of Home Health Nobody Explains: What a Medical Social Worker Does
The discharge planner runs through who will be coming to the house. A nurse. Maybe a physical therapist. And then, almost in passing, a Medical Social Worker.
That last one is where families get quiet. Does this mean someone thinks something is wrong at home? Are we being checked up on?
No. Medical social services are a standard, physician-ordered part of home health, written into the plan of care right alongside skilled nursing and therapy. One family calling about a parent put the reason for the visit better than any brochure could: they just needed someone to come to the house and help them figure out what to do next.
Why a Medical Social Worker Is on the Order in the First Place
Home health exists because a doctor decided a patient needs skilled care at home. The nurse handles wounds, medications, vital signs. The therapists handle strength, balance, safety, speech.
But the problems that actually keep a family up at night are usually not clinical. They are practical. Who pays for this. Who drives Mom to her cardiology appointment in Salinas. What happens when the eight weeks of visits end.
That gap is the Medical Social Worker's job. Medicare lists medical social services among the covered home health services when a doctor orders them as part of the plan of care, which is why the role shows up on the roster without anyone requesting it.
It is not a welfare check. It is not an evaluation of your housekeeping. The visit exists because illness drags a pile of paperwork, money questions, and family decisions into the house along with it, and somebody on the team should be trained to deal with that pile.
If you are still sorting out how the order itself got written, the physician referral process explains who sends what to whom.

What Does a Medical Social Worker Do in Home Health? The Real List
This is the part almost nobody spells out, so here it is plainly. A Medical Social Worker handles the pieces that sit outside the nursing visit:
- Benefits and coverage problems. Denied claims, plans that do not match, an old policy nobody has touched in years.
- Applications and paperwork. Medi-Cal, county programs, forms that ask questions a tired family cannot answer alone.
- Community referrals. Hourly help, meals, transportation, support groups, equipment.
- Family disagreements. Two adult siblings who want different things for the same parent is one of the most common reasons this visit matters.
- Care planning conversations. What the family wants care to look like if things change, and what they want it to look like if they do not.
One Monterey Peninsula family described it concretely in a public review: "She helped us find the right agency to cancel her mom's Medicaid in FL and recommended additional resources in the community."
That is the shape of the work. An out-of-state plan nobody knew how to close, plus a short list of places to call next.
The Local Referral List Is the Most Useful Thing in the Bag
Home health is intermittent skilled care. Visits, not shifts. So when a family needs hourly help with bathing, meals, or overnight supervision, that need falls outside the home health benefit.
The Medical Social Worker is usually the person who points the family somewhere real. IHSS, county aging programs, private duty agencies, food support, transportation help. Intake staff do a version of this on the phone every week, handing callers two or three local options when the request does not fit what home health covers.
Geography is the whole reason this matters here. Roughly 65,000 Monterey County residents are 65 or older, about 14.9% of the population, and households headed by someone over 65 report a median income well below the county overall, with close to one in ten families below the poverty line.
And those households are not evenly spread. A family in King City, Greenfield, or Hollister is working with a much thinner set of nearby options than a family in Monterey or Pacific Grove. A current local referral list beats a printed brochure every time in that situation.
If you are trying to sort out which kind of help you actually need, IHSS, home health, and private duty each cover different ground.
Bring These Up in the First Visit or Two, Not the Last
A home health episode is measured in weeks of intermittent visits, not months. The paperwork questions need to surface early, while there is still time to act on them.
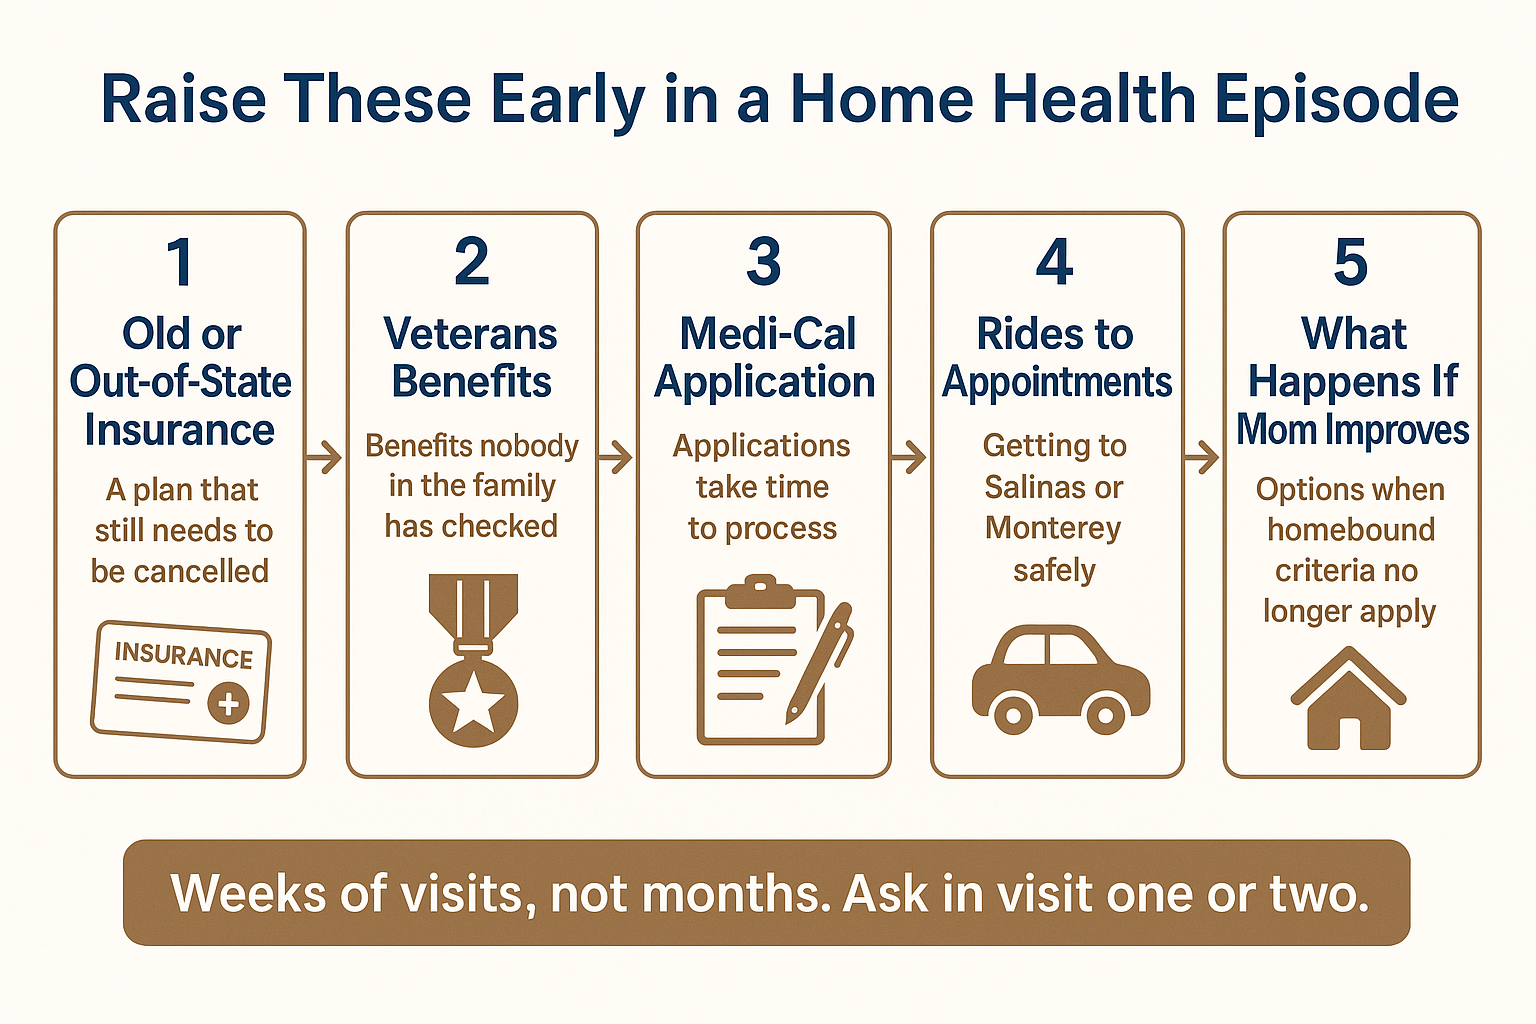
The Three Money Buckets Families Confuse
Insurance and referral questions come up in roughly 8% of incoming calls, often before anyone describes the patient's condition at all. One family wrote in about a father coming home from rehab after a pacemaker with moderate dementia and asked, straightforwardly, what services were offered and roughly what they cost. The honest answer starts with separating three different buckets.
| Bucket | What It Generally Applies To | What to Ask |
|---|---|---|
| Medicare | Skilled visits under a physician-ordered home health plan, which can include nursing, therapy, and medical social services for eligible patients | Whether your specific plan limits which agency you may use |
| Medi-Cal | May reach services and supports Medicare does not, including certain county and in-home support programs | Eligibility rules and how long an application takes |
| Veterans benefits | Home-based care and supports many families never think to look into | Which programs the veteran is already enrolled in |
| Private pay | Hourly non-medical help, overnight supervision, long stretches of personal care | Hourly rate, minimum hours, and how a month actually adds up |
Why Nobody Should Quote You a Price Over the Phone
Costs vary widely depending on what kind of help is needed, how many hours, and which coverage a household already has. Two families in the same Salinas neighborhood can land in completely different places.
So the useful move is not a number. It is a map. The Medical Social Worker is frequently the person who sits down and sorts a specific household into those buckets, then tells the family which doors are actually open to them.
For exact figures, your provider and your plan are the only reliable sources. Anyone giving you a firm dollar amount before they know the diagnosis, the coverage, and the hours is guessing.
Families planning a discharge often miss these questions entirely in the rush home. What gets overlooked when a hospital discharge is being planned is worth reading before the car pulls into the driveway. And if a veteran is involved, the benefits most families do not know to ask about can change the whole picture.
Frequently Asked Questions About Medical Social Workers in Home Health
Is the Medical Social Worker there to check up on us?
No. The visit is ordered by the physician as part of the home health plan of care, the same way nursing or therapy visits are. The focus is the practical problems around the illness, not a judgment about the household.
Does the visit cost extra?
Medical social services are generally included within the physician-ordered home health benefit for eligible patients rather than billed as a separate add-on. What your household owes depends on your coverage, so check with your plan or the agency's intake team for specifics.
Can they arrange hourly help with bathing and meals?
They do not provide that care themselves, because home health is intermittent skilled care. What they do is connect you to IHSS, county programs, and private duty agencies that handle hourly and overnight support, and help you understand which ones your parent may qualify for.
What if my parent lives in King City, Greenfield, or Hollister?
Service area questions come up constantly on the phone, and distance genuinely changes which resources are realistic. Fewer nearby options makes the referral list more valuable, not less, since the worker keeps track of what is actually running in south county and San Benito County right now.
What happens when home health ends?
That is exactly the conversation to start early. If a parent improves enough that they no longer meet homebound criteria, or the episode simply runs its course, the Medical Social Worker can lay out what community supports, private options, or other programs could carry things forward.
Questions About How Home Health Works on the Central Coast
Central Coast VNA & Hospice is a nonprofit founded in 1951 and marking 75 years in 2026, with Medical Social Workers working alongside Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Chaplains, Bereavement Specialists, and Volunteers across Monterey County, San Benito County, South Santa Clara County, and parts of Santa Cruz County. Medicare, Medi-Cal, and Veterans benefits are accepted. Families with questions are welcome to call 831-372-6668 or visit ccvna.com to speak with a care coordinator.

Who Brings the Hospital Bed? How Medical Equipment Reaches the House
A discharge planner at Community Hospital of the Monterey Peninsula or Salinas Valley Health says the words hospital bed, and then the conversation moves on to medications. Nobody stops to explain who orders the bed, who brings it, or when it shows up at the house.
Families across Monterey County call about home care on that same compressed clock. A parent is coming home tomorrow, the living room still has a couch in it, and someone has to figure out where an oxygen concentrator plugs in.
This is the practical sequence: how equipment gets ordered, who pays for what, how hospice changes the math, and whether the bed will even fit through the front door of a 1920s house in Pacific Grove.
Who Orders the Equipment and Who Delivers It
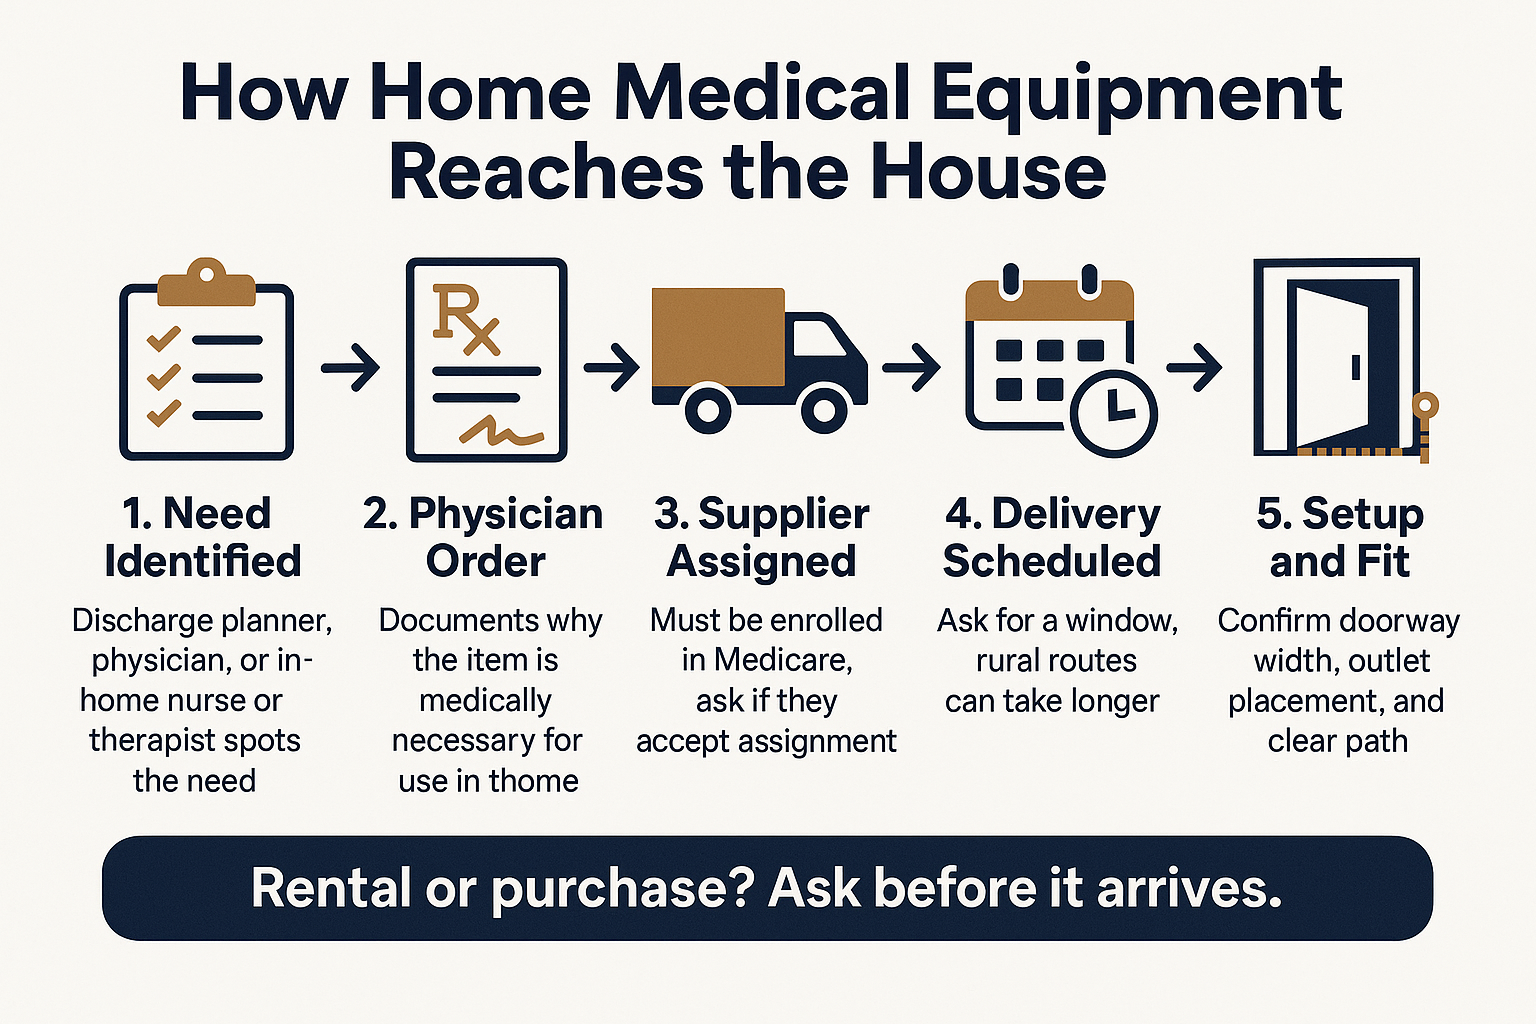
Home medical equipment does not come off a store shelf. For it to be covered, it generally needs a physician order documenting why the item is medically necessary for use inside the home, and it has to come from a supplier enrolled in Medicare.
The person who spots the need is often not the doctor. It is frequently a Registered Nurse or Physical Therapist on the first in-home visit, watching how someone actually moves through their own hallway, their own bathroom door, their own bedroom.
That visit catches things a hospital room never will:
- A bathroom doorway too narrow for a standard walker
- A bed too low for someone to stand up from safely
- A second-floor bedroom with no realistic way to get a hospital bed upstairs
- No outlet near the chair where the person actually sits all day
When a physician orders a pre-surgery home assessment, a lot of these decisions get made weeks early instead of in a scramble after discharge. One local patient put it plainly in a review: "The nurse that assess my environment prior to surgery left me with useful information."
If the equipment need surfaces after discharge instead, expect the order, the supplier, and the delivery to move on separate tracks. That is exactly where families get stuck, and it is worth reading up on what comes next after a hospital discharge before the day arrives.

Who Pays for a Hospital Bed at Home
Here is where families get surprised. Home health visits and home medical equipment are paid for in two different ways, even when both are happening in the same house on the same week.
Under Original Medicare, durable medical equipment falls under Part B. Per Medicare's own coverage rules for durable medical equipment, the item must be ordered by your provider for use in the home, must come from a Medicare enrolled supplier, and the patient is generally responsible for 20 percent of the Medicare approved amount after the annual Part B deductible when the supplier accepts assignment.
A few things change that picture:
- Deductible and approved amounts change every year, so last year's numbers are not this year's numbers
- Medicare Advantage plans set their own networks, prior authorization rules, and cost sharing
- Medi-Cal and Veterans benefits work on different rules entirely
- A Medigap policy may absorb part of the coinsurance
The practical trap worth knowing: a supplier that is not enrolled in Medicare, or one that does not accept assignment, can bill more than the approved amount. That difference lands on the family.
Confirm the numbers with the plan and the supplier before anything is delivered, not after. If a plan restricts which providers can be used at all, Medicare plan network limits are worth understanding early.
Hospice Changes the Equipment Math Completely
This is the piece families tend to learn late, often after weeks of worrying about bills.
Under the Medicare hospice benefit, equipment and supplies related to the terminal illness are part of the benefit itself. The hospice team arranges the bed, the wheelchair, the oxygen concentrator, and the supplies, and those items are not billed separately to the family the way Part B equipment is.
That means the calculation for a family weighing hospice at home in Salinas or Carmel Valley is different from the calculation for a family arranging equipment after a knee replacement. Same bed, same living room, different rules.
It does not cover everything. Room and board in a facility is a separate question, and one that trips up plenty of families, which is why who pays for hospice room and board is worth reading on its own.
But for equipment inside the house, the difference is real, and it is one of the more common surprises people mention once they finally understand how the benefit is built.
How Equipment Coverage Differs by Situation
A quick side by side of how the same hospital bed gets handled depending on which program a patient is under. Always confirm specifics with your own plan.
| Situation | Who arranges the equipment | What the family typically handles |
|---|---|---|
| Home health under Original Medicare | Physician order plus a Medicare enrolled supplier | Part B deductible, then generally 20 percent of the approved amount |
| Home health under Medicare Advantage | Plan network supplier, often with prior authorization | Plan-specific copay or coinsurance, network rules apply |
| Hospice under the Medicare hospice benefit | Arranged through the hospice team | Equipment related to the terminal illness is part of the benefit |
| Medi-Cal or Veterans benefits | Program-specific authorization process | Different cost sharing rules, confirm before delivery |
The Path From Order to Delivery
The sequence most families never get explained to them at discharge, laid out step by step.
Will It Actually Fit the House?
Almost nobody addresses this until the delivery driver is standing in the doorway with a bed frame.
Older homes on the Monterey Peninsula are charming and tight. Cottages in Pacific Grove, houses tucked into the hills in Carmel, bungalows in old Monterey. Many have doorways under 30 inches, sharp turns at the top of a staircase, and bedrooms on a second floor that a hospital bed is never getting to.
Walk the house before delivery day and check:
- Doorway width at every door the equipment must pass through, including the bathroom
- Turning space in hallways and at the top or bottom of stairs
- Whether the living room becomes the bedroom, which is the answer more often than families expect
- Where an oxygen concentrator can sit near an outlet without running a cord across a walking path
- A clear path wide enough for a walker, which usually means moving a rug, a side table, or both
Delivery timing matters too. Routes out to King City, Hollister, and the south county can stretch beyond a same-day window, so ask what the actual timeframe is rather than assuming the bed arrives the afternoon of discharge.
A safe layout is a big part of what makes staying home possible over the long run, not just for the first week.
Rent or Buy? It Comes Down to How Long the Need Lasts
The honest question is not which is cheaper. It is how long this equipment will be needed.
Recoveries after orthopedic surgery, a stroke, or a fall often run weeks, not years. Renting keeps a family from buying a hospital bed in March that sits in the garage by September.
And needs move in both directions. A walker becomes a wheelchair. A wheelchair becomes a hospital bed. Sometimes a person improves and the bed goes back.
Being able to swap or return items keeps the house matched to the person's condition right now instead of their condition last month. That flexibility matters most in the first few weeks, when things change fast. The first 72 hours of home health tend to reveal needs nobody predicted from a hospital bed.
Questions Worth Asking Before Anything Is Delivered
Families repeatedly describe being handed a plan at discharge and then having nobody to call when the pieces do not arrive. These are the questions that prevent that.
Ask the discharge planner, the supplier, or a plan representative:
- Who is the supplier, by name, and what is their direct phone number?
- Are they enrolled in Medicare, and will they accept assignment?
- Is this a rental or a purchase?
- Who services it if a motor fails or a rail sticks?
- Who picks it up when it is no longer needed, and is there a charge?
- What will we owe, and when will we see a bill?
Write the answers down. Get a name attached to each one.
If a physician referral is part of the picture, how the referral process actually works explains the paperwork side that often runs in parallel with the equipment order.
Frequently Asked Questions About Home Medical Equipment
Can I just buy a hospital bed online instead of going through all this?
You can, but Medicare will not pay for it. Coverage requires a provider's order and a Medicare enrolled supplier. If you buy retail, the full cost is yours, and you also give up service, swaps, and pickup when the need ends.
How fast can equipment show up after discharge?
It depends on the order, the supplier, and where you live. Homes on the Peninsula and in Salinas usually see faster routes than King City or Hollister. Ask for a specific delivery window rather than assuming same day, and confirm someone will be home to accept it.
Does the home health nurse bring the equipment?
No. Clinicians identify what is needed and document it, but delivery comes from the supplier. Those are two separate visits, often on different days, which is why families sometimes think something went missing when nothing actually did.
What if my parent's condition changes and the equipment no longer fits the need?
That is normal, and it is the main argument for renting. Equipment can often be swapped or returned as needs shift in either direction, so the house stays matched to the person's current condition.
Are supplies like bed pads and gloves covered the same way as the bed?
Not always. Disposable supplies are handled differently from durable equipment under Part B, and the rules shift again under the hospice benefit, where related supplies are included. Ask the supplier and your plan to spell out which specific items are covered before they arrive.
Still Sorting Out What Your Parent's House Needs?
Central Coast VNA & Hospice rents home medical equipment directly, including hospital beds, wheelchairs, walkers, crutches, scooters, and oxygen concentrators, with items that can be swapped or returned as a patient's condition changes. Home health teams across Monterey County include Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, chaplains, and volunteers who look at the home itself, not just the diagnosis. A care coordinator can walk through how equipment and coverage would work for your specific situation at 831-372-6668 or ccvna.com.

The First 72 Hours of Home Health After a Hospital Stay
The call usually comes with almost no warning. A hospital case manager says your mother is being discharged this afternoon, and suddenly you have hours, not days, to figure out what care at home is going to look like.
Families across Monterey County describe this same moment over and over. Discharges from Community Hospital of the Monterey Peninsula, Salinas Valley Health, and Natividad often move faster than anyone expects, and the drive home to Pacific Grove, Salinas, or King City is spent wondering who is going to walk through the door and when.
This is a plain look at what the first 72 hours of home health actually involve, so that part of the day stops being a mystery.
Why the Window Between Discharge and Home Feels So Short
Hospitals decide a patient is ready to go home based on clinical criteria, not on how prepared the family feels. Once that decision is made, the discharge itself can happen in a matter of hours.
The piece that surprises most families is the paperwork. Home health cannot start on a family's request alone. A physician's order is required before any agency can schedule a visit, which is why hospital case managers and discharge planners are usually the ones who set the referral in motion. If you want the detail on that step, a physician referral is required for home health and it works differently than most people assume.
A few things worth confirming before your loved one leaves the building:
- Which home health agency the referral was sent to, and whether they cover your town
- Whether the order includes therapy, nursing, or both
- The discharge medication list, printed, and who to call with questions about it
- Any equipment ordered, such as a walker, bedside commode, or hospital bed
Geographic coverage matters more here than people expect. A family in Carmel Valley, Hollister, and Watsonville may all get very different answers about who can reach them, so it is worth asking directly rather than assuming.
The First Visit Is an Evaluation, and Care Starts Anyway
The first home visit after a hospital stay is technically an evaluation visit. That word makes it sound like paperwork, but clinical care begins the moment the nurse walks in.
A Registered Nurse typically arrives within a day or so of the patient getting home, sometimes the same day for higher-risk discharges. In that first hour, the nurse is doing several jobs at once:
- Reviewing the full medication list, hospital orders and home bottles both
- Checking surgical sites or wounds and how they are healing
- Taking vital signs and comparing them to what the hospital recorded
- Looking at the home itself for fall risks, poor lighting, loose rugs, stairs, bathroom setup
- Asking how the patient slept, ate, and moved since getting home
That visit also builds the care plan that governs everything after it. It determines whether a Physical Therapist, Occupational Therapist, Speech Therapist, or Medical Social Worker gets added, and how often each one comes.
One Monterey Peninsula family described exactly this order of events in a public review: a nurse came first to evaluate, then a weekly nurse, then a Physical Therapist who built an exercise plan and kept adjusting it. That sequence is normal. Families are often surprised how much gets settled in the first hour. What a skilled nurse actually does on a home visit goes deeper on the clinical side.

Medication Reconciliation: The Highest-Stakes Task of the First Three Days
If there is one thing that goes wrong in the first days home, it is medication. Hospital discharge paperwork frequently does not match what is already sitting in the medicine cabinet at home.
The usual gaps look small on paper and are not:
- A dose was changed in the hospital, but the old bottle is still on the counter
- A new drug interacts with something the patient has taken for years
- A blood thinner or blood pressure medication was stopped, and nobody at home knows it
- Two bottles with different names contain the same active ingredient
A nurse comparing both lists side by side is the safety net that keeps a paperwork mismatch from turning into an emergency room trip. This is also why the nurse asks you to gather every bottle in the house, including supplements, eye drops, and anything from a previous hospitalization.
One family in Monterey County wrote in describing a parent in their 80s whose five-plus medications had simply become too confusing for a spouse to track. That is a common situation, not a failure. It gets harder when memory is involved, and dementia can turn medication management into a real safety issue very quickly.
Keep a single written list going forward, and update it after every appointment.
Who May Come Through the Door in the First Week
Not every patient sees every role. The care plan built during the evaluation visit decides who is added, based on the diagnosis and what the physician ordered.
| Role | What they focus on | Typical early pattern |
|---|---|---|
| Registered Nurse | Medications, wounds, vital signs, teaching the family what to watch for | First visit, then often 1-3 times a week |
| Physical Therapist | Strength, balance, walking safely, fall prevention | Starts within the first week if ordered |
| Occupational Therapist | Bathing, dressing, kitchen and bathroom safety, daily routines | Added when independence at home is the concern |
| Speech Therapist | Swallowing, speech, and thinking skills after stroke or illness | Added by order, less common overall |
| Medical Social Worker | Benefits, community resources, family stress, planning ahead | Often one or two visits early on |
| Home health aide | Personal care support under the care plan | Varies by plan and eligibility |
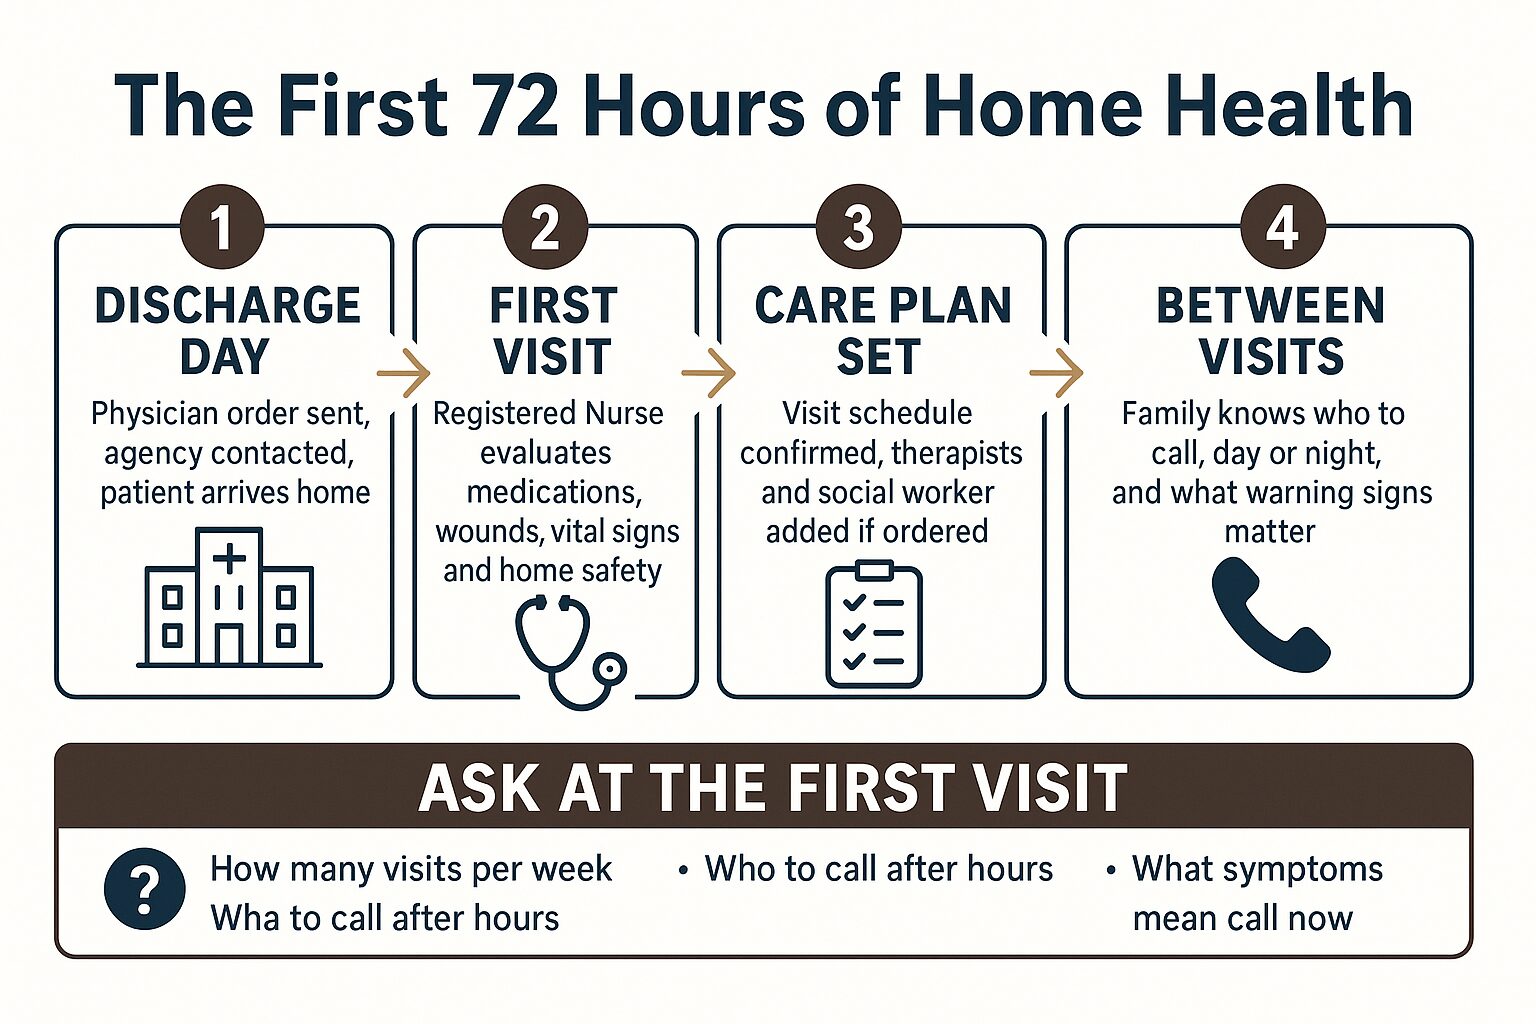
The First 72 Hours at a Glance
A simple map of how the first three days usually unfold once a patient gets home.
Home Health Is Intermittent, Not Around-the-Clock Care
This is the single biggest misunderstanding families run into, and it is better to hear it now than on day two. Home health is intermittent skilled care, which means visits a few times a week, not a nurse in the house all day.
A typical early schedule might be two or three nursing visits a week, plus therapy visits on separate days. Medicare's own description of the home health benefit spells out that it covers part-time or intermittent skilled care, not continuous supervision.
The gaps between visits are when families feel most anxious, especially in week one. Two questions asked at the first visit make those gaps far easier:
- How many visits a week should we expect, and on which days
- Who do we call at 9pm on a Saturday, and what number is that
If your loved one genuinely needs someone present most of the day, that is a separate kind of help. Private-duty hourly care is paid out of pocket in most cases, and in Monterey County round-the-clock coverage can run into the thousands of dollars a month depending on hours and agency. Costs vary widely, so get real numbers before assuming anything. Many families combine a clinical home health team with private hourly help, and a Medical Social Worker can point you toward local options.
What families in Monterey wish they had known sooner about home care covers more of this territory.
What the Team Is Quietly Watching For
The riskiest stretch after a hospital stay is the first 30 days. That is when avoidable returns to the hospital happen most often, and usually not because of one dramatic event.
Most of the time, something small was missed. A wound that looks slightly worse each day. A new medication causing dizziness that gets written off as tiredness. A patient who seems more confused than they should be for this point in recovery.
A family member without clinical training has no reason to catch those patterns. A nurse or therapist who saw the patient on Monday and sees them again on Thursday does, because they have a baseline to compare against. Part of the job in those first days is straightforward detective work.
What you can do between visits:
- Write down anything that changes, even if it seems minor
- Note appetite, sleep, and how far they walked each day
- Take a phone photo of a wound if you were told to watch it
- Call the after-hours line rather than waiting for the next scheduled visit
That last one matters. Families are rarely wrong when they feel that something is off, and the team would much rather get the call.
If recovery is more about relearning daily tasks than healing a wound, occupational therapy at home after a hospital stay explains what that side of the plan involves.
Frequently Asked Questions About the First Days of Home Health
How soon after discharge will someone actually come to the house?
It depends on when the order arrives and how urgent the situation is, but the first visit commonly happens within 24 to 48 hours of the patient getting home. Some post-surgical cases start sooner. Ask the discharge planner to confirm the timing before you leave the hospital, and call the agency directly if you have not heard anything the next morning.
Does Medicare cover home health, and do we need a doctor's referral first?
Yes to both, in most cases. Medicare covers eligible home health services, and a physician's order is required before any visit can be scheduled. Medi-Cal and Veterans benefits also cover home-based care for eligible patients. Coverage depends on meeting the criteria, so a quick conversation about the specific situation is worth more than a general answer.
What if my parent needs help every single day, not just a few visits a week?
That is a real and common gap. Home health provides skilled clinical visits, while daily hands-on help with meals, bathing, and companionship comes from private-duty agencies, family, or community programs. Many Monterey County families run both at once, using the clinical team as the medical anchor and hourly help for the rest of the day.
Is this the same thing as hospice?
No. Home health is focused on recovery, rehab, and managing a condition so someone can get back to independence. Hospice begins when the goal shifts from curing to comfort. They are different programs with different eligibility, and mixing them up is one of the most frequent points of confusion on first calls.
How do I know the person at my door really works for the agency?
Ask for a photo ID badge, and call the agency's main number to confirm. A legitimate agency will never ask for personal or financial information before an in-person assessment has been arranged. If anything feels off, stop and verify. Nobody will take offense.
Questions about care at home on the Central Coast?
If a hospital stay just ended and you are trying to sort out what happens next, a care coordinator can walk you through how home health works and whether it fits your family's situation. Central Coast VNA & Hospice has been serving families in Monterey County and the surrounding Central Coast since 1951, and you can reach someone at 831-372-6668 or at ccvna.com. There is no cost to ask a question.

Veterans and Home-Based Care: Benefits Most Families Do Not Know to Ask About
Your father spent decades in uniform. He knows how to fill out a form, how to sit on hold, how to work a system that does not want to be worked. And yet when the hospital says he needs care at home, nobody in the family knows which benefit actually pays for it.
That gap shows up constantly on the Central Coast. Families in Monterey, Salinas, Seaside, and Hollister take whatever plan the discharge planner hands them, never asking whether their veteran had a second or third benefit pathway available the whole time.
This article walks through the pathways veterans and their families most often miss, how VA and Medicare hospice benefits can interact, and why living an hour from a VA facility does not cut you off from care at home.
Why Veteran Benefits and Home Care Feel Like Two Separate Mazes
Veterans are usually the ones helping other people figure out paperwork. That is what makes this so disorienting when it happens to them.
Central Coast VNA & Hospice's 2025 annual report includes a firsthand account from a local veterans affairs director who spent 24 days in UCSF's Cardiac Critical Care Unit and then had to find home care to be discharged to. His description of that stretch is the clearest version of this problem anyone has written down: "Healthcare is its own complicated country, and we were trying to move through it while simultaneously hurting, healing, and feeling quite lost."
He had spent a career helping veterans find the right door. He still could not find his own.
His family is not unusual. The people staffing a hospital discharge desk know Medicare home health cold. They do not always know how a veteran's VA enrollment, service-connected disability rating, or priority group changes what is available.
So the family gets one option, takes it, and never learns there were others. That is not anyone acting in bad faith. It is just two systems that were built separately and never sat down together.

How Veterans Can Access Home Health and Hospice Benefits: Three Doors, Not One
Most families assume there is one payer and one plan. In practice a veteran may have coverage through more than one channel, and the rules about how they coordinate are complicated enough that it is worth asking directly.
The pathways worth asking about:
- VA healthcare benefits. Depending on enrollment status, priority group, and service connection, the VA may arrange or pay for home-based skilled care and hospice services through community providers.
- Medicare Part A. This is the standard route for home health and the Medicare hospice benefit. Most veterans over 65 have it alongside their VA coverage.
- Medi-Cal. For veterans who meet income and asset requirements, Medi-Cal can cover services or fill gaps the other two do not.
These are not always mutually exclusive. But the coordination rules are dense, and no family should be expected to sort them out from a hospital hallway.
One more thing that trips families up regardless of which door they use: a physician's order is required before home health can be scheduled. Roughly one in ten calls to local home health agencies involves a family surprised by that step, which is why understanding why a physician referral is required for home health ahead of time saves days.
A Medical Social Worker is the person who maps all of this. Ask for one by name during the referral conversation, not after.
Three Benefit Pathways at a Glance
Coverage details depend on the individual veteran's enrollment, service connection, and income. This table is general orientation, not a determination of what any one person qualifies for.
| Pathway | Generally Used For | Who Can Help You Confirm It |
|---|---|---|
| VA healthcare benefits | Home-based skilled care and hospice arranged through community providers; may cover items other benefits do not | VA social worker, county Veterans Service Office, or a Medical Social Worker at the home health agency |
| Medicare Part A | Intermittent skilled nursing, physical, occupational and speech therapy, and the hospice benefit | Discharge planner, physician's office, or the home health agency's intake team |
| Medi-Cal | Coverage for veterans meeting income and asset limits; can fill gaps left by other coverage | County social services, a Medical Social Worker, or the agency handling the referral |
VA Hospice and Medicare Hospice Are Not Always an Either/Or
This is the single most common thing families do not know to ask about.
When a veteran is nearing the end of life, families often assume they must pick one benefit. The VA offers hospice benefits that in some circumstances can work alongside the standard Medicare hospice benefit rather than instead of it.
In certain cases the VA benefit covers things the Medicare hospice benefit does not, including some medications and some care settings. Nobody volunteers this information. You have to ask about VA hospice coordination specifically when care is being set up.
The VA's geriatrics and extended care program is the starting point for understanding what a veteran's enrollment makes available. A county Veterans Service Office can help sort out the rest.
Worth saying plainly: asking about hospice benefits is not the same as choosing hospice. Plenty of families ask early, learn what exists, and use none of it for another year. If eligibility is the part that worries you, the hospice eligibility question most families are afraid to ask covers it directly.
Five Questions to Ask Before Care Starts
These are the questions that open doors families did not know were there. Ask them during the referral conversation, not after care has already begun.

Hollister, King City, and the Salinas Valley: Distance From a VA Facility Is Not the Whole Story
Geography does real damage to veteran benefit access on the Central Coast, but not always in the way families assume.
A veteran in King City or out past Greenfield may be a long drive from any VA facility. Families in San Benito County sometimes decide that puts them outside the range of meaningful veteran support entirely, and they stop asking.
That conclusion is usually wrong. VA-coordinated home health and hospice services can be delivered by community providers with agreements in place, which means the care comes to the house in Hollister rather than the veteran driving to the care.
Home-based nonprofits have covered this ground for a long time. An office opened in Hollister back in 1974 to bring skilled nursing and therapy to San Benito County, and the four-county service footprint across Monterey, San Benito, Santa Cruz and South Santa Clara counties has held since.
What this means practically: the question is not "how far are we from the VA?" It is "which providers in our area coordinate with the VA?" Those are very different questions with very different answers.
Agent Orange, Burn Pits, and the Conversation Veterans Tend to Avoid
Veterans who served in eras with known toxic exposure, including Agent Orange in Vietnam and burn pits in Iraq and Afghanistan, may have chronic conditions that qualify them for specific VA healthcare programs.
As those conditions progress, home health or palliative care can become medically necessary. The clinical need is real. The paperwork usually is not the problem.
The problem is that many veterans will not describe their health in the terms that trigger eligibility. Saying "I am short of breath most days and I stopped walking to the mailbox" feels like complaining. So they say "I'm fine" instead, and the benefit conversation never starts.
A Medical Social Worker who has worked with veteran benefits knows how to translate that. So does an adult child who understands that describing symptoms accurately is not the same as asking for a handout.
One related note on cost, since families always ask. Home health and hospice benefits cover intermittent skilled visits, not round-the-clock help in the house. Families in Monterey County who need daily hands-on assistance often end up paying privately for that piece, and those costs can run well into the thousands per month depending on hours. It is worth asking early which portion a benefit covers and which portion it does not, which is a big part of what families miss when planning a hospital discharge to home.
Frequently Asked Questions About Veteran Home Health and Hospice Benefits
Does my veteran have to give up VA care to use Medicare home health?
Not necessarily. Many veterans carry both VA benefits and Medicare Part A, and the two can often be coordinated rather than traded. The rules depend on enrollment, service connection, and the specific service, so ask a Medical Social Worker or your county Veterans Service Office to confirm your veteran's situation before you assume you have to pick.
We live in Hollister. Are we too far out for VA-coordinated home care?
Usually not. VA-coordinated home health and hospice can be delivered by community providers in San Benito County, so the visits happen at the house rather than requiring a drive to a VA facility. Distance from a VA campus and access to VA-coordinated care are two different things.
How fast can care start after a hospital discharge?
Once a physician's order is in hand, home health agencies on the Central Coast typically move quickly, sometimes within a day or two of the veteran getting home. The delay is almost never the agency. It is the order. If a discharge is coming up, ask the hospital to send that order before the patient leaves the building.
What is the difference between home health and hospice for a veteran?
Home health is skilled care aimed at recovery and stability, like wound care, therapy after surgery, or managing heart disease and COPD at home. Hospice begins when the goal shifts from curing to comfort. Many veterans use home health for years before hospice ever comes up. The piece on home health vs. hospice breaks down how families tell which one fits.
Who actually shows up at the house?
Depending on the plan of care, that can include Registered Nurses, Licensed Vocational Nurses, Physical Therapists, Occupational Therapists, Speech Therapists, Medical Social Workers, Hospice Aides, Chaplains, and trained Volunteers. Ask during intake which team members are part of the plan so nobody is surprised by a knock at the door.
Questions About a Veteran's Options for Care at Home?
If you are sorting through benefits for a veteran in Monterey County, Salinas, Hollister, or anywhere along the Central Coast, a conversation with a care coordinator can help you understand what pathways exist before any decisions get made. Central Coast VNA & Hospice accepts Medicare, Medi-Cal, and Veterans benefits, and has been caring for families in this region since 1951. You can reach a care coordinator at 831-372-6668 or find more information at ccvna.com.

Occupational Therapy at Home: What Really Happens After a Hospital Stay
Your mother is discharged from Community Hospital of the Monterey Peninsula after a knee replacement. The paperwork includes a referral for home health, and you assume that means a nurse will come check the incision.
Then someone calls to schedule an Occupational Therapist. Most families have no idea what that visit is for, and almost nobody expects how practical it turns out to be.
This is a look at what occupational therapy at home actually does after surgery, what the therapist is watching for in your parent's house, and how Medicare coverage works for these visits in Monterey County.
What an Occupational Therapist Is Actually Evaluating
An Occupational Therapist who comes to the house is answering one question: can this person safely do the ordinary activities of daily life in their real environment?
That sounds simple until you break down what a single morning requires. Getting out of bed, standing at the sink, stepping over a tub wall, reaching a shelf, buttoning a shirt, carrying a plate from the stove to the table. Surgery disrupts the strength, balance, and sometimes the mental focus that all of those tasks quietly depend on.
So the therapist watches the patient do them. Not describe them. Actually do them.
Common areas an Occupational Therapist works on after a hospital stay:
- Bathing and toileting, including how someone gets in and out of a shower or tub
- Dressing, especially lower-body dressing after hip or knee surgery when bending is restricted
- Meal preparation, from standing tolerance at the counter to safely handling hot pans
- Moving between rooms, including the path from bed to bathroom at 2 a.m.
- Energy management, so a patient does not spend all their strength before lunch
The plan that comes out of this is built around that specific house. The layout, the furniture, the height of the bed, the habits of the person living there. A clinic gym cannot tell you whether the hallway in a Pacific Grove cottage is wide enough for a walker. The home visit can.

The Home Safety Assessment Catches What a Hospital Room Never Will
A hospital room is flat, wide, and built for medical equipment. Almost no home on the Central Coast looks like that.
Under the Orthopedic Program at Central Coast VNA & Hospice, a home safety assessment can happen before surgery when a physician orders it, and care can begin within 24 hours of a patient returning home. Either way, the therapist is looking for the same things.
What gets flagged during a home safety review:
- Fall risks like throw rugs, extension cords, low lighting, and pets underfoot
- Bathroom access, which is where a large share of household falls happen
- Stair navigation, including the short entry steps common in older Monterey and Seaside homes
- The bed to bathroom path, walked at night, in the dark, half asleep
- Whether a walker or wheelchair actually fits through the doorways it needs to clear
These are not hypothetical hazards. Older homes in Carmel, Pacific Grove, and the older Salinas neighborhoods often have narrow hallways, raised thresholds, tubs with high walls, and stairs with a handrail on only one side.
If you want the wider picture of what a discharge plan should include, it is worth reading what families often miss when planning a hospital discharge to home.
Occupational Therapy vs. Physical Therapy at Home
Families often assume these are the same service with different labels. They overlap, but the focus is different. Many patients receive both.
| Focus Area | Physical Therapist | Occupational Therapist |
|---|---|---|
| Main question | Can this person move, walk, and build strength safely? | Can this person carry out daily tasks in this home? |
| Typical work | Gait training, balance, strengthening exercises, endurance | Bathing, dressing, meal prep, transfers, energy pacing |
| Equipment role | Walkers, canes, assistive devices for mobility | Grab bars, shower chairs, dressing aids, reachers |
| Environment focus | Movement patterns and physical capacity | Room layout, furniture height, bathroom setup, daily routine |
| Common after | Joint replacement, stroke, fall, general deconditioning | Joint replacement, stroke, hand surgery, cognitive changes |
What Happens During the First Home OT Visit
Most first visits follow a similar shape. Here is what families can expect in the hour or so after the therapist arrives.

How Medicare Coverage Works for Home Occupational Therapy
Medicare covers Occupational Therapy visits at home when a physician orders them as part of a home health plan of care and the patient meets the homebound standard. Homebound does not mean bedbound. It generally means leaving the house takes real effort or help.
The part that surprises families most is the referral. A doctor's order has to come first before visits can be scheduled. Callers ask about this constantly, usually some version of does Medicare cover this, and do we need a referral from the doctor first. The answer to both is yes.
You can read the specifics on covered home health services directly from Medicare's own coverage page, and we cover the order process in more detail in why a physician referral is required for home health.
Families in Pacific Grove, Carmel, and Seaside helping a parent recover from a hip or knee replacement often do not learn this coverage exists until a nurse or a Medical Social Worker mentions it during an intake call. Ask about it at the time of discharge, not after the first fall.
Coverage for therapy at home also comes up constantly with physical therapy, and the rules are similar. That is walked through in does Medicare cover physical therapy at home.
The Equipment Conversation Is Worth Having Early
An Occupational Therapist will usually recommend adaptive equipment, and this is where a lot of the practical value shows up. Grab bars, shower chairs, raised toilet seats, long-handled shoe horns, sock aids, reachers.
These are modest changes that often decide whether someone can manage at home without full-time help. Costs vary quite a bit by item and supplier, but many of the smaller aids fall in the low double digits, while durable items like hospital beds and wheelchairs are more commonly rented than bought. The therapist can tell you what typically falls under Medicare's durable medical equipment provisions and what usually does not, so families know what to ask for and what to budget.
One local patient wrote in a review that the nurse who assessed her home before surgery "left me with useful information" for staying safe during recovery, and that the therapy team "encouraged me to do more than I could imagine possible so soon after surgery." That combination, a safer house plus steady pushing, is the whole point.
For the longer view on making a home work over years rather than weeks, see what actually makes staying home as you age possible.
Frequently Asked Questions About Occupational Therapy at Home After Surgery
How many occupational therapy visits will my parent get at home?
It depends on the surgery, the recovery, and what the physician orders. Home health is intermittent care, so visits are typically a few times per week for a stretch of weeks, not daily. The therapist reassesses progress and the plan changes as the patient improves.
Is this the same as having someone come help with bathing and meals every day?
No, and this trips up a lot of families. Home health occupational therapy is skilled, physician-ordered clinical care on a visit schedule. If your family needs daily hands-on help with personal care, that is private-duty home care, and it is usually paid for out of pocket. Many families use both, with the home health team as the clinical anchor.
My mom refuses to use a walker or a shower chair. Can the therapist help with that?
Often, yes. Refusal usually comes from pride or from equipment that was never fitted properly. An Occupational Therapist can adjust the height, show why a particular setup helps, and sometimes find a less obtrusive option that a patient will actually accept.
Does insurance other than Medicare cover home occupational therapy?
Medi-Cal, Veterans benefits, and most private insurance plans cover home health services, though the requirements and visit limits differ. Coverage details are worth confirming during the intake call rather than assuming.
Do you serve areas outside the Monterey Peninsula?
Home health service across the Central Coast covers Monterey County, including Salinas and King City, along with San Benito County including Hollister, parts of Santa Cruz County, and South Santa Clara County. Coverage by exact address is worth confirming by phone before a discharge date is set.
Questions About Therapy at Home After a Hospital Stay?
If a parent is coming home to Monterey, Salinas, Pacific Grove, or anywhere else in Monterey County after surgery and you are not sure what the home health referral covers, it is a fair question to ask out loud. A care coordinator can walk through what the physician ordered, what Medicare or Medi-Cal typically covers, and what an Occupational Therapist would look at in that specific house. Central Coast VNA & Hospice has been visiting homes in this region since 1951, and the phone number is 831-372-6668.

When a Parent's Dementia Makes Medication Management a Safety Issue
A Monterey County family put it plainly in a message to a local nonprofit home health team. An 86-year-old father had just been diagnosed with dementia. He was taking more than five prescriptions, and his wife, in her 80s and recovering from her own serious illness, was the one keeping track of all of it.
Their question was direct. Could a Registered Nurse look over his medications and help put together a daily schedule?
That same question arrives again and again from families on the Monterey Peninsula, across the Salinas Valley, and out toward King City. This article covers what actually goes wrong with dementia and medication management at home, what a skilled nursing visit looks like, and how coverage works.
Why a Pill Routine That Worked Six Months Ago Can Be Dangerous Now
Dementia changes three things at once: how a person processes instructions, how they recognize pills, and whether they remember taking a dose. Any one of those alone is manageable. Together, they break a routine that used to run fine.
Most families worry about missed doses. The bigger danger is usually double-dosing, because a person who does not remember the morning pills may take them again at noon.
That matters most with a few common categories:
- Blood thinners, where an extra dose raises bleeding risk
- Diabetes medications and insulin, where a repeat dose can drop blood sugar fast
- Cardiac drugs for blood pressure and heart rhythm
- Pain medications and sedatives, which compound confusion and fall risk
An extra dose of a blood pressure medication can end with a fall in the hallway and an ambulance ride to an emergency department in Monterey or Salinas. That is often the moment a family realizes the system had been failing for weeks.
One more detail families miss: pills get moved. A person with dementia may relocate bottles, hide them, or set them down somewhere odd, which makes it impossible to tell from the bottle whether a dose was taken.

What a Registered Nurse Actually Does During a Medication Visit
Families often picture a nurse counting pills and filling a plastic organizer. That is a small piece of it. The visit is a clinical review of the whole picture, in the home, with the actual bottles on the table.
A visit focused on medication management generally includes:
- A full review of every prescription, over-the-counter drug, and supplement, including duplicates from different prescribers
- A check for interactions and doses that no longer fit the patient's kidney function, weight, or blood pressure
- An honest assessment of whether the patient can still self-administer safely
- Communication with the prescribing physician about simplifying the regimen, such as consolidating dose times or dropping a drug that no longer helps
- Hands-on teaching for the family member running the day-to-day system
- A written schedule that matches how the household actually works, not an idealized version of it
That teaching piece is the part families underestimate. For a spouse in her 80s managing an ailing partner, sitting down with a nurse for an hour can turn daily dread into something she feels able to handle.
The visit is also where problems surface that nobody reported over the phone. A skilled nurse on a home visit sees the stairs, the lighting, the two bottles that look nearly identical, and the sticky notes on the refrigerator that stopped making sense a month ago.
How Medication Needs Shift as Dementia Progresses
Dementia-related medication problems tend to compound. What works with reminders in the early stages often does not work at all 12 to 18 months later.
| Stage | What families usually notice | Support that tends to fit |
|---|---|---|
| Early | Occasional missed doses. A weekly organizer and reminders still mostly work. | Family reminders, one clinical review of the full list, a simplified schedule |
| Middle | Doses repeated or skipped. Bottles moved or hidden. Confusion between similar looking tablets. | Skilled nursing visits, pre-set organizers, physician review to reduce the number of drugs |
| Later | No reliable ability to self-administer. Refusing pills or spitting them out. | Another person administering every dose, with clinical oversight and ongoing family teaching |
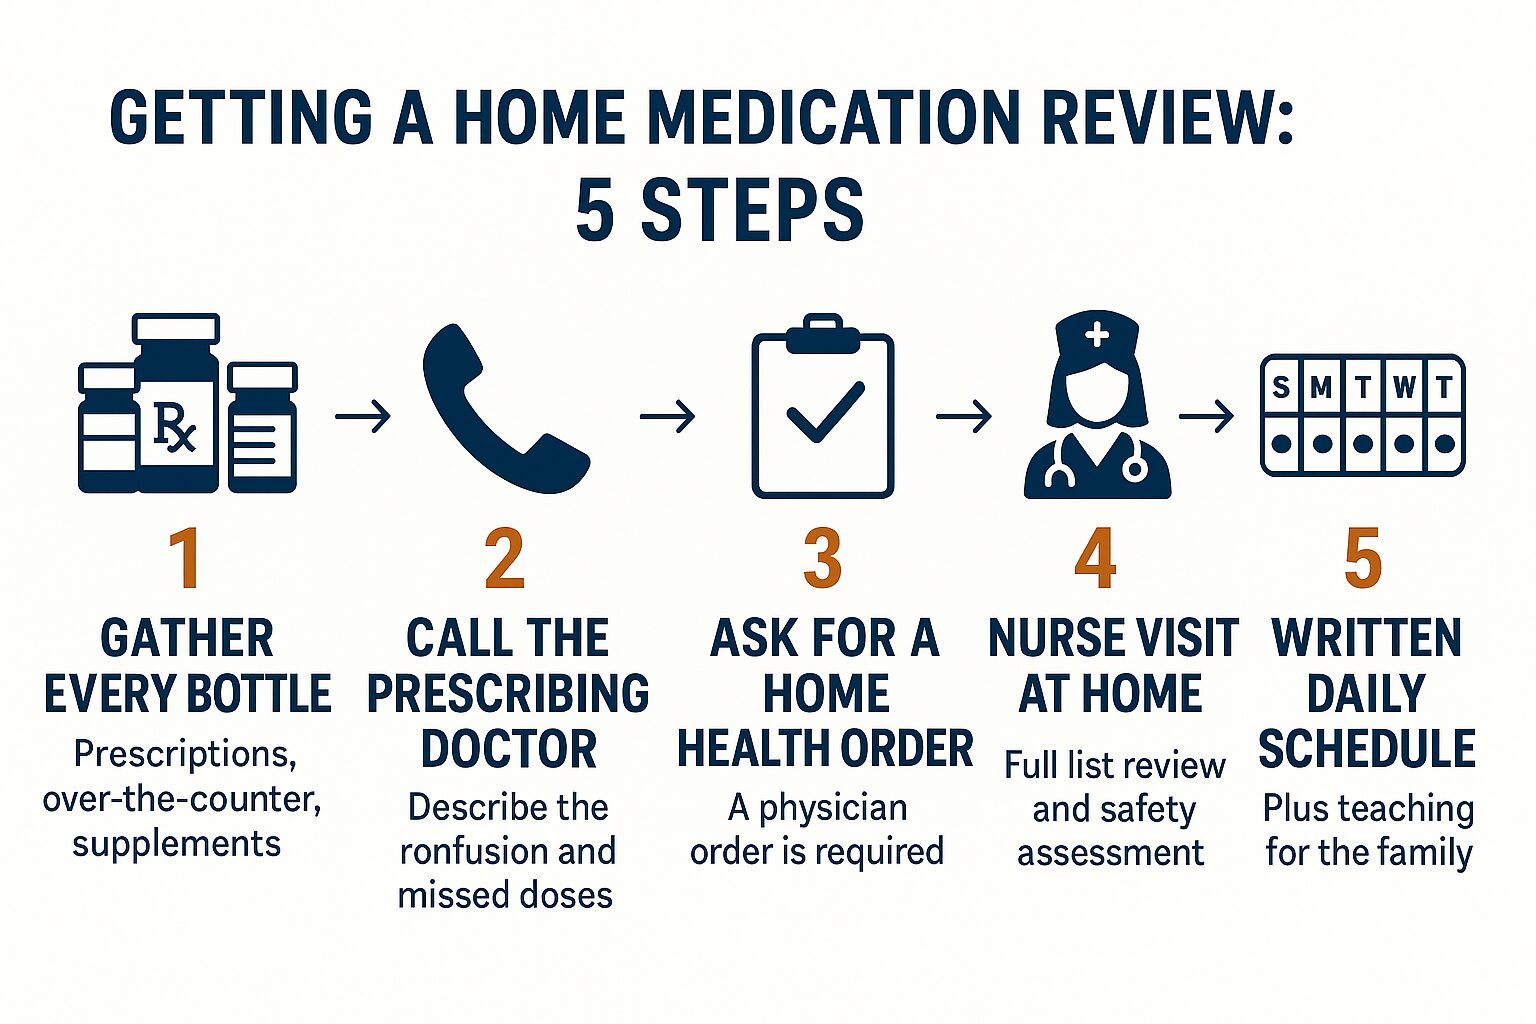
How Families Get a Medication Review Started
The path is shorter than most families expect, but it does start with the physician rather than the home health agency.
Medicare Covers This, and Many Families Are Never Told
Home health visits for medication management are a covered benefit under Medicare when two conditions are met. There has to be a physician order, and the patient has to meet the homebound criteria, meaning leaving home takes considerable effort or help.
Medicare publishes the rules for home health services coverage directly, and skilled nursing on an intermittent basis is part of it. Nonprofit agencies in the region, including Central Coast VNA & Hospice, accept Medicare, Medi-Cal, and Veterans benefits along with most private insurance.
Here is where families get stuck. Callers regularly reach local agencies not knowing that a doctor's order comes first, which delays everything by days or weeks. And the physician who wrote the prescriptions does not always connect a new dementia diagnosis to eligibility for skilled nursing at home.
So the family sometimes has to make that connection and ask for it. Plenty of households in Hollister, King City, and the Salinas Valley have gone a year without support that was available the whole time. If you want the mechanics, this piece on why a physician referral is required walks through the process.
One honest limit: home health is intermittent skilled care, usually a few visits per week, not someone in the house every day. Families who need daily hands-on help typically add private-duty help, and that market runs into the thousands of dollars per month depending on hours. Costs vary widely, so ask any provider for specifics on your situation.
Asking Early Is Easier Than Recovering From a Crisis
Families who wait for the fall, the hypoglycemic episode, or the hospitalization end up making decisions under pressure with fewer options. Families who ask while the situation is still messy but manageable get to build something on their own terms.
The point of early involvement is not to take over. It is to set up a system the household can actually keep running, then adjust it as the disease changes what is needed.
That usually means the whole team gets involved over time: nurses, therapists, medical social workers, chaplains, volunteers, and other clinicians. A Medical Social Worker may be the one who finds the community resources nobody knew about, which is exactly what one Monterey Peninsula family described in a public review after their 91-year-old mother came onto service.
If you are already past the medication question and wondering about the bigger picture, when caring for an aging parent becomes more than you can do alone covers the next set of decisions.
Frequently Asked Questions About Dementia and Medications at Home
Can a nurse just come out and look over my parent's medications?
Yes, that is a normal reason for a home health visit, but it needs a physician order first. Call your parent's doctor, describe what you are seeing with missed or repeated doses, and ask for a home health referral for medication management.
Does Medicare pay for medication management at home?
Skilled nursing at home is covered under the Medicare home health benefit when there is a physician order and the patient meets homebound criteria. Medi-Cal and Veterans benefits also cover home health for eligible patients. Coverage details depend on the individual plan, so confirm with the agency before services start.
What if we need someone in the house every day?
Home health visits are intermittent, often two or three times a week, so daily hands-on help usually comes from a private-duty agency. Many Monterey County families use both, with the home health team as the clinical anchor and private help filling the daily hours.
Will the nurse take over giving the pills?
Not usually. The goal is a workable system the family can sustain between visits, which often means the nurse pre-sets organizers, writes out the schedule, and teaches the spouse or adult child what to watch for.
My dad insists he can handle his own medications. What then?
That is common, and it is one reason an outside clinician helps. A nurse can assess self-administration objectively and frame the changes as doctor's orders rather than a family member questioning his judgment, which lowers the resistance considerably.
Want to Understand What Support Is Available Near You?
If you are sorting through pill bottles at a kitchen table somewhere in Monterey County and not sure what comes next, a conversation with a care coordinator can clarify what is covered and what a home visit would involve. Central Coast VNA & Hospice has been working with families across Monterey County, San Benito County, and the surrounding Central Coast since 1951, and information is available at 831-372-6668 or ccvna.com whenever you are ready to ask.

Speech Therapy at Home: What It Covers and Who Qualifies
Most families picture the same thing when they hear speech therapy: someone practicing words that came out wrong. That picture is only a small slice of what a Speech Therapist actually does in the home.
After a stroke, a head or neck surgery, or a long hospital stay, the harder problems are often invisible from across the room. Trouble swallowing safely. Forgetting the steps of a task. Losing the thread of a conversation halfway through.
Families across Monterey County call about this after a discharge from Community Hospital of the Monterey Peninsula, Salinas Valley Health, or Natividad, usually with two questions: does Medicare cover it, and do we need a doctor's order first. This guide answers both, and explains what speech therapy at home actually covers after a stroke or surgery.
What speech therapy at home actually covers after a stroke or surgery
A Speech Therapist, also called a speech-language pathologist, works on three broad areas in the home. Speech is only one of them.
- Swallowing safety (dysphagia). Coughing during meals, a wet or gurgly voice after drinking, food that seems to stick, or unexplained weight loss.
- Communication. Slurred words, trouble finding the right word, difficulty understanding what others say, or a voice that has gone weak and quiet.
- Thinking and memory (cognition). Losing track of medications, repeating questions, trouble sequencing daily tasks, poor safety awareness after a fall or a head surgery.
That third one surprises people. A patient in Pacific Grove who can hold a normal conversation may still be unable to reliably remember whether they took their morning pills.
That is a speech therapy problem, and it is also a safety problem. It is one reason therapy visits are usually coordinated with a Registered Nurse who is already managing medications in the home.
Speech therapy in the home is part of a physician-directed plan, the same way skilled nursing care at home works. Visits are intermittent, goal-based, and reassessed as the patient improves.

The swallowing problem families almost never see coming
Of everything a Speech Therapist handles at home, swallowing difficulty carries the highest stakes. When food or liquid goes down the wrong way, it can settle in the lungs and cause aspiration pneumonia, which sends patients right back to the hospital.
It often shows up quietly. A parent starts eating less. Meals take twice as long. They stop drinking water because it makes them cough. According to the National Institute on Deafness and Other Communication Disorders, swallowing problems commonly follow stroke and other nervous system conditions, and they can lead to poor nutrition and dehydration.
What a Speech Therapist does about it in the home:
- Evaluates how the patient handles different food textures and liquid thicknesses
- Teaches positioning and swallowing techniques that reduce risk
- Recommends diet changes, cup types, and pacing that the family can actually follow
- Trains family members on what warning signs mean a call to the nurse
Families frequently do not realize this is a skilled clinical concern at all. They treat it as picky eating, and then the pneumonia arrives three weeks later.
What Families Notice vs. What a Speech Therapist Is Looking At
The same everyday observation can point to a very different clinical issue. Here is how common household signs line up.
| What the family notices | What it may actually be | What therapy addresses |
|---|---|---|
| Coughing or throat clearing during meals | Unsafe swallow, aspiration risk | Swallow techniques, texture and liquid changes, positioning |
| "He just doesn't talk much anymore" | Weak voice or word-finding difficulty after stroke | Voice strength, language exercises, communication strategies |
| Missed or doubled medications | Memory and sequencing changes | Cognitive strategies, written routines, safety cues |
| Repeating the same question | Short-term memory loss after surgery or illness | Memory supports the family can maintain between visits |
| Eating less, losing weight | Fear of choking, fatigue while chewing | Meal pacing, calorie-dense soft foods, endurance work |
The Qualifying Path in Four Steps
Most families get stuck on the referral step. This is the order things actually happen in.
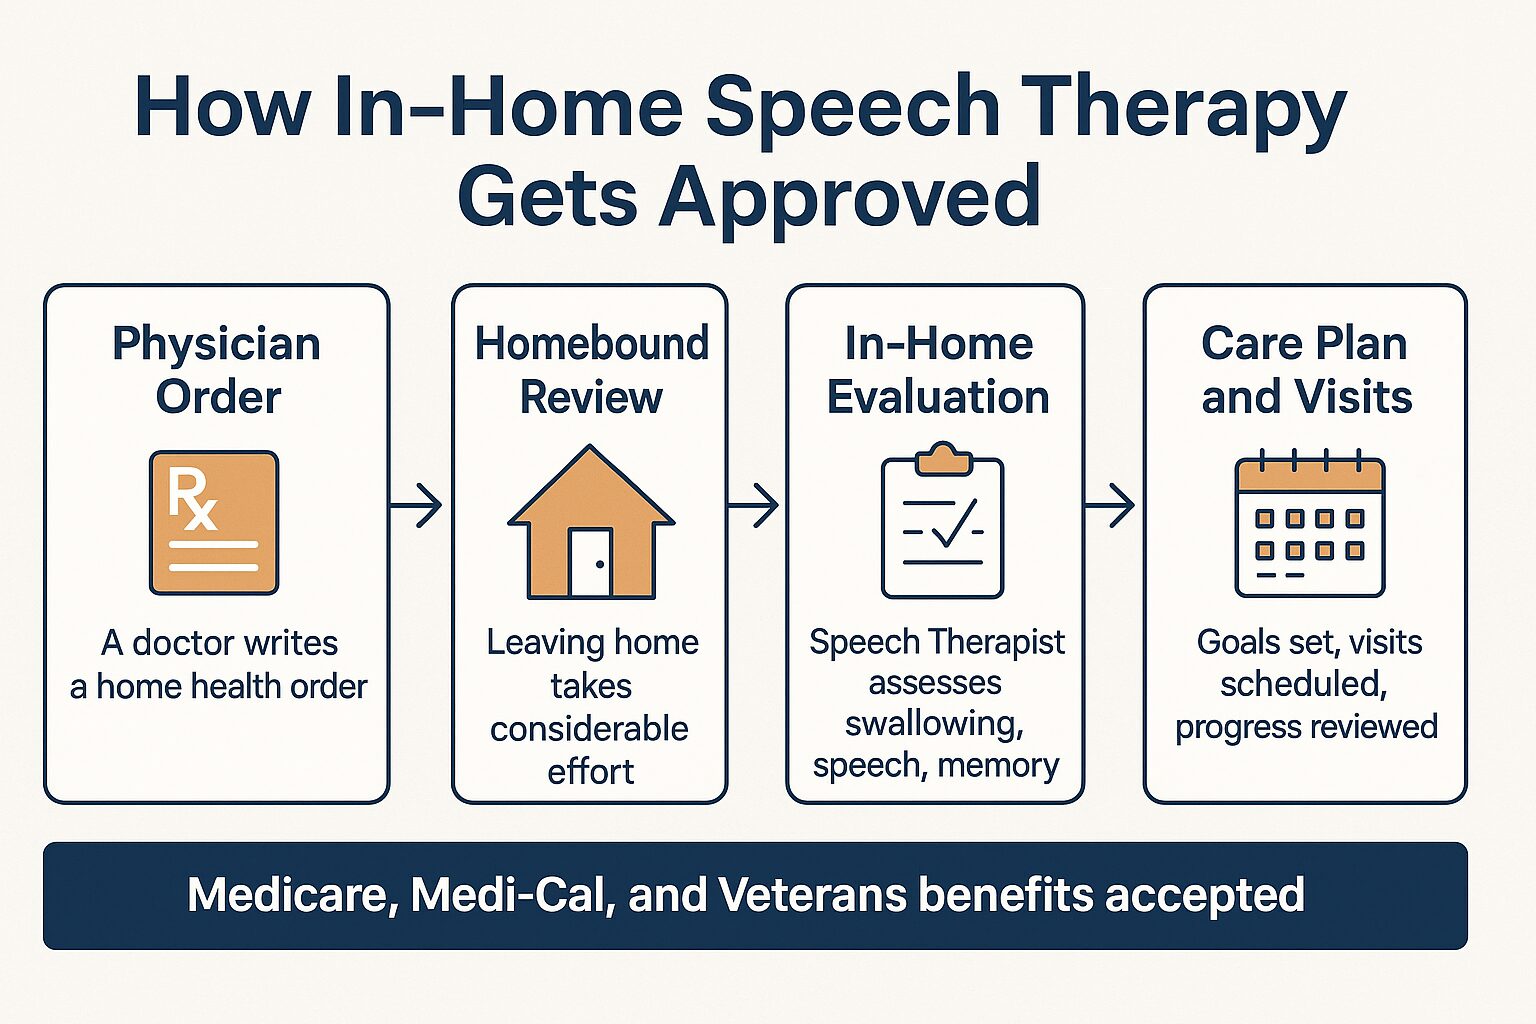
Who qualifies, and what "homebound" really means
To get speech therapy at home under Medicare, a patient generally needs two things: a physician order and to meet the homebound requirement. Those are the same conditions that apply to skilled nursing and physical therapy.
The homebound standard is where families count themselves out too early. It does not mean the patient can never leave the house. It means leaving takes a considerable and taxing effort, or that they need help or a device to do it.
Someone in Salinas who can get to a Sunday church service with a walker and a family member's arm may still qualify. Someone recovering from head and neck surgery who tires after twenty minutes upright may qualify too.
A few practical notes:
- Medicare, Medi-Cal, and Veterans benefits are all accepted for home health services here
- The order can come from the hospital physician at discharge or from the primary care doctor later
- Home health does not cover ages 0 to 21, maternity diagnoses, or primary behavioral health conditions
If the rules feel murky, a Registered Nurse or care coordinator can walk through the specific situation. The guidelines are more flexible than most families assume, which is also true of Medicare coverage for physical therapy at home. And if you are unsure how the order gets written, this explanation of the physician referral process covers it step by step.
Why the kitchen beats the clinic room
A clinic can simulate a meal. A home does not have to.
When a Speech Therapist sits down in a patient's own King City or Hollister kitchen, they are working with the actual cups in that cupboard, the actual chair height, the food that family actually cooks. Swallowing strategies get practiced with dinner, not with a demonstration.
The same holds for memory work. Cues get placed on the real pill organizer, on the real calendar, in the room where the patient will use them at 7 a.m. tomorrow.
One family on the Peninsula described the team that came to their home as nurses, physical therapists, and a Medical Social Worker who each evaluated a different piece of the picture, then built one plan. That coordination between nurses, therapists, social workers, chaplains, volunteers, and other clinicians is the point of home-based care.
Progress made in the room where the patient lives tends to stick. There is no gap between the exercise and real life.
Asking for an evaluation is not a commitment
Plenty of families wait because they are not sure the problem is "serious enough" to bother anyone about. That hesitation costs weeks.
A formal evaluation gives you information, not an obligation. A Speech Therapist can tell you what is present, what is not, which goals are realistic, and roughly how many weeks a course of therapy might run.
Sometimes the answer is that no therapy is needed and the family can stop worrying. Sometimes the answer changes the meal plan that night. Either outcome is better than guessing.
If a discharge is coming up soon, it is worth reading what families often miss when planning a hospital discharge to home, because the speech therapy question is one of the most commonly skipped items on the list.
Frequently Asked Questions About In-Home Speech Therapy
Does Medicare cover speech therapy at home, and what will we pay?
Medicare covers speech-language pathology as part of the home health benefit when the patient meets the homebound requirement and has a physician order. For eligible patients, the covered home health visits themselves typically come with no coinsurance, though durable medical equipment is usually billed separately at a percentage. Coverage details depend on the plan, so ask a care coordinator to review the specific situation before assuming anything.
Do we need a doctor's order first, or can we just call and schedule?
A physician order is required before a visit can be scheduled. This is the single most common point of confusion on incoming calls. The hospital physician can write it at discharge, or the primary care doctor can write it afterward.
My mother's speech is fine. Is speech therapy still relevant?
Often yes. Swallowing difficulty and memory or sequencing problems fall under speech therapy even when the patient speaks clearly. If she is coughing at meals, losing weight, or mixing up medications, an evaluation is worth requesting.
How many visits does in-home speech therapy usually involve?
It varies with the diagnosis and goals. Home health is intermittent, meaning scheduled visits rather than daily coverage, and the plan is reassessed as the patient progresses. A Speech Therapist can give a realistic estimate after the initial evaluation.
We need someone in the house every day. Is that what this is?
No, and this comes up often. Home health provides skilled clinical visits, not around-the-clock personal care. Many families pair home health with a private-duty agency for daily hands-on help, and a care coordinator can point you toward local options for that piece.
Still Unsure Whether a Speech Therapy Evaluation Makes Sense?
If someone you love is coughing at meals, forgetting medications, or struggling to be understood after a stroke or surgery, a conversation costs nothing but a few minutes. Central Coast VNA & Hospice has provided home-based care across Monterey County and the surrounding Central Coast since 1951, and a care coordinator can talk through whether an in-home evaluation fits your situation. You can reach the team at 831-372-6668 or read more at ccvna.com.

Summer Heat and Smoke on the Central Coast: What Home Patients Need to Know
It usually starts with a phone call. A daughter in Pacific Grove, wearing a sweatshirt in 62-degree fog, calls her father in Salinas and finds out his house has been sitting at 94 degrees since noon.
That gap between the coast and the valley is one of the most misunderstood health risks in Monterey County. And when wildfire smoke drifts in on top of the heat, a patient managing serious illness at home is dealing with a medical situation, not a weather annoyance.
This guide covers what heat and smoke actually do to a seriously ill person at home, which medications make it worse, and the handful of questions families should answer before the next advisory shows up on their phone.
Why heat hits inland patients harder than coastal ones
Monterey County is really two climates. Coastal Monterey, Pacific Grove, and Carmel often stay in the 60s through summer, while Salinas, Gonzales, Soledad, and King City can push into the 90s and past 100.
A lot of seriously ill patients live in those hotter inland communities. Their adult children often live on the Peninsula, where the fog makes the risk feel abstract.
Heat is harder on some bodies than others. Risk climbs for:
- Adults over 65, who sweat less and feel thirst less reliably
- People with heart disease or a history of heart failure
- People with COPD or other chronic lung conditions
- People with diabetes, which can affect circulation and sweating
- Anyone with limited mobility who cannot move to a cooler room on their own
- Anyone taking medications that interfere with temperature regulation
One more factor matters here: many older inland homes have no central air conditioning. A home built to shed valley heat overnight does not do much during a five-day stretch of triple digits. If your parent is already having trouble managing the house on a hot day, that is often the same moment families start asking whether it's time to get some help at home.

Heat plus wildfire smoke is a different kind of risk
Smoke season on the Central Coast rarely stays put. Fires burning in Big Sur, Los Padres National Forest, or well outside the county can push haze into the Salinas Valley and across the Peninsula for days.
In July 2026, the American Heart Association published findings that the combination of extreme heat and wildfire smoke can nearly double the risk of a fatal heart attack, with older adults facing even greater risk. You can read the American Heart Association's warning on heat and wildfire smoke directly.
The reason is fairly simple. Heat already makes the heart work harder to cool the body. Fine smoke particles inflame the airways and lower the oxygen the blood is carrying. Stack those two demands on a heart or set of lungs that is already compromised, and the margin gets thin fast.
For a patient with a cardiac diagnosis, COPD, or an advanced illness, that means a smoke event needs to be managed clinically, not just waited out. Symptoms families should watch closely during a smoke day include new or worsening shortness of breath, chest pressure, a cough that will not settle, confusion, and swelling in the legs or feet.
The medication piece most families never hear about
This is the part that surprises people. Some of the most common medications for seriously ill patients make it harder for the body to handle heat.
Monterey County's own emergency heat guidance flags people taking certain medications as higher-risk during heat events. Broad categories that can affect temperature regulation, fluid balance, or sweating include:
- Diuretics, often called water pills
- Beta blockers and some other blood pressure medications
- Certain antidepressants and antipsychotics
- Anticholinergic medications, including some bladder and allergy drugs
- Medications that cause drowsiness or reduce awareness of thirst
Nobody should stop or change a dose on their own. But a Registered Nurse visiting the home can look at the full medication list, flag the combinations that raise heat risk, and bring concerns back to the treating physician.
That kind of review is routine work on a home visit. If you have never seen one, this walkthrough of what a skilled nurse actually does during a home visit covers the ground. Medication management is also part of why a single visit often catches problems a family has been living with for months.
Warning signs during a heat or smoke event and what they usually mean
Use this as a general reference, not a diagnosis. Any patient with a serious illness should have symptom instructions from their own physician or care team.
| What you notice | What it may point to | Typical next step |
|---|---|---|
| Hot, dry skin with no sweating, plus confusion | Possible heat stroke | Call 911 right away |
| Chest pressure, pain, or a racing heartbeat | Cardiac event | Call 911 right away |
| Sudden severe shortness of breath or bluish lips | Respiratory distress | Call 911 right away |
| Dizziness, weakness, cramping, heavy sweating | Early heat exhaustion | Move to a cooler room, give fluids, call the care team |
| Worsening cough or wheeze during a smoke day | Airway irritation | Call the care team or physician the same day |
| Not urinating much, very dark urine | Dehydration | Call the care team or physician the same day |
| More confused or sleepy than usual | Heat effect or medication effect | Call the care team the same day |
Five questions to answer before the next heat advisory
Families who work through these five questions ahead of time spend far less energy scrambling once an advisory hits.

Building a plan that fits your parent's actual house
The plan does not need to be elaborate. It needs to be specific to the home and the person in it.
Start with cooling. If there is no air conditioning, pick one room to cool rather than the whole house. Costs vary, but many households in Monterey County find portable or window units land somewhere in the range of a couple hundred dollars, and a good box fan with drawn shades makes a real difference in a valley home overnight.
Then work through the practical gaps:
- A backup plan for power, especially if the patient uses an oxygen concentrator or refrigerated medication
- Someone who can physically get the patient to the cooler room, since a hallway is a long trip for a patient with limited mobility
- Windows and doors closed during smoke, with recirculating air and a clean filter if the home has a system
- A written symptom list on the refrigerator so any family member or visitor knows what to act on
- Fluid guidance from the physician, because some heart and kidney patients have fluid limits that override general advice to drink more
One caller described the feeling plainly: they just needed someone to come out and help, because they did not know where to start. That is a normal place to be. Families managing a hospital discharge in August have plenty on their plate already, and the pieces families tend to miss during a discharge home often include seasonal safety.
The team already in the home is part of the answer
Here is what families often overlook. If a patient is receiving home health, palliative care, or hospice care at home, clinicians are already walking through that house on a regular schedule.
A Physical Therapist who visits weekly already knows whether the patient can safely get down the hall to a cooler room. A nurse already has the medication list. A Medical Social Worker already knows what community resources exist in Salinas or Hollister or King City.
Across a home care team, that means nurses, therapists, social workers, chaplains, volunteers, and other clinicians all see pieces of the picture. Seasonal safety planning is a reasonable thing to raise at the next visit instead of researching alone at 11 p.m.
One family in Monterey County described a team of nurses, physical therapists, and a Medical Social Worker coming into the home and said they were "blown away by the personalized care." That kind of coordination is exactly what makes a heat plan realistic rather than theoretical. It is also part of what makes staying home as you age workable through a hard summer.
Frequently Asked Questions About Heat, Smoke, and Home Patients
Does Medicare cover home health visits during a heat wave?
Heat by itself is not a qualifying reason for home health. But Medicare covers physician-ordered home health when a patient meets the clinical criteria, and a real change in condition during a heat or smoke event is worth reporting to the physician. Home health always starts with a physician referral, which is a step many families do not realize is required.
Should we cancel a scheduled home visit when the air quality is bad?
Talk to the care team rather than deciding on your own. Clinicians work through smoke days regularly, and a visit during a bad air stretch is often more useful than a normal one because someone is laying eyes on the patient.
My mother is on hospice at home. Does smoke really matter at that point?
Yes. Hospice care is focused on comfort, and smoke can cause coughing, breathlessness, and agitation that make a patient genuinely uncomfortable. Pain and symptom management includes respiratory symptoms, so report changes just as you would report new pain.
What about air purifiers? Are they worth it?
A unit with a HEPA filter sized for one room can meaningfully cut indoor fine particles during a smoke event. Prices vary widely by room size and brand, so check what the room actually needs. Running it in the bedroom where the patient sleeps usually gives the most benefit per dollar.
Who do I call if I am not sure whether something is an emergency?
Keep the care team's clinical line where you can see it, and use 911 without hesitation for chest pain, severe shortness of breath, or new confusion. Guessing wrong toward caution is the right error to make.
Want help thinking through a heat and smoke plan?
Summers in Monterey County are not getting gentler, and families in Salinas, King City, and Hollister feel that before anyone on the coast does. If you have questions about care at home during a heat or smoke event, a care coordinator at Central Coast VNA & Hospice can talk through what applies to your loved one's situation. Call 831-372-6668 or visit ccvna.com when the timing is right for you.

Why a Physician Referral Is Required for Home Health, and How It Works
One of the most common things families say when they first call about home health is some version of: "I didn't know I needed a referral to get started." It comes up again and again, and usually the family is already frustrated, because no one at the hospital or the doctor's office explained this step to them.
In Monterey County, many families are navigating a loved one's discharge from Community Hospital of the Monterey Peninsula or Salinas Valley Health for the first time. The process moves quickly, and the referral requirement can feel like a surprise obstacle when it should be a routine part of the discharge plan.
This article explains what a physician referral for home health actually is, how it gets started, and what your family's role looks like through the process, so you are not caught off guard when the moment comes.
What a Physician Referral for Home Health Actually Means
A physician referral is a written order from a licensed physician that does two things at once. It certifies that the patient has a medical need for skilled care at home, and it confirms that the patient meets the homebound standard Medicare requires.
Without this order, a home health agency cannot legally admit a patient for skilled services. That includes skilled nursing, physical therapy, occupational therapy, speech therapy, and wound care. It is not a paperwork formality, it is the clinical and legal authorization that makes Medicare coverage possible in the first place.
The referring physician also takes on an ongoing role. Medicare requires that a physician review and sign the patient's plan of care within a specific window after services begin, and that the plan be recertified if care continues beyond the initial period. So the referral is not a one-time event. It is the beginning of a documented, physician-supervised relationship between the patient and the home health team.
For a closer look at what happens once a skilled nurse actually arrives at the home, What Does a Skilled Nurse Actually Do on a Home Visit? walks through that process in plain terms.
What 'Homebound' Means, and Why It Trips People Up
The word "homebound" sounds more restrictive than it actually is. Many families assume it means their loved one cannot leave the house under any circumstances. That is not the standard.
Medicare considers a patient homebound when leaving the home requires considerable effort, meaning the patient uses a wheelchair, walker, or crutches, or has a condition that makes leaving medically inadvisable. The patient can still go to a medical appointment, attend a religious service, or step outside occasionally. What matters is that leaving is the exception, not the routine.
Families do not have to make this determination on their own. A Registered Nurse from the home health team will assess homebound status during the first visit. That assessment becomes part of the clinical record that supports Medicare billing.
Here are common situations that typically qualify:
- Recent surgery with limited mobility
- Recovering from a fall or fracture
- Significant weakness from a cardiac event or stroke
- A condition where leaving the home poses a genuine medical risk
- Dependence on a walker, wheelchair, or assistive device to leave safely
If you are unsure whether your family member qualifies, that question is worth asking a care coordinator directly rather than guessing.

How the Referral Process Actually Starts
Most families have no idea who initiates the referral, which is exactly where the confusion starts. The answer depends on where the patient is at the time.
If the patient is being discharged from a hospital: A hospital discharge planner or medical social worker typically handles the referral. At Community Hospital of the Monterey Peninsula or Salinas Valley Health, this is a standard part of the discharge planning process. The family does not have to track down a physician or submit paperwork on their own, the hospital team is supposed to coordinate this.
If the patient is already at home and the situation has changed, a new diagnosis, a fall, a medication issue, increasing difficulty managing daily tasks, the referral comes from the primary care physician. In this case, it often starts with a phone call to the doctor's office describing what has changed.
In both situations, the family does not have to manage this alone. A home health agency can also help facilitate the referral by sending the necessary paperwork directly to the physician's office. That removes most of the burden from the family.
For a broader look at what happens in the days right after a hospital stay, After the Hospital Discharge, What Comes Next? is worth reading before a discharge date arrives.
How a Home Health Referral Moves from Order to First Visit
This step-by-step flow shows what happens between a physician writing an order and a nurse arriving at the patient's home.
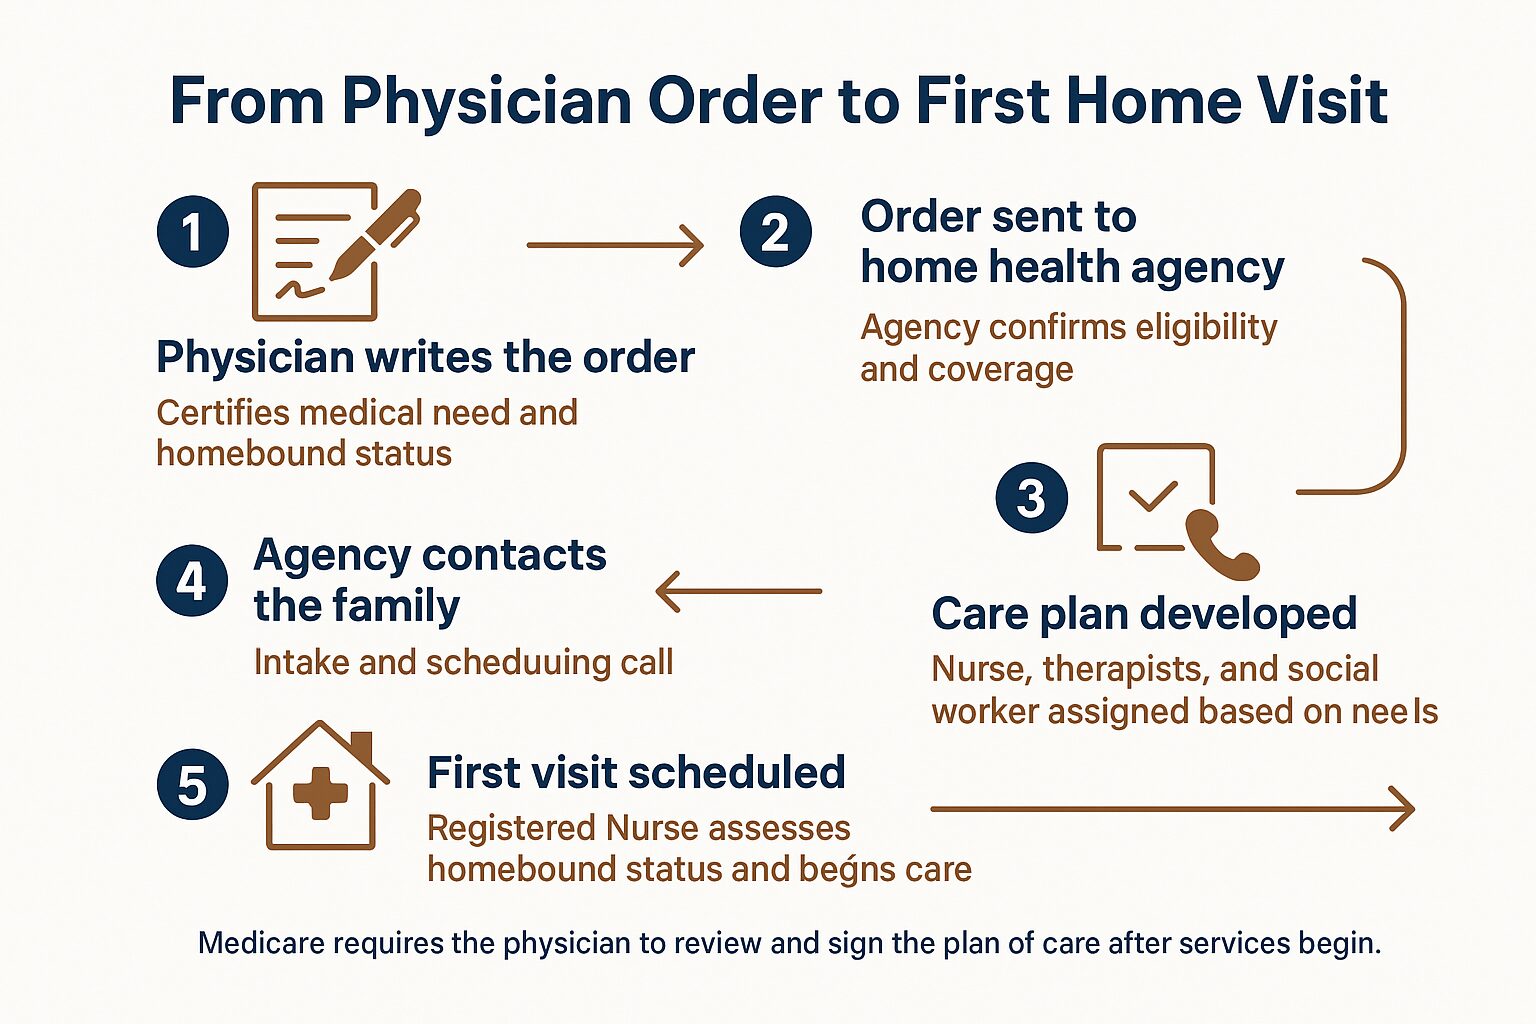
Hospital Discharge vs. Home-Based Referral: What's Different
The referral process looks slightly different depending on where the patient is when care is first needed. This table shows the key differences at a glance.
| Situation | Who Initiates the Referral | What the Family Typically Does |
|---|---|---|
| Patient being discharged from a hospital | Hospital discharge planner or medical social worker | Confirm the referral is in progress and state your agency preference |
| Patient already at home with a changing condition | Primary care physician (after a call or visit) | Contact the doctor's office and describe what has changed |
| Patient with a specialist managing a chronic condition | Specialist or primary care physician, coordinated together | Ask the specialist whether a home health referral is appropriate |
You Can Choose Your Own Home Health Agency
This is one of the most important things families do not know: Medicare gives patients the right to choose their own home health provider. A referring physician or discharge planner cannot require you to use a specific agency.
If a hospital social worker suggests a particular provider and you would prefer a local nonprofit organization, one that has served someone you know, or that has been part of the Monterey Peninsula community for decades, that choice is yours to make. You can say so directly, and the referral will be directed to the agency you select.
This matters because not all home health agencies are the same. Nonprofit agencies, for example, are structured differently from for-profit companies. The mission and the margins work differently. Families who do not know they have a choice sometimes end up with whichever agency is suggested first, rather than the one that actually fits their situation.
If you are trying to think through whether home health is even the right type of care for your loved one right now, Home Health vs. Hospice: How Families Know Which One Fits Right Now lays out the distinction clearly. And if a physician has raised the possibility of palliative care alongside treatment, What Palliative Care Actually Means, and When It Can Start is a useful read.
Frequently Asked Questions About the Home Health Referral Process
Can I request a home health referral myself, or does it have to come from the doctor?
The order itself has to come from a licensed physician, that is a Medicare requirement. But you can absolutely prompt the conversation. Call the doctor's office, describe what has changed with your loved one, and ask whether a home health referral is appropriate. Most physician offices are familiar with the process and can move quickly once the request is made.
What if the discharge planner at the hospital doesn't mention a referral?
Ask directly. Before a loved one leaves Community Hospital of the Monterey Peninsula or any other hospital, it is reasonable to ask the discharge team: "Is a home health referral being placed, and who is it going to?" You can also state your agency preference at that point. Discharge planners handle many cases at once, and a direct question ensures nothing is overlooked.
Does Medicare cover home health if I have a referral?
Medicare covers 100% of approved home health services when the patient meets eligibility criteria, including the homebound standard and a documented need for skilled care. There is no copay for home health under Medicare Part A or Part B when those criteria are met. The Medicare.gov home health coverage page has the full eligibility details straight from the source.
My mother's condition has been stable for months. Can she still qualify?
Stability alone does not disqualify a patient. Medicare allows home health services for patients managing chronic conditions, such as heart disease, COPD, or diabetes, when skilled care is needed to maintain that stability or prevent a decline. The key is that a Registered Nurse or therapist needs to be doing something that requires clinical training, not just general assistance.
How long does it take to get services started after a referral is sent?
Once a referral is received, many home health agencies aim to initiate contact with the family quickly, often within 24 to 48 hours for standard cases. For patients being discharged from the hospital, the goal is typically to have care in place before or immediately after the patient arrives home. If urgency is a factor, say so when you call.
What if my family member is not technically homebound but still needs skilled nursing at home?
If a patient does not meet the homebound standard, Medicare home health benefits would not apply. However, there may be other coverage options depending on the patient's insurance situation, and some services can be arranged privately. A care coordinator can help clarify what options exist based on the specific situation.
Questions About Getting Started With Home Health in Monterey County?
Central Coast VNA & Hospice has been supporting families across Monterey County, Santa Cruz County, San Benito County, and South Santa Clara County since 1951. If you are trying to figure out whether a referral is already in motion, which agency to request, or whether your family member qualifies for skilled care at home, a care coordinator can talk through the specifics with you. Call 831-372-6668 or visit ccvna.com to reach someone who knows this process and can help you take the right next step.